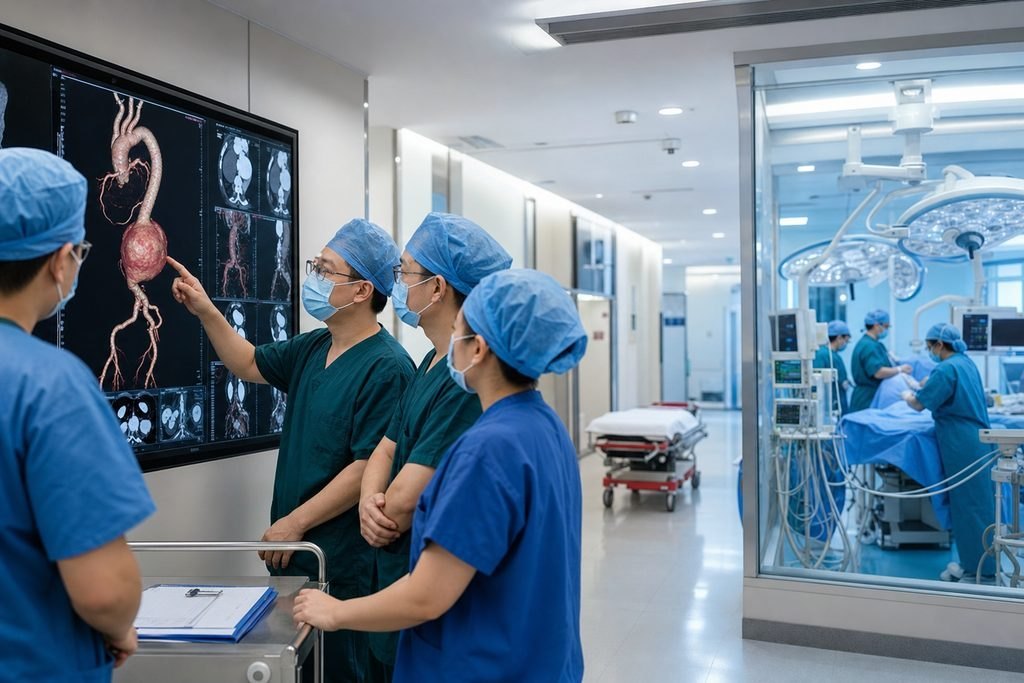
The question a record gap actually blocks
When an overseas patient asks about thoracic aortic aneurysm care in China, a missing record does not block the whole enquiry. It blocks one specific decision. The decision it blocks is whether the receiving team can confirm the aneurysm's current size, its rate of change and the prior treatment plan. Without those documents, the hospital cannot say whether observation, further imaging or repair is appropriate for you.
If the earlier imaging report or the prior specialist letter is absent, the receiving clinician sees only a snapshot. A single scan can show that an aneurysm exists, but it cannot show how fast it has changed. Rate of change is one of the factors that shapes whether a team recommends monitoring or intervention, so this is the question a missing record can leave open.
The practical consequence is not that care is impossible. It is that the China hospital may give a provisional view and then ask for the missing documents before confirming a plan. Naming the gap early shortens that exchange.
Which documents usually answer the size and change question
The records that most directly answer the size-and-change question are the imaging itself and the reports that describe it. For a thoracic aortic aneurysm, that normally means the CT or MRI images, not only the written report, plus the radiologist's measurements and the date of each study. If you have two or more studies separated in time, the comparison between them is the evidence a receiving team needs.
A prior cardiothoracic or vascular specialist letter is also useful because it records what was already recommended and why. A discharge summary from any previous aortic-related admission, and a current medication list, help the team understand the existing plan. These are examples to confirm with the receiving hospital, not a universal mandatory list.
If you are unsure which documents matter, the safest approach is to ask the receiving team directly: which specific reports or image sets would let you confirm the current size and rate of change? That question turns a vague records request into a named list.
Why the date and identifier on each record matter
Two records with the same measurement can mean very different things depending on when they were taken. A scan from last month and a scan from three years ago tell a different story from two scans six months apart. When you send records, include the exact study date and the patient identifiers used by the original hospital, so the receiving team can match images to reports. Without a date, a report is hard to place in sequence, and the receiving clinician cannot tell whether the measurement is current or historical.
Identifiers also matter for image files. A disc or portal link without a name, date of birth or hospital record number can be difficult to link to the correct patient and study. If the original hospital uses a different naming format, a short cover note explaining the identifiers prevents confusion. This matters most when a patient has had several studies at different hospitals, because the same measurement can appear under different accession numbers and dates.
The date also determines which question the record can answer. A recent study can speak to current size. An older study can only speak to what was true at that time. If the missing item is the most recent imaging, the receiving team may be unable to confirm the current size at all, and the gap is not about history but about the present.
A second practical point is the report's own internal date. A radiologist's report may be issued days after the scan, and a specialist letter may be written weeks after that. When you list documents, note both the study date and the report date, because the two are not the same and a receiving clinician reading a summary needs to know which date they are looking at.
Identifiers also help when records are translated. A translated report without the original patient identifiers can be hard to match back to the source images. If a translation is prepared, keep the original identifiers visible alongside the translated text so the receiving team can cross-check the two versions.
This is administrative, not clinical. You are not interpreting the images; you are making sure the receiving clinician can identify which study is which before they review it. If you are unsure whether a particular identifier is needed, ask the receiving team what it uses to match an outside study to a patient, and follow that format rather than guessing.
One more distinction is worth making. A date and an identifier do not make a record complete, and they do not replace the images themselves. They only make an existing record usable. If the underlying study is missing, the correct next step is to request that study from the hospital that holds it, not to send a summary in its place.
Finally, keep the identifier information in one place. A short cover sheet listing each document, its study date, its report date and the patient identifiers used by the original hospital saves the receiving team from opening every file to work out what it is looking at. That single sheet is often the difference between a records set that can be reviewed and one that prompts another round of questions.
What a preliminary reply can and cannot settle
A records-based preliminary reply can tell you whether the available documents are sufficient for a specialist to form a view, and what further information would be needed. It can also indicate whether the case is likely to need a single specialty or a combined review. It cannot confirm hospital acceptance, a final treatment plan or a date for any procedure.
If the reply says the records are incomplete, that is useful information rather than a rejection. It tells you exactly which gap is blocking a fuller answer. Ask the reviewer to name the missing item and the question it would resolve, so your next step is targeted rather than a broad resend of everything.
A preliminary reply is also not a substitute for the treating hospital's own assessment once you are in China. The hospital decides suitability after it has seen you and the full record.
How to write the records request so the gap is named
A useful records request is short and specific. State the diagnosis, the date of the most recent imaging, and the one question you need answered. For example: I have a thoracic aortic aneurysm. My most recent CT was in March. I want to know whether the current size and rate of change suggest monitoring or repair. Please tell me which records you need to answer that.
Avoid sending a complete archive before anyone has asked for it. An initial enquiry can start with a brief summary: the diagnosis, the date of the latest study, the main question and the documents you already hold. The receiving team can then request the specific items it needs.
Keep a simple list of what you have sent and on what date. If a document is missing, note who holds it and whether you can obtain it. That list becomes the working record for the enquiry.
Who is responsible for obtaining the missing record
Responsibility for obtaining a missing record usually sits with the patient or the patient's family, because the original hospital releases records to the patient or an authorised representative. The China receiving team can specify what it needs, but it cannot normally retrieve a foreign hospital's images on the patient's behalf.
If you are working with a coordination service, clarify in writing who will request the record, who will translate it if needed, and who will confirm that the receiving hospital has actually received and opened it. These are administrative steps, and naming them prevents the common situation where both sides assume the other has the file.
For confirmed help with record organisation, interpretation or a specialist appointment request, ChinaSpecialistCare can support the administrative side of this process. The hospital still decides suitability and the clinical plan.
The next step is to send a brief summary through the enquiry form, email or WhatsApp, naming the one question your missing record blocks. An initial enquiry is free and does not require buying a proxy consultation.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.