Why the first visit does not settle the cost question
A first appointment usually answers a narrower question than patients expect. The clinician reviews your description of facial pain, the pattern of attacks, which medicines you have tried and how you responded, and any imaging or neurology records you bring. That review may support a working diagnosis and a direction of care, but it does not automatically produce a complete financial picture for everything that follows.
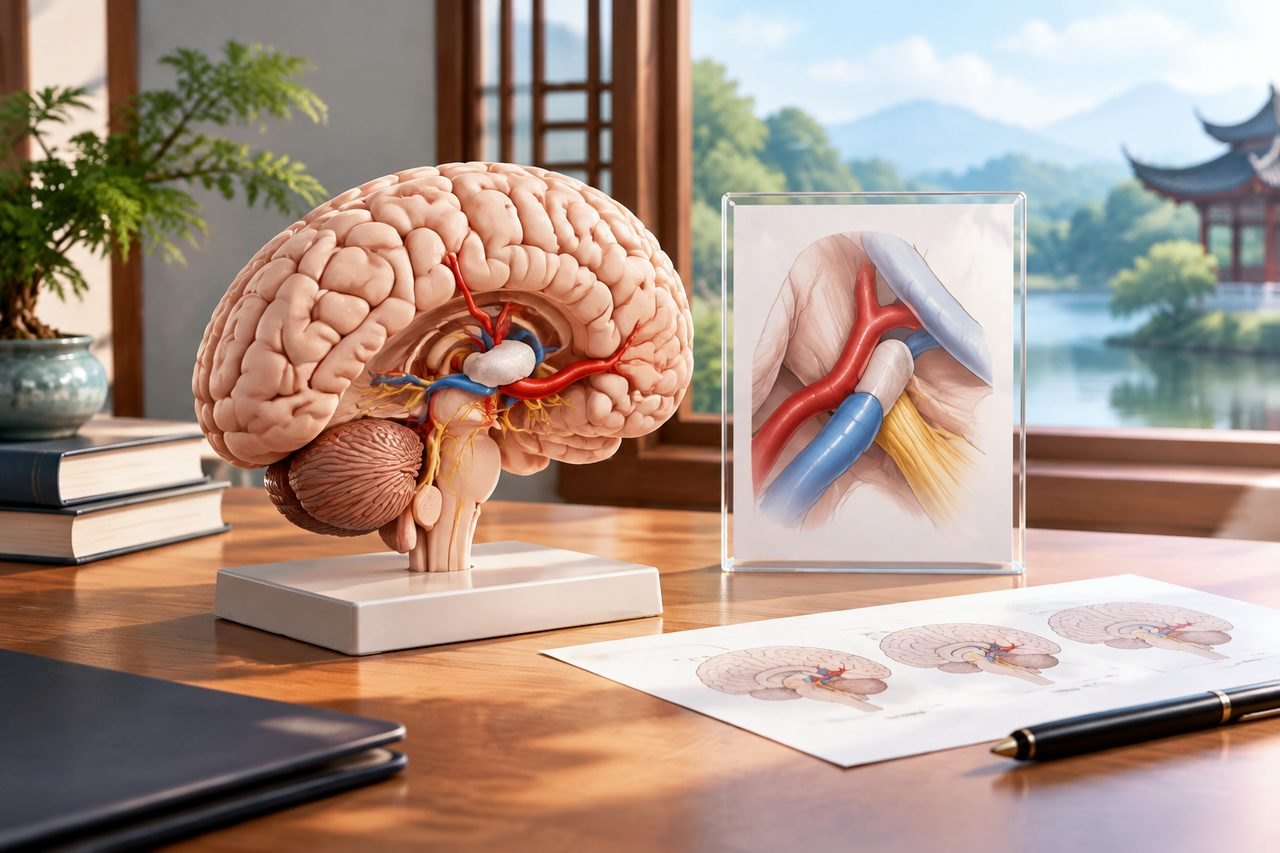
The gap matters because trigeminal neuralgia care is not one item. It can include further clinical assessment, imaging, medicine adjustments, and in selected patients a procedure such as microvascular decompression, which can relieve pressure from blood vessels on the trigeminal nerve. Each of those stages has its own scope, and a first-visit receipt or verbal figure may cover only the consultation and tests done that day.
For an overseas patient, the practical risk is planning a trip around a number that later turns out to describe only part of the pathway. The fix is not to demand a single all-in figure at the first meeting. It is to ask for a written scope that states what is included, what is excluded, and what remains undecided until further assessment.
What a written estimate should actually list
Ask the hospital or clinic to put the estimate in writing and to organise it by stage rather than as one lump sum. A useful document names the clinical items under consideration, the ward or facility type if admission is possible, and the professional fees that apply. It should also state clearly which items are not covered, rather than leaving you to discover them later.
The estimate should distinguish hospital charges from any coordination or interpretation fees charged by a separate service. Those are different payees and different documents. If you use a coordination service, its fee should be quoted separately and should not be presented as part of the hospital bill.
Where a decision depends on further tests or on the treating team's judgement, the estimate should say so. A line marked undecided is more honest and more useful than a figure that quietly assumes a particular procedure will go ahead. You can then ask what information would move that line from undecided to confirmed.
- Which clinical stages the estimate covers, and which it does not.
- Whether hospital charges and coordination fees are shown as separate items.
- Which parts depend on further assessment or on the treating team's decision.
- What currency the estimate is written in and when it was prepared.
- Who to contact if a listed item changes before admission.
The clinical details that change the scope
The scope of an estimate follows the clinical picture, so the records you bring directly affect how specific the quote can be. A facial-pain history that describes short, electric-shock-like attacks in a trigeminal distribution points in one direction. A history of constant burning pain, or pain that has changed character, may prompt a different assessment pathway.
Your medicine response is equally relevant. If a medicine has controlled the pain well, the plan may focus on review and adjustment. If response has been partial, or side effects have limited use, the treating team may discuss procedural alternatives. Each alternative carries its own preparation, admission and follow-up requirements, and therefore its own cost scope.
Imaging findings also need careful handling. A scan showing a blood vessel near the trigeminal nerve does not by itself prove the diagnosis or settle whether a procedure is appropriate. The treating clinician has to interpret the images alongside your history and examination. Ask which findings would make a procedure more or less suitable in your case, and ask how that affects the estimate.
Questions to send before you travel
You do not need a complete medical archive to start. A short summary of your facial-pain history, the medicines you have taken and your response to them, plus any relevant imaging reports, is enough for an initial enquiry. After first contact, the team can tell you which additional records would help.
Once you have a written estimate, compare it against the clinical plan rather than against a headline number. A lower figure that covers only the consultation is not comparable with a figure that includes admission and follow-up. Ask what would need to change for the estimate to be revised, and whether revisions are issued in writing.
It is reasonable to ask about evidence-based risk estimates for any proposed procedure, including uncertainty. A responsible clinician can discuss what is known about benefits and risks in general terms without guaranteeing your individual result. What no estimate can do is promise a particular outcome or a pain-free result.
If a procedure such as microvascular decompression is under discussion, ask whether the estimate assumes a standard ward or an international department, since the two routes are quoted differently and the choice affects the total. Ask whether the figure covers the surgeon, the anaesthetist and the hospital separately or as one package, and whether a revision would be issued if the treating team changes the plan after admission.
Send your summary through the enquiry form, email or WhatsApp, and ask the named hospital to confirm in writing which clinical stages its estimate covers. Keep the reply with your travel documents so that any later revision can be checked against the original scope.
If the pain changes character, or new symptoms appear, arrange local assessment before continuing the overseas enquiry. That step protects you and gives the treating team a clearer picture to work from.
- Which procedure, if any, is being considered, and on what basis.
- What the estimate includes for admission, medicines, imaging and follow-up.
- What is excluded, and what is still undecided.
- What records or tests would make the estimate more specific.
- How and when the estimate would be updated if the plan changes.
Separating hospital, coordination and travel costs
Three cost streams are involved in most overseas treatment journeys, and mixing them makes comparison impossible. Hospital charges are paid to the hospital for consultations, tests, treatment, medicines and rooms. Coordination fees, if you use a service, are paid separately for non-clinical help such as appointment arrangements or interpretation. Travel costs, including flights, accommodation and local transport, sit outside both.
Ask each provider for its own written scope. For the hospital, that means the clinical estimate. For a coordination service, that means a clear description of what the fee covers and what it does not. Do not accept a single combined figure that does not show which payee receives which part.
If you are comparing routes, compare like with like. Two estimates are only comparable when they cover the same clinical stages, the same ward or facility type, and the same follow-up assumptions. Where a figure is missing, ask for it in writing rather than estimating it yourself.
What to do next, and what not to delay
Start with a short summary rather than a full archive. Describe your facial pain, list the medicines you have tried and your response, and note any imaging you already have. An initial enquiry is free and does not commit you to buying a proxy consultation or any other service. The hospital, not the coordination team, decides whether assessment or treatment is suitable.
If your pain is worsening, or if you develop new symptoms such as weakness, numbness or difficulty with vision or speech, seek local medical assessment promptly rather than waiting on an overseas enquiry. Trigeminal neuralgia can be severe, and travel planning should not delay necessary care where you are.
When you are ready, ask the named hospital for a written estimate that reflects your own history and the procedure being considered. Ask what is included, what is excluded and what is still undecided. That single document will answer more of your cost questions than any general figure.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.