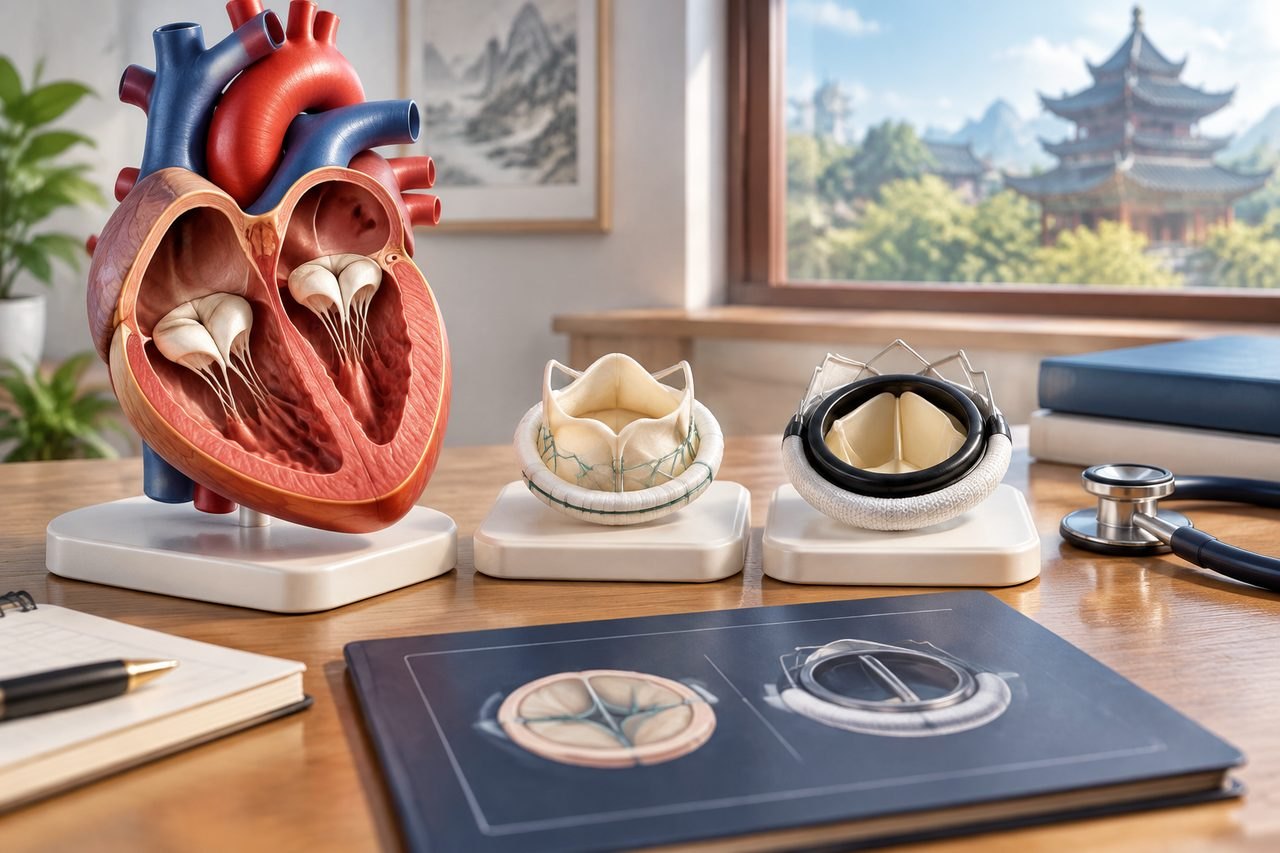
Why the surgeon cannot decide from a report alone
A transthoracic echocardiogram report gives numbers: valve area, gradient, regurgitant volume, chamber dimensions. Those numbers tell the cardiologist how severe the problem is. They do not tell the surgeon whether the leaflets are pliable enough to reshape, whether the annulus can hold a ring, or whether infection has eaten into tissue. That information comes from a transesophageal echocardiogram, sometimes a cardiac CT, and from looking at the valve directly in the operating room.
This is why two surgeons can read the same report and reach different conclusions. One may see a repairable mitral valve; another may see calcification that makes repair unreliable. Neither is wrong before surgery. The disagreement reflects genuine uncertainty that only direct inspection resolves.
For an overseas patient, this matters practically. If you send records to a hospital in China and receive a tentative plan, treat that plan as provisional. The surgeon will confirm or change it after seeing your imaging in full resolution and, in some cases, after opening the chest. Ask the coordinator to state clearly which parts of the plan are confirmed and which depend on intraoperative findings.
What repair actually involves, and why surgeons prefer it when feasible
Repair means the surgeon works with your own valve tissue. For a mitral valve, this might mean resecting a prolapsed segment, placing artificial chords, and implanting an annuloplasty ring to reshape the base of the valve. For a tricuspid valve, repair often means tightening the annulus. For an aortic valve, repair is less common but possible in selected cases, particularly in younger patients or those with aortic insufficiency from a specific cause.
The attraction of repair is biological. Your own tissue does not clot the way mechanical prostheses do, and it does not degenerate the way bioprosthetic tissue can. A successful repair may avoid lifelong anticoagulation, which matters for women who may become pregnant, for people at high bleeding risk, and for anyone who wants to avoid the monitoring burden of warfarin.
But repair is not automatically better. A repair that leaks or narrows again within a year is worse than a replacement that works. Surgeons therefore weigh the probability of a durable repair against the risks of the alternatives. That probability depends on the valve involved, the mechanism of dysfunction, the surgeon's own experience with that specific anatomy, and whether the tissue looks favourable on imaging.
When replacement becomes the more defensible choice
Replacement removes the diseased valve and sews in either a mechanical prosthesis or a bioprosthesis made from animal tissue. Mechanical valves last a long time but require anticoagulation, typically with warfarin, and the associated monitoring and bleeding risk. Bioprosthetic valves avoid long-term anticoagulation for most people but have a finite lifespan and may need replacement later, especially in younger patients.
Surgeons lean toward replacement when the valve is heavily calcified, when infection has destroyed the annulus, when the valve is congenitally malformed in a way that repair cannot correct, or when the patient's overall condition makes a shorter, more predictable operation safer. They also consider replacement when the surgeon's own repair results for that valve type are not strong, or when the patient cannot reliably take or monitor anticoagulation.
The mechanical-versus-bioprosthetic decision is separate from the repair-versus-replacement decision. A patient may be a repair candidate but still need to choose between a mechanical and tissue prosthesis if repair fails. Ask the surgeon to explain both decisions, not just the first one.
A planning example: how the reasoning changes with the valve
Consider two hypothetical patients, neither based on a real case. The first is a 52-year-old with severe mitral regurgitation from posterior leaflet prolapse, normal heart function, no coronary disease. A surgeon might reasonably discuss repair as a possible route, because this anatomy is often favourable and the patient is young enough that avoiding anticoagulation matters. Whether repair is feasible and how long it would last are questions for the operating surgeon, not conclusions from the report.
The second is a 74-year-old with aortic stenosis, a calcified bicuspid valve, and moderate coronary disease. Repair may be less likely to hold here. The surgeon might lean toward replacement, and the conversation would shift to whether a bioprosthesis or mechanical valve fits the patient's age, bleeding risk, and willingness to take warfarin. Again, the recommendation depends on direct inspection and the surgeon's own experience with that anatomy.
These examples show that the same question — repair or replace? — produces different answers depending on the valve, the mechanism, the patient's age, and the presence of other heart disease. They are not recommendations. They illustrate the variables a surgeon weighs and the questions you should be prepared to ask.
Questions that change the next step before you travel
The answers to these questions determine whether you can plan surgery in China with reasonable confidence or whether you need more imaging first.
Ask the surgeon or coordinating team: Which valve is involved, and what is the mechanism of dysfunction? Is repair technically feasible based on my imaging, and what is the chance it will hold? If repair is not feasible, which prosthesis would you recommend and why? What imaging do you still need before a final plan? Will the final decision be made before or during surgery? What is your own experience with this specific repair?
If the team cannot answer these questions from your records, they may ask for a transesophageal echocardiogram, a cardiac CT, or a repeat study. That is not a delay tactic; it is how the surgeon reduces uncertainty. Ask what specific images or measurements would change the recommendation, and arrange to send those.
Also ask how the hospital handles the consent conversation. You should understand the planned operation, the alternatives, and the possibility that the plan changes once the surgeon sees the valve. If you need an interpreter for that conversation, request one in advance.
What to prepare and what remains uncertain
For an initial enquiry, a brief summary is enough: which valve, what the echocardiogram showed, your symptoms, your age, other diagnoses, and your main question. You do not need to send a complete archive at first contact. After the team reviews the summary, they will tell you which records or images to send next.
Useful records typically include the full echocardiogram report and images, any cardiac catheterisation or CT studies, a list of current medicines, and relevant surgical or medical history. Whether the hospital needs the images on disc, via a portal, or in another format is a question to confirm with the coordinator, not a fixed rule.
What remains uncertain until the surgeon reviews everything: whether repair is feasible, which prosthesis is appropriate if replacement is needed, and whether the hospital accepts your case. A records-based opinion can clarify the reasoning and the remaining questions, but it does not replace the surgeon's direct assessment and does not confirm acceptance in advance or a specific outcome.
Costs also depend on the final plan. Repair and replacement involve different prostheses, different operative times, and different hospital stays. Ask the hospital for a written estimate that states what is included, what is excluded, and what remains undecided until the surgical plan is confirmed. Coordination fees are separate from hospital charges.
Sources & scope of this guide
References and official service information relevant to this guide.
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.