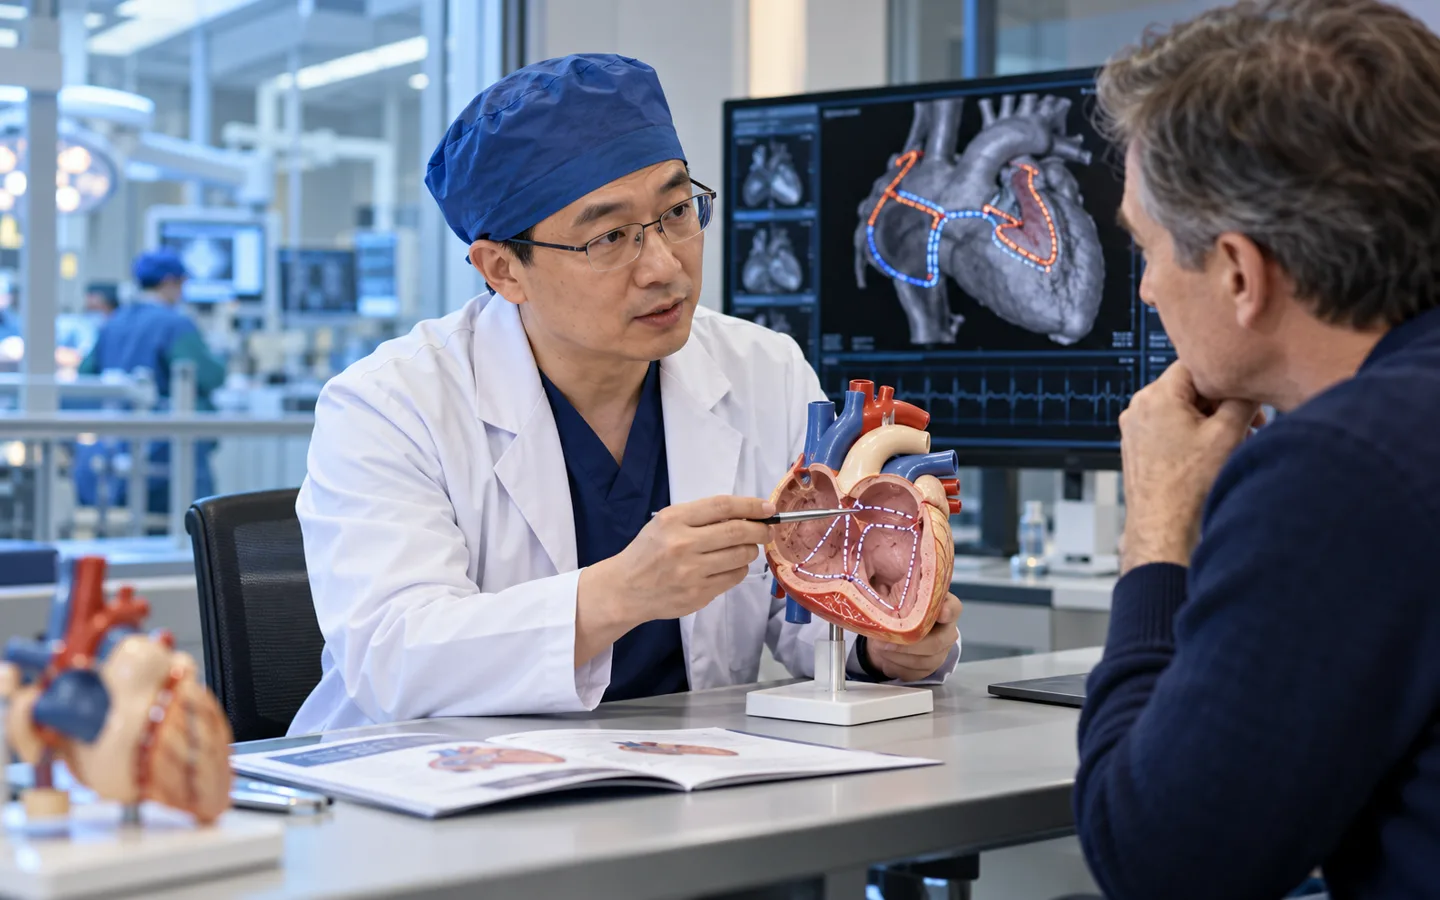
The Maze procedure creates controlled barriers to abnormal atrial signals
Surgeons use surgical incisions or energy sources to create a planned lesion pattern in the atria. Healed tissue redirects electrical activity and can reduce atrial fibrillation.
It is often considered during another open cardiac operation. Stand-alone minimally invasive surgical ablation may be considered in selected patients after specialist rhythm review.
Even if sinus rhythm returns, anticoagulation decisions still depend on stroke risk, rhythm monitoring and clinician assessment.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about surgical atrial fibrillation ablation.
- Symptomatic atrial fibrillation in a patient already undergoing valve or other cardiac surgery.
- Persistent or long-standing AF where catheter and medicine strategies are inadequate.
- Selected patients considered for stand-alone surgical or hybrid ablation.
- A left atrial appendage strategy being considered with cardiac surgery.
What the specialist team must confirm
Review includes ECG and rhythm-monitoring history, AF duration and symptoms, atrial size, valve disease, ventricular function, prior ablation, stroke and bleeding risk, anticoagulation tolerance and the indication for any accompanying operation.
Key points for this treatment
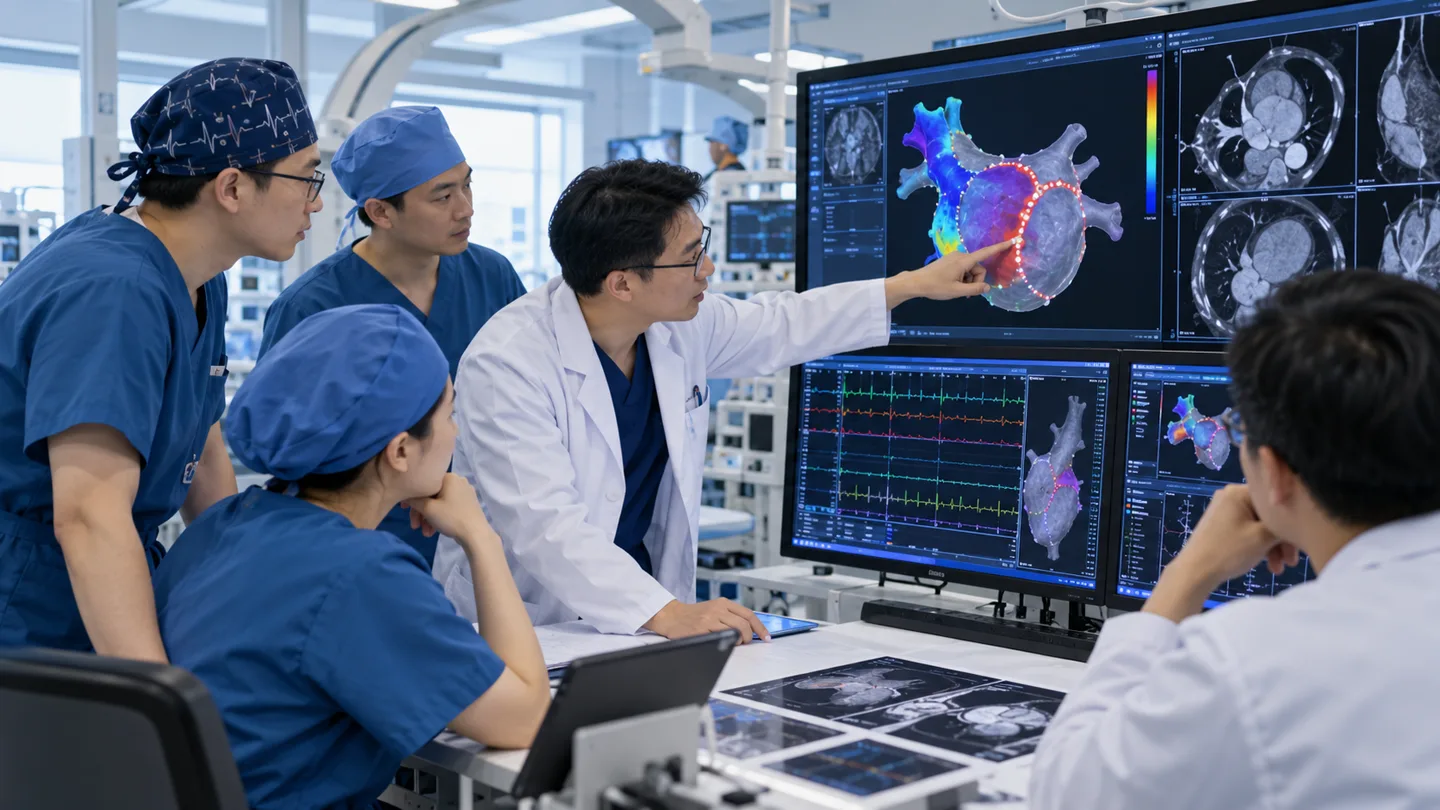
From rhythm documentation to combined surgical planning
The team separates symptom-control goals from stroke prevention and considers whether the Maze adds enough benefit to the planned operation.
Rhythm may evolve during healing
Early atrial arrhythmias can occur while tissue heals. Medicines, cardioversion or pacing decisions may be needed during this period.
Longer-term follow-up uses symptoms, ECG or ambulatory monitoring and stroke-risk review rather than assuming that the procedure permanently eliminates AF.

Risks, limits and realistic expectations
The Maze procedure may not eliminate AF and can cause bleeding, infection, stroke, atrial flutter, sinus-node dysfunction, pacemaker need and the risks of open cardiac surgery. Benefit depends on patient selection and lesion completeness.
Chest pain, severe breathlessness, fainting, stroke symptoms or sustained rapid rhythm requires urgent local assessment.