
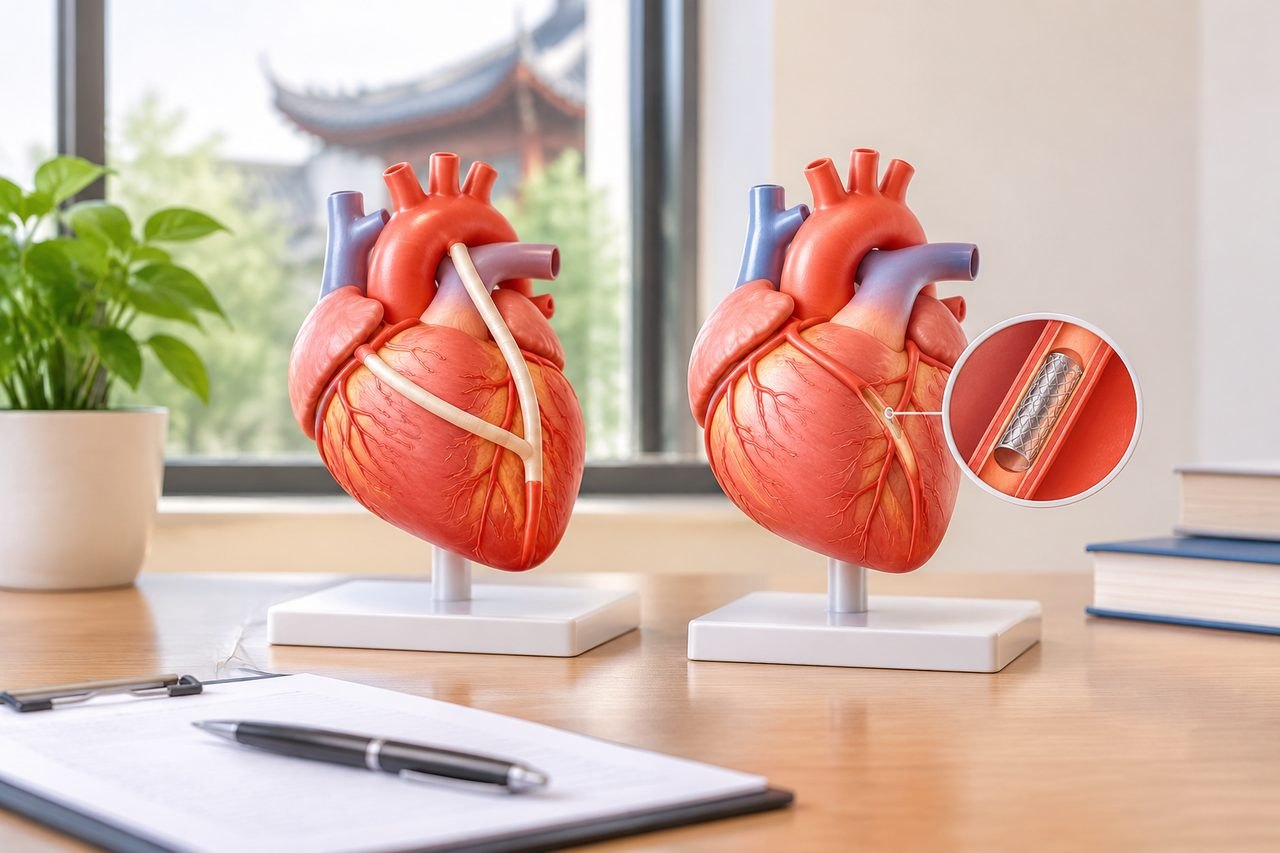
The core difference: a new route versus opening the original artery
Coronary artery bypass grafting, usually called CABG, is open heart surgery. The surgeon uses a blood vessel taken from elsewhere, often the chest wall or the leg or arm, to carry blood around a narrowed or blocked section of a coronary artery. The original artery is left in place. Blood reaches the heart muscle through the graft instead. Because the chest is opened and the heart is often stopped briefly with a heart-lung machine, CABG is a major operation with a hospital stay and a recovery period measured in weeks rather than days.
Coronary stenting is part of percutaneous coronary intervention, or PCI. It is usually done through a catheter threaded from an artery in the wrist or groin to the heart. A balloon opens the narrowing, and a small metal mesh tube, the stent, is left in place to hold the artery open. There is no chest incision and no graft. Most patients are awake or lightly sedated, and many go home within a short time, although the exact schedule is set by the treating team.
The practical consequence is that the two treatments differ in invasiveness, in what they physically change, and in what follow-up they require. Stenting keeps the original artery as the blood channel and relies on the stent staying open. Bypass relies on the graft and on the heart's ability to adapt to surgery. Both need ongoing medical therapy and risk-factor control afterwards.
Why the choice is not simply 'the newer one' or 'the less invasive one'
A common assumption is that stenting is always the modern, gentler option and bypass is reserved for people who are too unwell for anything else. That is not how the decision works. For some patterns of coronary disease, bypass offers more durable results; for others, stenting is entirely appropriate and avoids major surgery. The anatomy matters more than the patient's preference alone.
International guidance, including from the European Society of Cardiology and the American College of Cardiology and American Heart Association, ties the recommendation to how many coronary arteries are diseased, where the narrowings sit, whether the left main coronary artery is involved, whether the disease is diffuse or focal, and how well the left ventricle is pumping. Diabetes, kidney function, previous heart procedures, age, frailty and other illnesses also enter the discussion. A heart team, typically interventional cardiologists and cardiac surgeons reviewing the same images together, is the usual setting for a complex decision.
This is why a patient who asks 'which is better?' rarely gets a single answer. The better question is 'which is better for this pattern of disease in this person, and what are the trade-offs?' That question belongs to the treating clinicians who can see the angiogram and the full clinical picture.
What each option asks of the patient afterwards
After stenting, antiplatelet medicines are typically needed to reduce the risk of the stent clotting, and the duration and combination are decided by the treating cardiologist. Patients also need control of blood pressure, cholesterol, blood sugar and smoking. Stents can narrow again over time, and repeat procedures are sometimes needed. The treating team should explain the specific risks for the individual, including bleeding risk and the possibility of restenosis.
After bypass, recovery involves a hospital stay, a period of reduced activity, wound care for the chest and graft sites, and a structured return to normal activity. Grafts can also fail over the long term, and bypass does not remove the underlying artery disease, so the same medical therapy and lifestyle changes apply. Cardiac rehabilitation is often part of recovery, and its availability and format should be confirmed with the treating hospital.
Neither treatment cures coronary artery disease. Both are ways of improving blood supply while long-term medical management continues. Patients should ask their clinicians about expected recovery, activity limits, driving, flying and return to work, because these depend on the operation, the person and the treating team's instructions rather than on a standard timetable.
What a patient considering care in China should clarify first
For an international patient, the clinical decision and the practical arrangements are separate questions. The first is whether the coronary anatomy and overall health make bypass, stenting or another approach appropriate. That requires the angiogram images and report, not just a written summary, along with records of heart function, kidney function, diabetes control, previous heart attacks or procedures, current medicines and allergies. A receiving hospital will want to review these before offering an opinion.
The second question is what the hospital can actually offer and on what terms. Patients should ask whether the hospital has a heart team that reviews complex cases, whether both bypass and stenting are available on site, who would perform the procedure, and what the written plan and fee scope include. It is reasonable to ask how many of the relevant procedures the team performs, although the answer should be treated as context rather than a guarantee.
A records-based review can help a patient understand the options before travelling, but it does not replace the hospital's own assessment and does not confirm acceptance or a final treatment plan. The hospital decides suitability after reviewing the case. An initial enquiry through ChinaSpecialistCare is free and asks only for a brief summary, not a complete medical archive or payment details.
Costs and coordination: what is known and what to confirm
Cost is a real part of the decision, but it should not be the first filter. Bypass and stenting differ in what they involve, so a meaningful comparison starts with the clinical recommendation and then asks what that recommendation would cost at a named hospital. Published reference ranges for the two procedures are indicative only, not fixed or guaranteed quotes, and they are not China-wide averages. The final figure depends on the individual assessment, the treatment plan, the hospital, the materials and devices used, and the services included. A final quote may fall outside any published range.
The ranges do not tell a patient what is included. Anaesthesia, tests, medicines, hospital stay, intensive care, follow-up and coordination are not confirmed as included or excluded by the range alone. Patients should ask the named hospital for a written quote that lists what the fee covers and what is billed separately. ChinaSpecialistCare's own coordination and interpretation fees are separate from hospital charges and are not offset against later treatment.
Travel, accommodation and companion costs are separate again. Patients should not assume that a lower procedure figure means a lower total cost, because the scope of care and the length of stay differ between bypass and stenting. The right comparison is between written plans for the same clinical situation, not between headline numbers.
Questions worth putting to the treating team
Before committing to either route, a patient can ask a focused set of questions. Which coronary arteries are affected, and is the left main artery involved? Is the disease focal or diffuse? What is the heart's pumping function? Does diabetes or kidney disease change the recommendation? What are the expected benefits and risks of each option for this individual? What follow-up and medicines will be needed, and for how long?
It also helps to ask what would happen if the first choice did not work, and whether the hospital can manage complications of either approach. Patients should ask who makes the final decision and how the heart team's recommendation is documented. These are clinical questions, and the answers belong to the treating clinicians, not to a coordination service.
For practical planning, patients can ask the hospital what records it needs, how images should be sent, what language support is available, and what the written plan and quote will contain. ChinaSpecialistCare can help with appointment coordination, interpretation and hospital navigation once a patient decides to proceed, but it does not make clinical decisions or guarantee acceptance.
Sources & scope of this guide
References and official service information relevant to this guide.
- Related treatment reference
- ACC/AHA/SCAI Coronary Revascularization Guideline: Key Perspectives
- Coronary artery bypass graft
- Coronary angioplasty and stent insertion
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.