
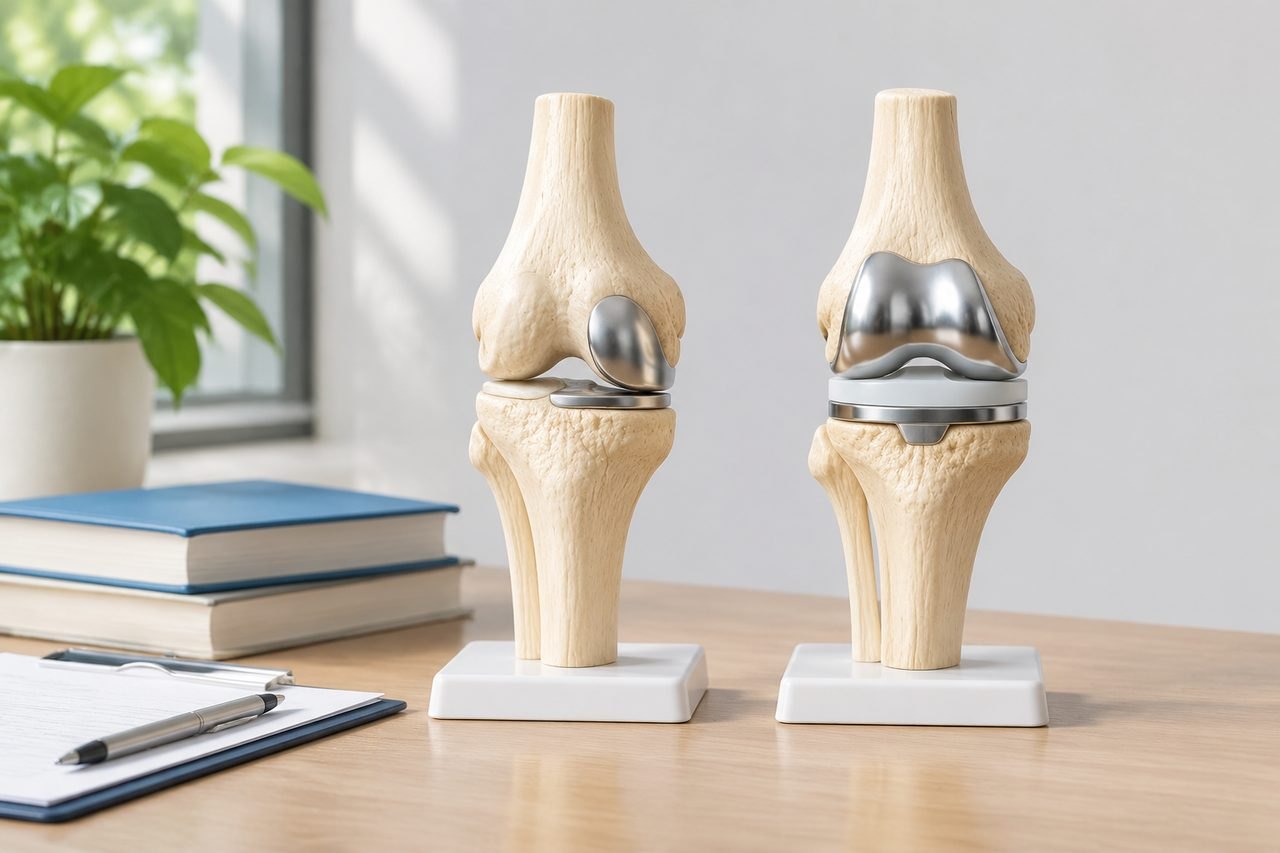
The core difference is how much of the knee is replaced
Both operations replace worn joint surfaces with implanted components. The difference is scope. A partial (unicompartmental) knee replacement replaces the damaged surface in one compartment of the knee, most commonly the inner side. The healthy cartilage, the other compartments and, in suitable knees, the cruciate ligaments are left in place. A total knee replacement replaces the surfaces of all three compartments and typically involves the anterior cruciate ligament.
That difference matters because a partial replacement is only appropriate when the damage is genuinely confined to one compartment. If arthritis or wear affects more than one area, a partial implant would leave diseased surfaces behind. A total replacement addresses the whole joint but removes more tissue and changes the mechanics of the knee more extensively.
Neither operation is automatically better. Each has a defined role, and the surgeon's job is to match the operation to the pattern of disease rather than to offer the smaller procedure because it sounds less invasive.
Who each operation may suit, and what has to be confirmed
Partial knee replacement is generally considered when the wear is limited to one compartment, the ligaments that stabilise the knee are functioning, the alignment is not severely deformed and the patient's symptoms fit that pattern. It is not suitable for inflammatory arthritis affecting the whole joint, for significant wear in more than one compartment, or where ligament function is poor.
Total knee replacement is considered when more than one compartment is worn, when deformity or ligament problems make a partial implant unreliable, or when the surgeon judges that the whole joint needs resurfacing. It is also the usual choice when a previous partial replacement has failed and needs revision.
These are general principles, not a checklist that decides your case. Body weight, age, activity level, previous surgery and the condition of the kneecap surface all enter the discussion. Ask the surgeon to explain, using your imaging, which compartments are affected and why one operation is being recommended over the other. The hospital, not the patient or a coordinator, decides suitability.
What imaging and records actually show
The decision rests on weight-bearing X-rays, which show the pattern of joint-space narrowing and alignment, and often on MRI or other imaging to assess ligaments and cartilage. A standing long-leg view can show the overall mechanical alignment. These are the records a knee surgeon will want to review.
If you are seeking care in China, gather your existing imaging on disc or as original files, not only a written report, plus any operation notes and clinic letters. Ask whether the receiving team wants repeat imaging in China; do not assume your home scans will be accepted without review. A records-based opinion can discuss the likely options, but it cannot replace the physical examination and the surgeon's own assessment of ligament function and alignment.
Be cautious about any service that offers to choose the implant type from a report alone. The distinction between partial and total is a clinical judgement made with the patient in front of the surgeon.
Recovery, risks and the trade-offs patients ask about
Patients often assume a partial replacement means a faster, easier recovery. That may be part of the reasoning behind offering it in selected knees, but it is not a guarantee, and recovery depends on the individual, the surgical approach and rehabilitation. Do not plan around a fixed number of days in hospital or a fixed return to work; ask the treating team what to expect in your case.
Both operations carry risks including infection, blood clots, stiffness, implant wear or loosening, and the possibility that further surgery is needed. A partial replacement can be revised to a total replacement if arthritis progresses in the other compartments, but revision surgery is generally more complex than a first operation. A total replacement is a larger procedure with its own recovery demands.
The honest trade-off is this: a partial replacement preserves more of your own knee but depends on the disease staying confined; a total replacement treats the whole joint but is a bigger operation. Your surgeon should discuss both, including the evidence for each in knees like yours, rather than presenting one as the default.
Questions to bring to a knee surgeon in China
A productive consultation is built on specific questions. Ask which compartments are worn and how the imaging shows this. Ask whether your ligaments and alignment make a partial implant reliable. Ask what would make the surgeon change the plan during surgery, and whether a total replacement would then be performed in the same session.
Ask about the implant, the approach, expected rehabilitation and who provides it, and what follow-up is arranged after you return home. Ask what the written treatment plan and fee quote include, since hospital charges, implants, tests, stay and follow-up are confirmed by the treating provider rather than assumed. If you are comparing hospitals, compare the same scope of assessment and the same written plan.
You can begin with a short summary of your knee problem and your main question. An initial enquiry is free and does not require buying a proxy consultation; a records-based opinion is optional and does not establish hospital acceptance or final surgical eligibility.
Next step
If you are weighing partial against total knee replacement, the useful next step is to gather your weight-bearing X-rays, any MRI and your clinic notes, then ask a knee surgeon to explain which compartments are affected and why one operation fits your knee. ChinaSpecialistCare can help you prepare that summary and identify an appropriate orthopedic route; the clinical decision remains with the treating surgeon and hospital. You can start with a brief enquiry and share records after first contact.
Before that conversation, it helps to know what each operation actually changes inside the knee, because the words partial and total describe scope rather than quality. A partial (unicompartmental) replacement resurfaces the worn surface of one compartment, most commonly the inner side, and leaves the other compartments and, in suitable knees, the cruciate ligaments in place. A total replacement resurfaces all three compartments and typically involves the anterior cruciate ligament. Neither is the better operation in the abstract; each has a defined role, and the surgeon's task is to match the operation to the pattern of wear rather than to offer the smaller procedure because it sounds less invasive.
That match depends on findings, not preference. Partial replacement is generally considered when wear is confined to one compartment, the stabilising ligaments work, alignment is not severely deformed and symptoms fit that pattern. It is not suitable for inflammatory arthritis affecting the whole joint, for significant wear in more than one compartment, or where ligament function is poor. Total replacement is considered when more than one compartment is worn, when deformity or ligament problems make a partial implant unreliable, or when a previous partial replacement has failed and needs revision. Body weight, age, activity level, previous surgery and the condition of the kneecap surface all enter the discussion, so ask the surgeon to point to your imaging and explain which compartments are affected and why one operation is being recommended over the other.
The records that support this discussion are specific. Weight-bearing X-rays show the pattern of joint-space narrowing and alignment, a standing long-leg view can show overall mechanical alignment, and MRI or other imaging may be used to assess ligaments and cartilage. If you are seeking care in China, bring your imaging as original files or discs rather than only a written report, plus any operation notes and clinic letters, and ask whether the receiving team wants repeat imaging in China rather than assuming your home scans will be accepted without review. A records-based opinion can discuss likely options, but it cannot replace the physical examination and the surgeon's own assessment of ligament function and alignment. Be cautious about any service that offers to choose the implant type from a report alone.
Patients often assume a partial replacement means a faster, easier recovery. That may be part of the reasoning behind offering it in selected knees, but it is not a guarantee, and recovery depends on the individual, the surgical approach and rehabilitation. Do not plan around a fixed number of days in hospital or a fixed return to work; ask the treating team what to expect in your case. Both operations carry risks including infection, blood clots, stiffness, implant wear or loosening, and the possibility that further surgery is needed. A partial replacement can be revised to a total replacement if arthritis progresses in the other compartments, but revision surgery is generally more complex than a first operation, and a total replacement is a larger procedure with its own recovery demands. The honest trade-off is that a partial replacement preserves more of your own knee but depends on the disease staying confined, while a total replacement treats the whole joint but is a bigger operation.
A productive consultation is built on specific questions. Ask which compartments are worn and how the imaging shows this. Ask whether your ligaments and alignment make a partial implant reliable. Ask what would make the surgeon change the plan during surgery, and whether a total replacement would then be performed in the same session. Ask about the implant, the approach, expected rehabilitation and who provides it, and what follow-up is arranged after you return home. Ask what the written treatment plan and fee quote include, since hospital charges, implants, tests, stay and follow-up are confirmed by the treating provider rather than assumed. If you are comparing hospitals, compare the same scope of assessment and the same written plan. An initial enquiry is free and does not require buying a proxy consultation; a records-based opinion is optional and does not establish hospital acceptance or final surgical eligibility.
Sources & scope of this guide
References and official service information relevant to this guide.
- Related treatment reference
- American Academy of Orthopaedic Surgeons: Unicompartmental Knee Replacement
- National Institute for Health and Care Excellence: Joint replacement (primary): hip, knee and shoulder
This is general planning information and has not been individually reviewed by a doctor. Medical decisions and personal treatment advice come from your treating clinicians.