
Aortic dissection separates layers of the aortic wall
Blood enters a tear in the aortic lining and creates a false channel. Dissection involving the ascending aorta usually needs emergency surgery because rupture, tamponade, valve failure and organ ischemia can occur.
Descending dissection is managed according to complications, anatomy and chronic evolution. Some patients need medical therapy, endovascular repair or later open reconstruction rather than immediate surgery.
Suspected acute dissection should be managed at the nearest capable emergency centre. International record review must never delay stabilization or transfer.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about aortic dissection surgery.
- Acute ascending or arch dissection requiring emergency repair.
- Complicated descending dissection with rupture or malperfusion.
- Chronic residual dissection with aneurysmal enlargement.
- Previous repair requiring staged arch, branch or downstream aortic treatment.
What the specialist team must confirm
The team reviews emergency CT angiography from neck to pelvis, entry tear, true and false lumen, branch-vessel perfusion, valve and coronary involvement, neurologic and organ status, blood pressure and any previous aortic grafts or stents.
Key points for this treatment
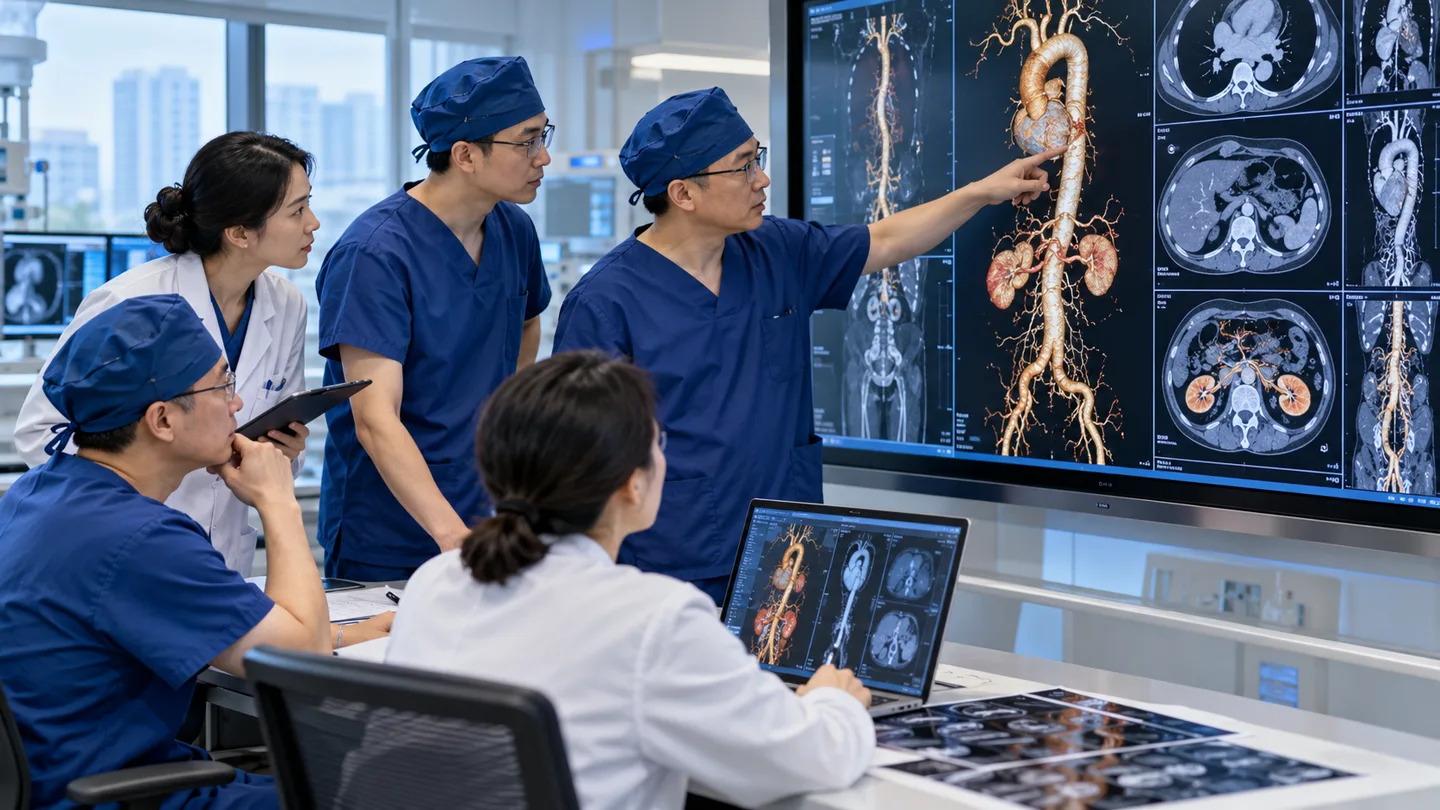
From emergency stabilization to staged aortic care
The operation is tailored to the life-threatening segment while preserving options for downstream repair.
Survival leads into lifelong dissection care
After surgery, teams monitor neurologic, kidney, bowel, limb and cardiac function as well as bleeding and infection.
CT or MRI surveillance follows the repaired and residual aorta. Blood-pressure control, medication adherence and assessment of inherited aortopathy are central.

Risks, limits and realistic expectations
Emergency surgery carries substantial risks including bleeding, stroke, organ failure, spinal-cord injury, infection, reoperation and death. Even successful repair does not eliminate disease in the remaining aorta.
Sudden tearing chest or back pain, collapse, new weakness, absent pulse or severe abdominal pain requires emergency services immediately.