
Stage describes disease extent at a defined point in the journey
Cancer stage summarizes where the tumour started, its local extent, regional lymph-node involvement and whether it has spread to distant sites. Stage helps the team discuss prognosis, treatment intent, sequencing and clinical-trial eligibility, but it does not by itself prescribe one treatment.
Clinical stage uses examinations, imaging, biopsy and other tests available before definitive surgery. Pathologic stage adds findings from resected tissue and lymph nodes. After preoperative treatment, response is recorded with additional staging notation. At recurrence, clinicians describe the new extent while preserving the original stage assigned at diagnosis.
The reviewer must know the exact cancer type, the date and purpose of every study, what treatment occurred between scans and which staging system applies. Brain tumours, blood cancers and several other diseases do not follow the same TNM pathway.
Who may benefit from review?
A coordinated staging review may help when:.
- A new diagnosis has been confirmed but the extent of disease is incomplete or unclear.
- Outside reports use different stage labels or disagree about lymph nodes or distant lesions.
- A major operation, radiotherapy plan or systemic-treatment sequence depends on resectability and disease extent.
- Imaging after treatment must distinguish response, residual disease, progression or treatment effect.
- A patient is considering international care and needs to know which missing tests should be completed before travel.
What the hospital needs to assess
The team reconciles the pathology diagnosis, tumour site and applicable staging edition, then reviews original CT, MRI, PET, ultrasound, nuclear medicine or other relevant images—not only their translated reports. Examination findings, endoscopy, operative notes, laboratory results and previous treatment are added when the cancer type requires them.
Key points for this treatment
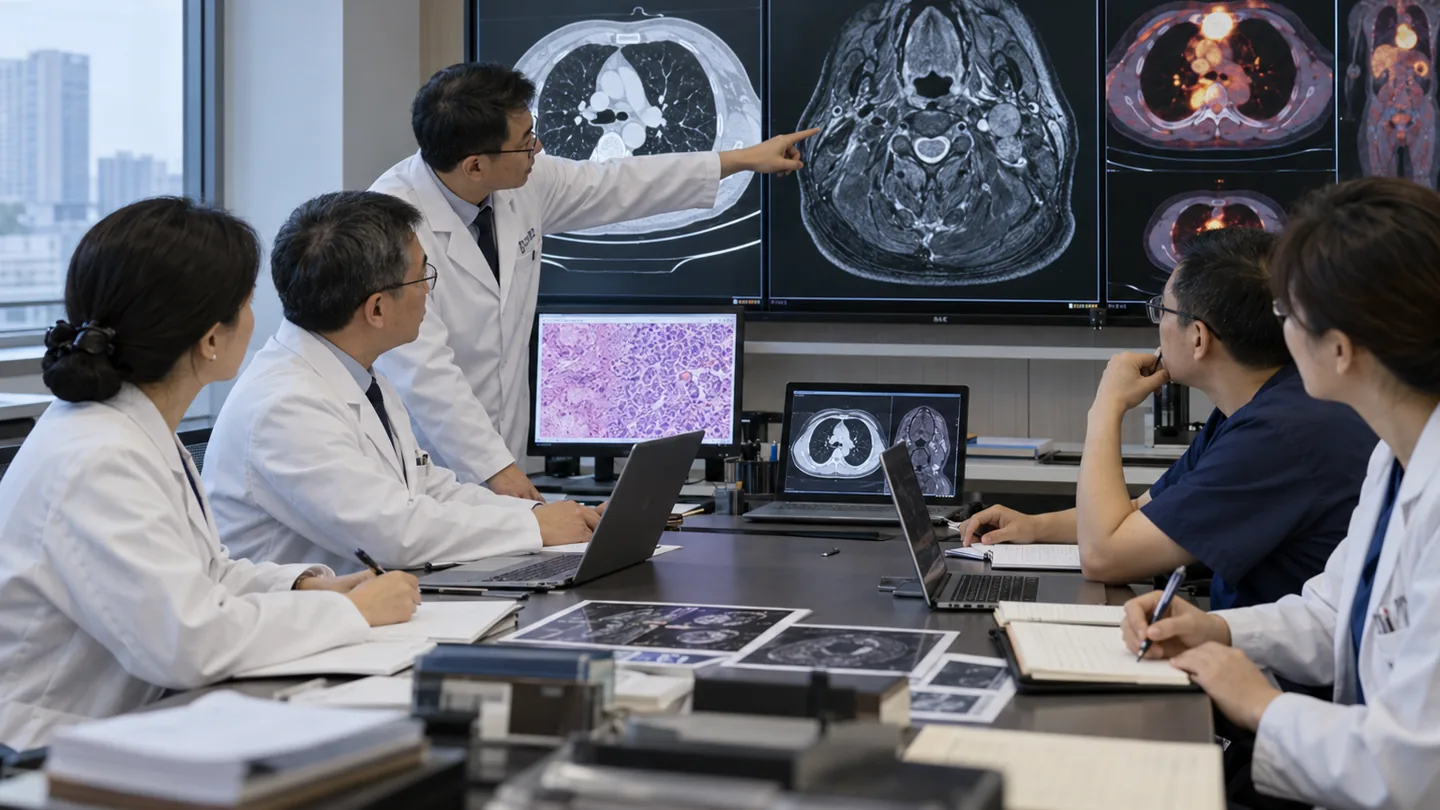
How a staging review reaches a usable conclusion
First, the diagnosis and primary site are confirmed because the staging system depends on tumour type. The radiologist and disease-specific team then map the primary tumour, regional nodes and possible distant disease. Suspicious findings may need targeted imaging, biopsy or short-interval follow-up when certainty would change treatment.
The final review should state the staging system and evidence used, clarify whether the stage is clinical or pathologic, list unresolved findings and explain how uncertainty affects the next decision. Multidisciplinary discussion is especially important when surgery, radiation and systemic therapy could be sequenced in different ways.
After staging: intent, sequencing and follow-up
The care team uses stage together with tumour biology, symptoms, organ function and patient goals to discuss curative, disease-controlling or symptom-relieving treatment. Two patients with the same stage may still receive different recommendations because the disease subtype and individual health differ.
Baseline measurements and imaging technique should be recorded for later comparison. Follow-up scans are scheduled according to the cancer and treatment—not simply repeated as often as possible. New symptoms between planned scans may require earlier local assessment.

Limitations and realistic expectations
Imaging has resolution limits, and inflammation, infection or treatment effect can resemble cancer. Very small deposits may not be visible; suspicious findings may remain indeterminate. Missing DICOM studies, incomplete scan coverage or treatment between examinations can prevent reliable comparison. Stage is a population-based framework, not an exact prediction for one person, and staging review cannot guarantee resectability or treatment outcome.
New weakness, loss of bladder or bowel control, severe breathlessness, coughing blood, uncontrolled bleeding, confusion, seizure, bowel obstruction or rapidly worsening pain requires urgent local assessment rather than waiting for an overseas staging opinion.