
A second review checks the evidence behind the diagnosis
The pathology report usually provides the definitive cancer diagnosis. It describes what tissue was examined and may include tumour type, grade, margins, lymph-node findings and biomarker results. Treatment choices can change when any of these elements change.
An expert review is not simply a rereading of the written report. A specialist pathologist examines the original glass slides and, when needed, requests paraffin blocks or unstained slides for additional work. The findings must be interpreted with the biopsy site, imaging, operation and treatment history.
Ask the original laboratory what can be released, whether original slides must be returned and how blocks should be shipped. Confirm the receiving hospital’s specimen and customs instructions before sending irreplaceable material.
Who may benefit from review?
A pathology review may be especially useful when the result will change a major treatment decision or when the diagnosis is difficult to classify. Examples include:.
- A newly diagnosed rare tumour, sarcoma, lymphoma, brain tumour or unusual subtype.
- A proposed operation, chemotherapy or radiotherapy plan that depends on exact histology or grade.
- Different reports that disagree about tumour type, grade, margins or biomarker status.
- A recurrence, new lesion or unexpected clinical course that may represent a different process.
- A small or poor-quality sample where the report states that the diagnosis is limited or uncertain.
What the hospital needs to assess
The reviewing service needs the complete pathology chain: the original report, representative H&E slides, existing immunohistochemistry, paraffin blocks or unstained slides when requested, and relevant molecular results. Operative notes, imaging and prior treatment help the pathologist decide whether the sample represents the target lesion and whether more tissue is needed.
Key points for this treatment
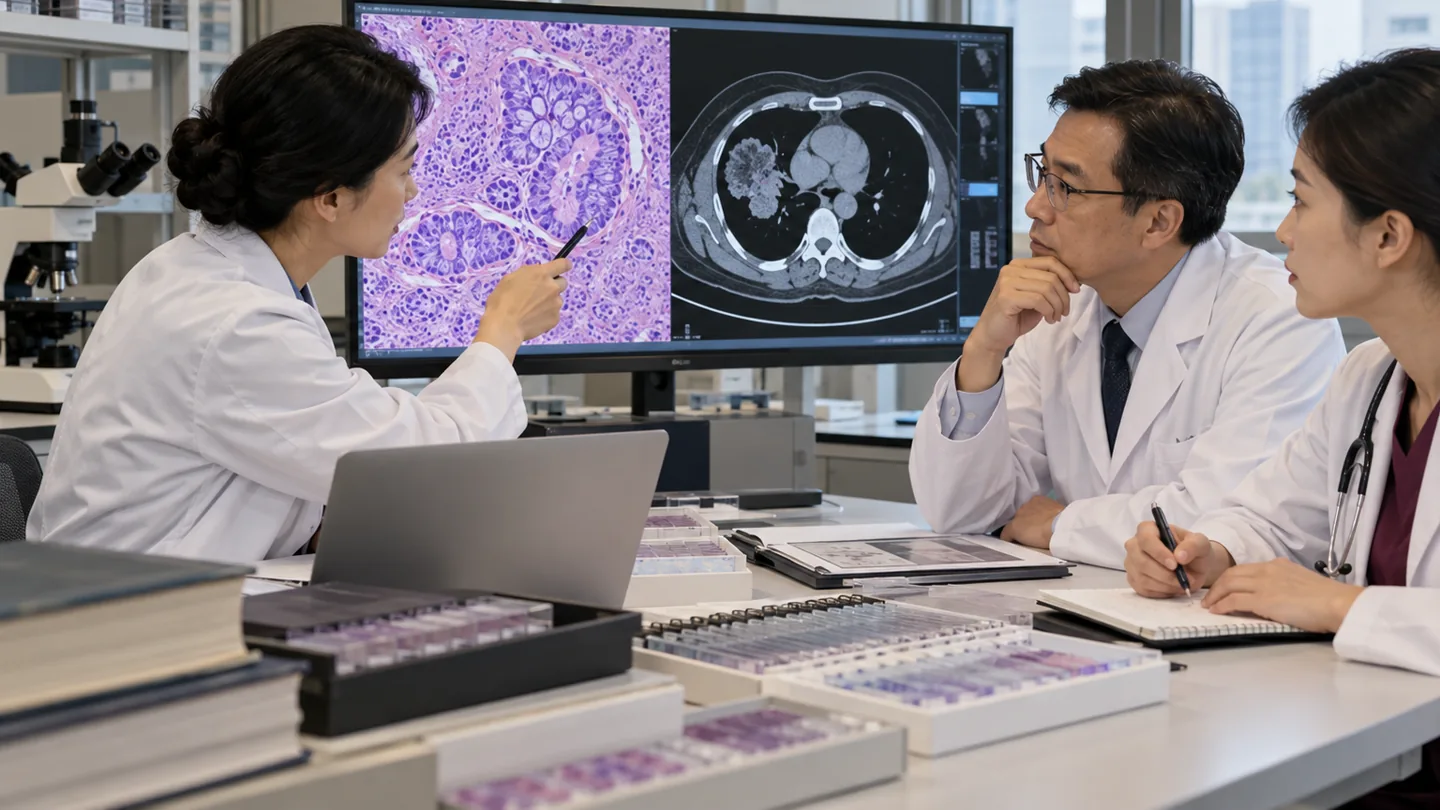
How the review is organized
The receiving laboratory logs the material, verifies patient and specimen identifiers and checks that the slides match the submitted report. A pathologist with relevant subspecialty experience reviews morphology and previous ancillary tests. If the question remains unresolved, the team may recommend selected immunohistochemistry, special stains or molecular testing rather than repeating every test.
The final opinion may confirm the original diagnosis, refine the subtype or grade, document a meaningful disagreement, or state that the available material is insufficient. The result should then be interpreted by the treating oncology team; a pathology label alone does not select treatment without stage, health status and treatment history.
After the review: decisions and next steps
Straightforward reviews may be completed after the submitted slides are examined. Additional stains, retrieval of blocks, molecular testing or consultation among several pathologists can extend the timeline. Do not assume a deadline until the laboratory confirms that all required material has arrived.
If the diagnosis changes, the oncology team should revisit staging and treatment rather than acting on one sentence in isolation. If the tissue is exhausted or does not answer the clinical question, a new biopsy may be discussed, but only after clinicians compare its expected value and procedural risk.

Limitations and realistic expectations
A second review can still be limited by scant tissue, crush or fixation artifact, missing slides, treatment effect, tumour heterogeneity or an unrepresentative biopsy. Shipping can delay care and irreplaceable material can be damaged or lost. Expert review may narrow uncertainty without producing a single definitive answer, and a changed diagnosis does not guarantee that another treatment is available or appropriate.
Do not postpone urgent local assessment for severe bleeding, breathing difficulty, spinal-cord symptoms, bowel obstruction, rapidly worsening pain or another acute problem while arranging an overseas pathology review.