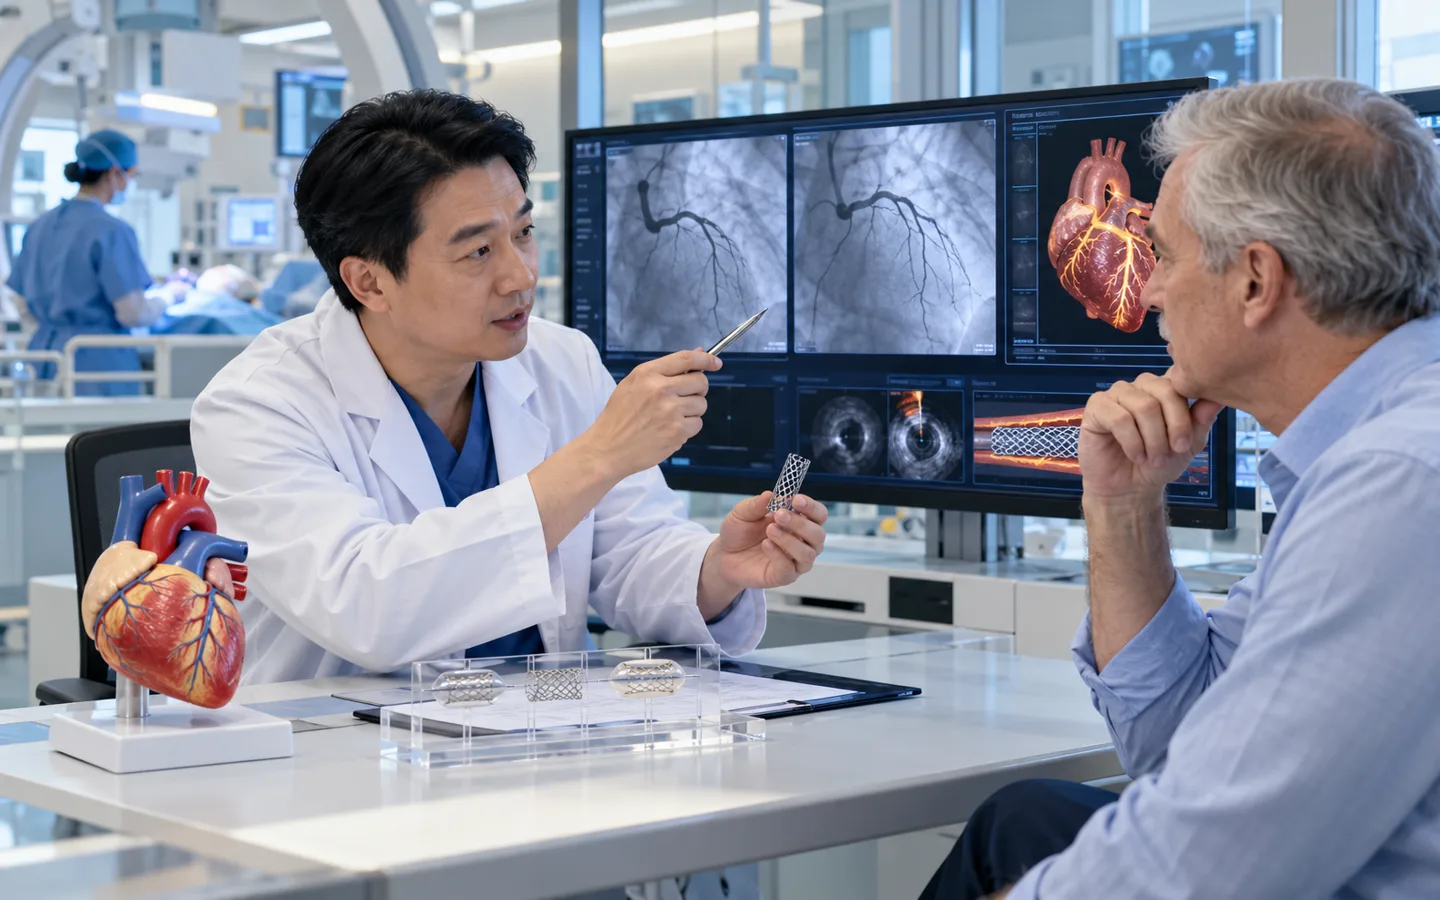
Angiography defines coronary anatomy; PCI treats selected narrowings
A thin catheter delivers contrast into the coronary arteries so X-ray imaging can show obstruction. Pressure measurements or intravascular imaging may clarify whether an intermediate lesion matters.
PCI opens a selected narrowing with a balloon and commonly a stent. It can be lifesaving during some heart attacks; in stable disease it is compared with medical therapy and bypass surgery according to symptoms and anatomy.
Before elective angiography, clarify whether PCI would be appropriate and how complex findings would be reviewed with a heart team.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about coronary angiography and PCI.
- Acute coronary syndrome requiring urgent invasive assessment.
- Persistent angina despite appropriate medical treatment.
- High-risk non-invasive testing or uncertain coronary anatomy.
- Known coronary disease where physiology or imaging may change treatment.
What the specialist team must confirm
The team reviews symptoms, ECG and troponin when acute, stress or CT testing, kidney function, bleeding and allergy history, previous stents or bypass grafts, medicines and whether anatomy could favor CABG.
Key points for this treatment

From clinical question to anatomy-guided treatment
The plan distinguishes emergency reperfusion from elective symptom-focused or prognostic treatment.
Stent success depends on medication and prevention
Access-site bleeding, chest symptoms, rhythm and kidney function are checked early. Antiplatelet treatment must be understood before discharge.
Long-term care addresses cholesterol, blood pressure, diabetes, smoking, exercise and recurrent symptoms. A stent treats one segment but not the whole atherosclerotic process.

Risks, limits and realistic expectations
Risks include bleeding, artery injury, contrast allergy or kidney injury, rhythm problems, heart attack, stroke, emergency surgery, restenosis, stent thrombosis and death. PCI may not improve survival in every stable coronary pattern.
Ongoing chest pressure, sweating, severe breathlessness, collapse or new neurologic symptoms require emergency local care.