
GI bleeding is a symptom with many possible sources and levels of urgency
Bleeding may arise from the esophagus, stomach, small bowel, colon or rectum. It can be obvious and sudden or slow enough to appear only as anemia.
Resuscitation, medicine review and estimated bleeding rate guide the sequence. Endoscopy can diagnose and treat many sources, while CT angiography, interventional radiology or surgery may be needed for ongoing severe bleeding.
Vomiting blood, black stool with weakness, large-volume red bleeding, fainting or shock requires immediate local hospital assessment rather than planned travel.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about gastrointestinal bleeding evaluation and treatment.
- Overt upper or lower GI bleeding after stabilization.
- Unexplained iron-deficiency anemia.
- Recurrent bleeding after initial endoscopy.
- Suspected small-bowel bleeding after adequate gastroscopy and colonoscopy.
What the specialist team must confirm
The team reviews vital signs, hemoglobin and trends, transfusions, stool or vomit appearance, anticoagulants and NSAIDs, liver disease, prior ulcers or surgery, endoscopy quality, CT angiography and whether bleeding is ongoing enough for urgent localization.
Key points for this treatment
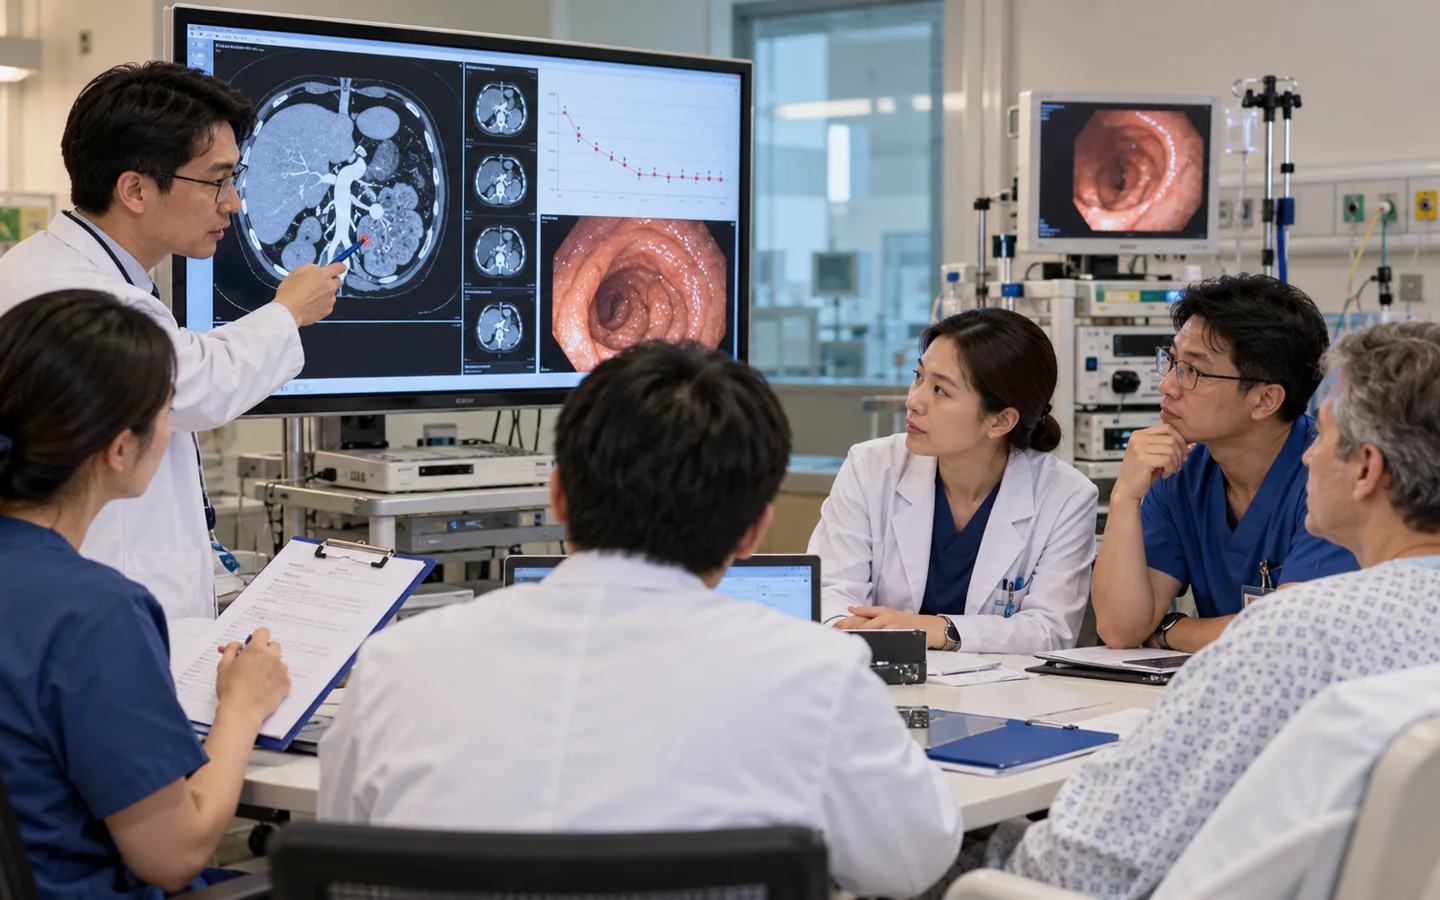
From resuscitation to source control
The team prioritizes safe stabilization, then selects the test most likely to find and treat the active source.
Hemoglobin recovery does not prove the source is solved
After treatment, recurrent stool change, symptoms and blood counts are monitored. Iron replacement may be needed after the bleeding source is controlled.
A negative study may reflect intermittent bleeding or inadequate visualization. The next step depends on recurrence, anemia severity and the quality of prior investigations.

Risks, limits and realistic expectations
Bleeding can recur despite apparently successful treatment. Endoscopy and radiologic procedures can cause bleeding, perforation, contrast or sedation complications, and surgery may be required in unstable cases.
Vomiting blood, black or large-volume red stool, fainting, confusion, chest pain, shortness of breath or signs of shock requires emergency services immediately.