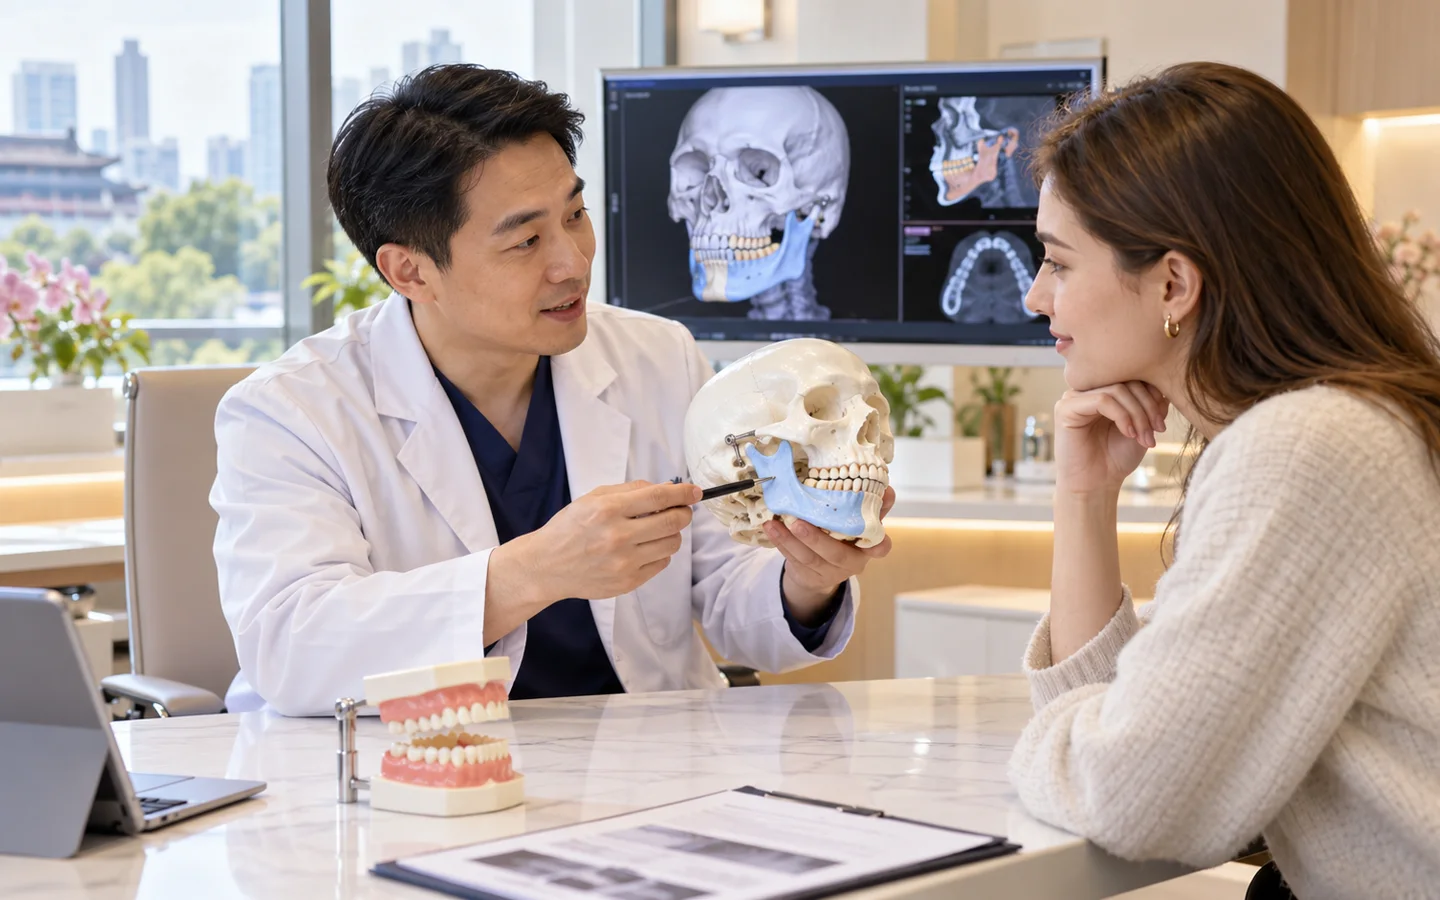
Maxillofacial Reconstruction: diagnosis, function and long-term planning
Maxillofacial Reconstruction is considered when tumor, trauma, infection or congenital difference leaves a jaw or facial defect requiring structural and functional restoration.
Reconstruction should anticipate the final bite, dental implants, speech, swallowing, airway and facial contour before selecting plates, grafts or vascularized tissue.
Who may be considered?
Specialist review may help when a complex defect crosses bone, soft tissue and dental function and needs coordinated specialist planning.
- Jaw defect after cancer removal.
- Complex facial trauma with bone or soft-tissue loss.
- Osteonecrosis or infection requiring resection.
- Congenital or acquired deformity needing staged reconstruction.
What the specialist team must confirm
Review high-resolution CT and vascular imaging when needed, pathology, defect dimensions, bite and remaining teeth, donor sites, nutrition, airway, speech and swallow, prior radiation and infection history.
Key points for this treatment

From defect mapping to staged facial and dental rehabilitation
The team should define which goals are immediate and which require later contouring, implants or prosthetic work.
Reconstruction matures through healing and rehabilitation
Early monitoring focuses on airway, flap blood flow, infection, wound closure, nutrition and donor-site function.
Bone union, plate condition, speech, swallowing, jaw movement, appearance and readiness for dental restoration are reviewed in stages.

Risks, limits and realistic expectations
Risks include flap loss, bleeding, infection, fistula, nonunion, plate exposure, donor-site weakness, nerve change, malocclusion, swallowing difficulty and repeated surgery.
Flap color or temperature change, neck swelling, heavy bleeding, fever, wound breakdown or breathing difficulty requires immediate specialist assessment.