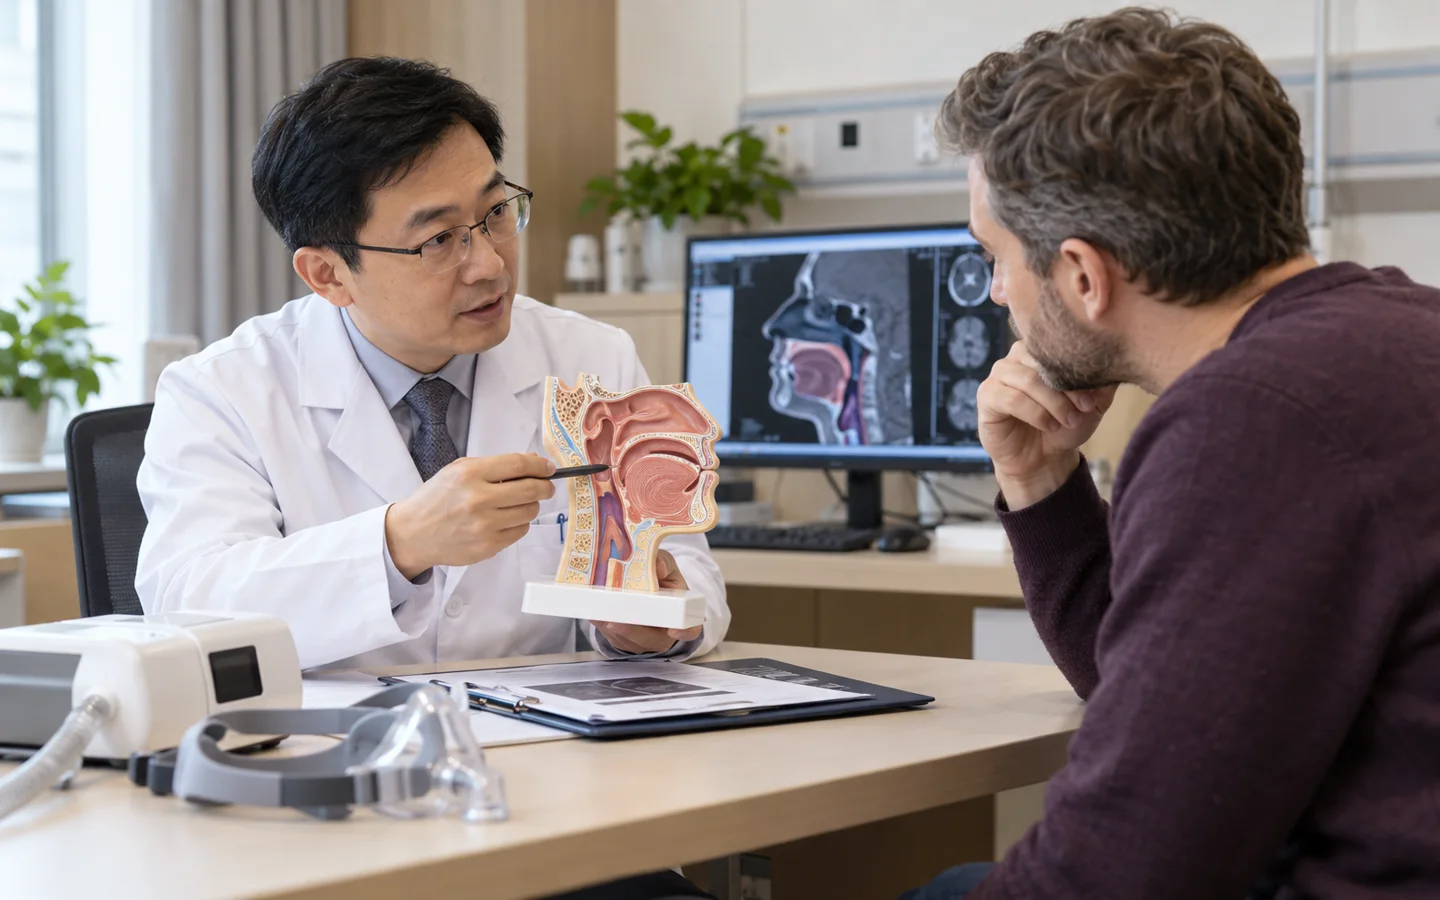
Sleep Apnea Surgery: diagnosis, function and long-term planning
Sleep Apnea Surgery is considered when obstructive sleep apnea remains clinically important despite appropriate nonsurgical treatment or a correctable anatomic obstruction is identified.
No single operation treats every airway; tonsils, palate, tongue base, jaw position, nasal resistance, weight and sleep-state collapse may require different or combined strategies.
Who may be considered?
Specialist review may help when sleep apnea is objectively confirmed and PAP or other therapy is ineffective, intolerable or insufficient for a defined anatomic reason.
- Large tonsils or a focal obstruction with documented apnea.
- PAP-intolerant patients after optimization and alternative review.
- Craniofacial restriction suitable for skeletal advancement.
- Selected patients for tongue-base or stimulation procedures.
What the specialist team must confirm
Review full polysomnography, oxygen burden, PAP settings and adherence, weight and comorbidities, awake airway examination, tonsils, nasal obstruction, jaw anatomy and sleep endoscopy when it will change procedure selection.
Key points for this treatment
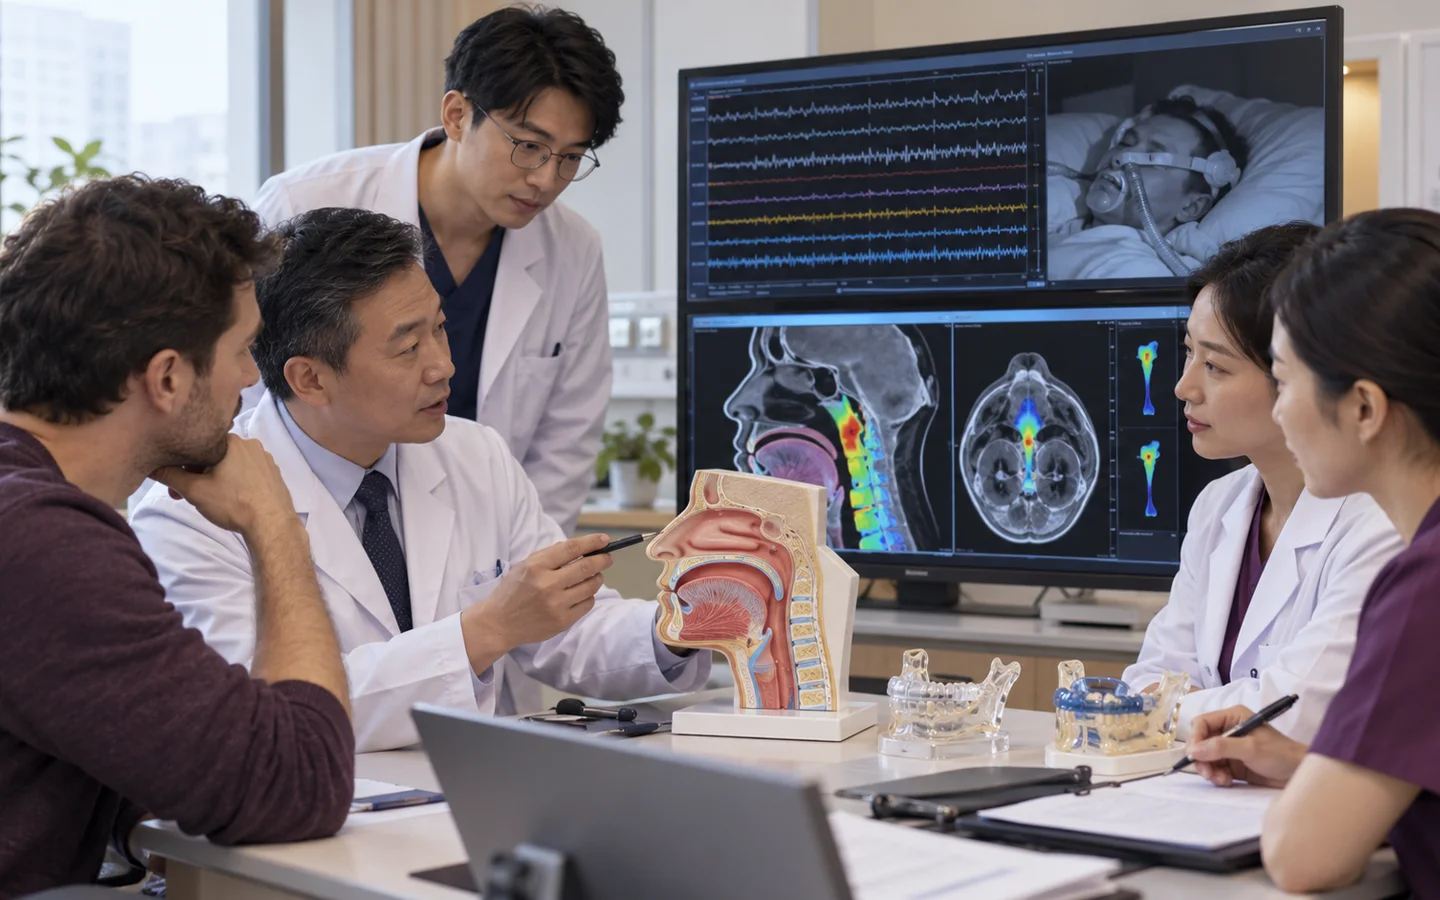
From physiologic severity to targeted airway treatment
The plan should state whether surgery aims to cure apnea, reduce severity or make PAP easier to use.
Symptoms alone cannot confirm surgical success
Swelling, throat pain, diet changes and temporary breathing risk depend on the procedure, so local postoperative monitoring must be arranged.
Repeat sleep testing determines residual apnea and whether PAP, oral appliance, weight management or additional treatment remains necessary.

Risks, limits and realistic expectations
Risks vary by operation and include pain, bleeding, infection, swallowing or speech change, airway swelling, dental or nerve effects, incomplete control and need for continued PAP.
Breathing difficulty, repeated oxygen drops, heavy throat bleeding, inability to drink, dehydration, chest symptoms or marked drowsiness needs emergency care.