
Voice Surgery: diagnosis, function and long-term planning
Voice Surgery is considered when a defined vocal-fold lesion, paralysis, scar or glottic gap causes persistent functional voice impairment.
Voice surgery should be diagnosis-specific; lesion removal, injection, framework surgery and reinnervation address different problems and can worsen voice if used without functional assessment.
Who may be considered?
Specialist review may help when hoarseness or vocal fatigue persists and laryngeal imaging identifies a potentially treatable structural or motion problem.
- A benign vocal-fold lesion not responding to conservative care.
- Vocal-fold paralysis or weakness causing a symptomatic gap.
- Selected scar or airway lesions requiring microsurgery.
- A patient prepared for perioperative voice therapy and vocal restrictions.
What the specialist team must confirm
Review flexible and stroboscopic laryngoscopy, acoustic and perceptual voice analysis, swallowing and airway symptoms, reflux and smoking factors, neurologic history, occupational voice demands and previous voice therapy.
Key points for this treatment
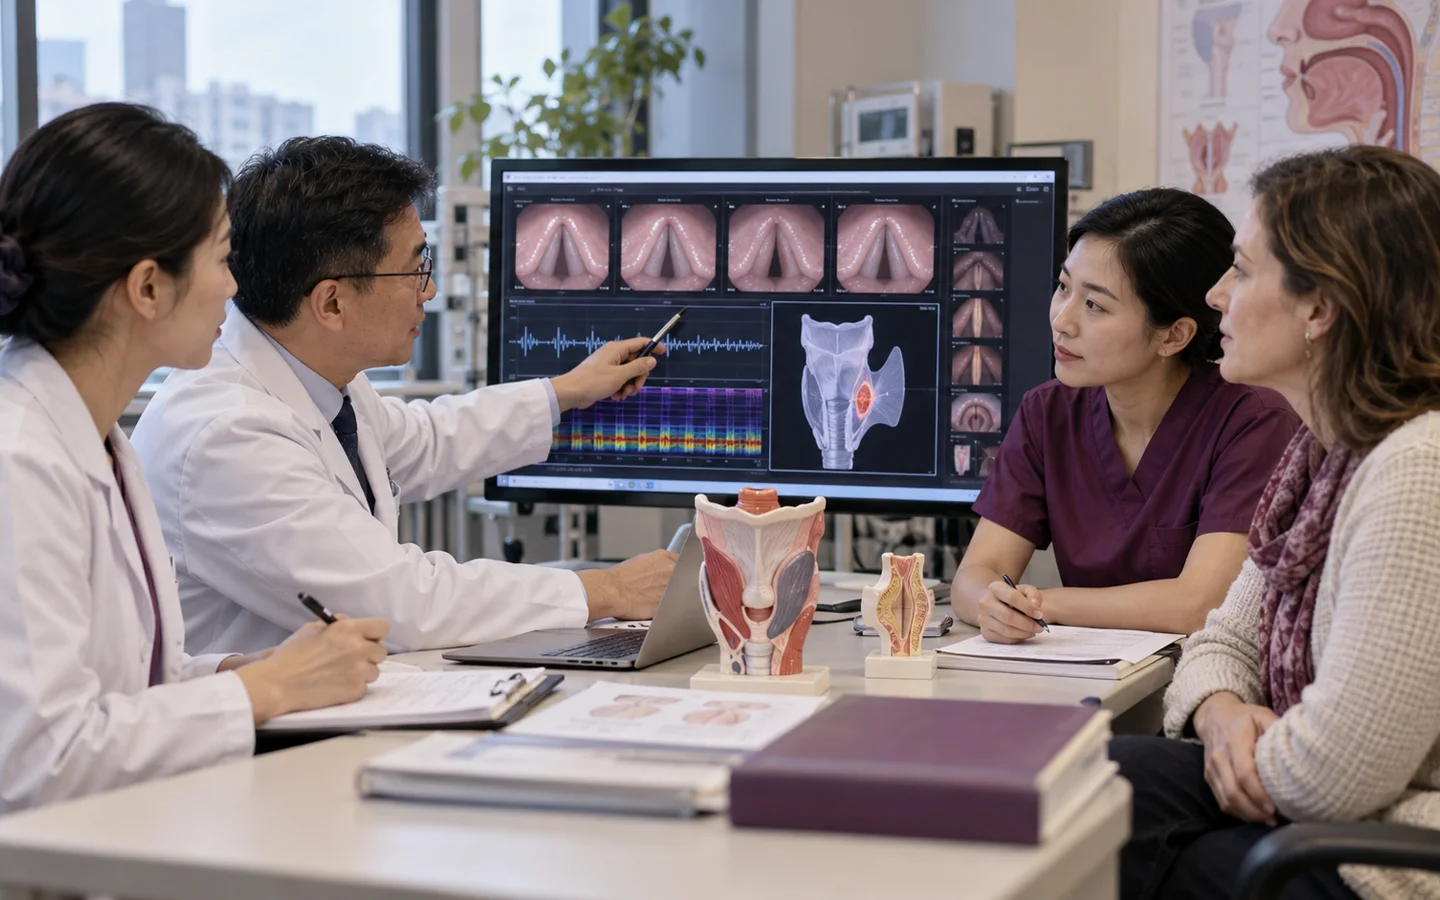
From voice diagnosis to coordinated surgery and therapy
Timing, vocal rest and therapy milestones should reflect tissue healing and professional voice demands.
Voice recovery requires controlled use, not only rest
Temporary voice restriction and gradual return are tailored to the operation, with hydration and irritant control supporting healing.
Repeat stroboscopy and voice measures guide therapy, workload progression and decisions about injection durability or revision.
Risks, limits and realistic expectations
Risks include bleeding, infection, dental or tongue injury, airway swelling, vocal-fold scar, persistent hoarseness, pitch change, swallowing difficulty and need for revision.
Breathing difficulty, noisy breathing, inability to swallow saliva, neck swelling, fever or sudden complete voice loss requires urgent assessment.