
Replacement is considered when a diseased valve cannot be repaired reliably
A narrowed or leaking valve can overload the heart and eventually cause symptoms or irreversible damage. Replacement substitutes a mechanical or biological valve when repair is not appropriate.
Valve choice is a lifetime pathway decision. Mechanical valves are durable but usually require lifelong anticoagulation; tissue valves avoid that requirement in many patients but can deteriorate and need another intervention.
Discuss pregnancy plans, bleeding risk, medication access, imaging follow-up and how a future valve-in-valve or redo procedure might fit.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about surgical heart valve replacement.
- Severe symptomatic valve stenosis or regurgitation.
- Severe disease with progressive ventricular changes despite limited symptoms.
- A valve unsuitable for durable repair.
- Failure or degeneration of a previous surgical prosthesis.
What the specialist team must confirm
The valve team reviews echocardiography, CT when relevant, ventricular and pulmonary function, coronary disease, frailty, infection history, anticoagulation feasibility, patient preference and the alternatives of repair or transcatheter therapy.
Key points for this treatment
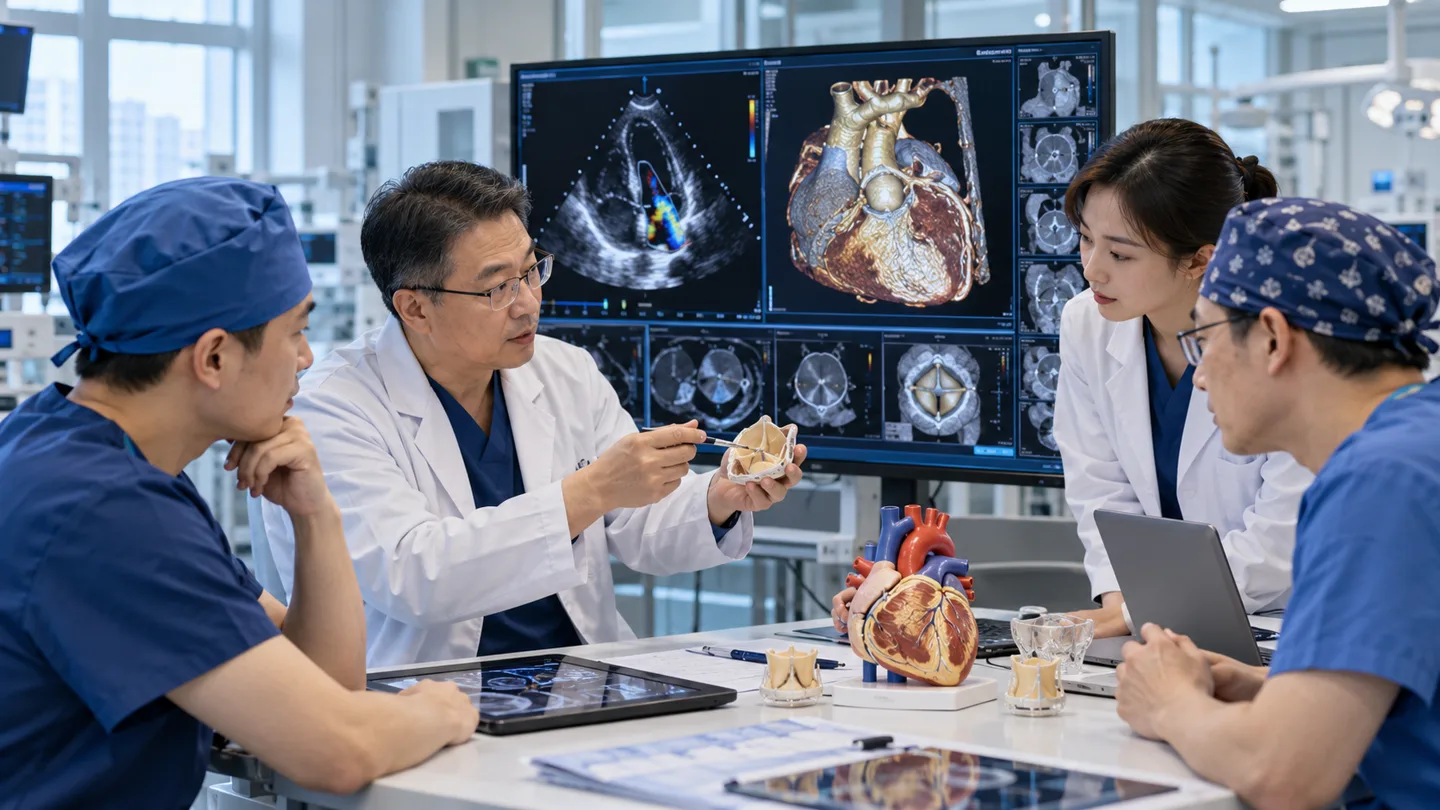
From timing decision to lifetime valve management
The procedure is one part of a plan that continues through anticoagulation, infection prevention and lifelong surveillance.
Protect the prosthesis and monitor heart recovery
Early follow-up checks valve function, rhythm, wound healing and anticoagulation where needed. A baseline postoperative echocardiogram supports later comparison.
Long-term care includes symptom review, scheduled imaging, dental health and rapid assessment of unexplained fever or embolic symptoms.

Risks, limits and realistic expectations
Risks include bleeding, infection, stroke, rhythm disturbance, prosthetic thrombosis, structural deterioration, patient–prosthesis mismatch, reoperation and death. No prosthesis reproduces a normal native valve perfectly.
New severe breathlessness, chest pain, fainting, stroke symptoms, uncontrolled bleeding or fever with chills requires urgent local care.