Home / Thoracic Surgery / Mediastinal Tumor Surgery
Thoracic surgery patient guide · 纵隔肿瘤手术

Mediastinal Tumor Surgery in China

Considering mediastinal tumor surgery in China? Start with tumour location, pathology and proposed surgical approach. This guide helps you identify the relevant records, questions for the receiving team and the scope of an individual estimate before a visit is agreed.

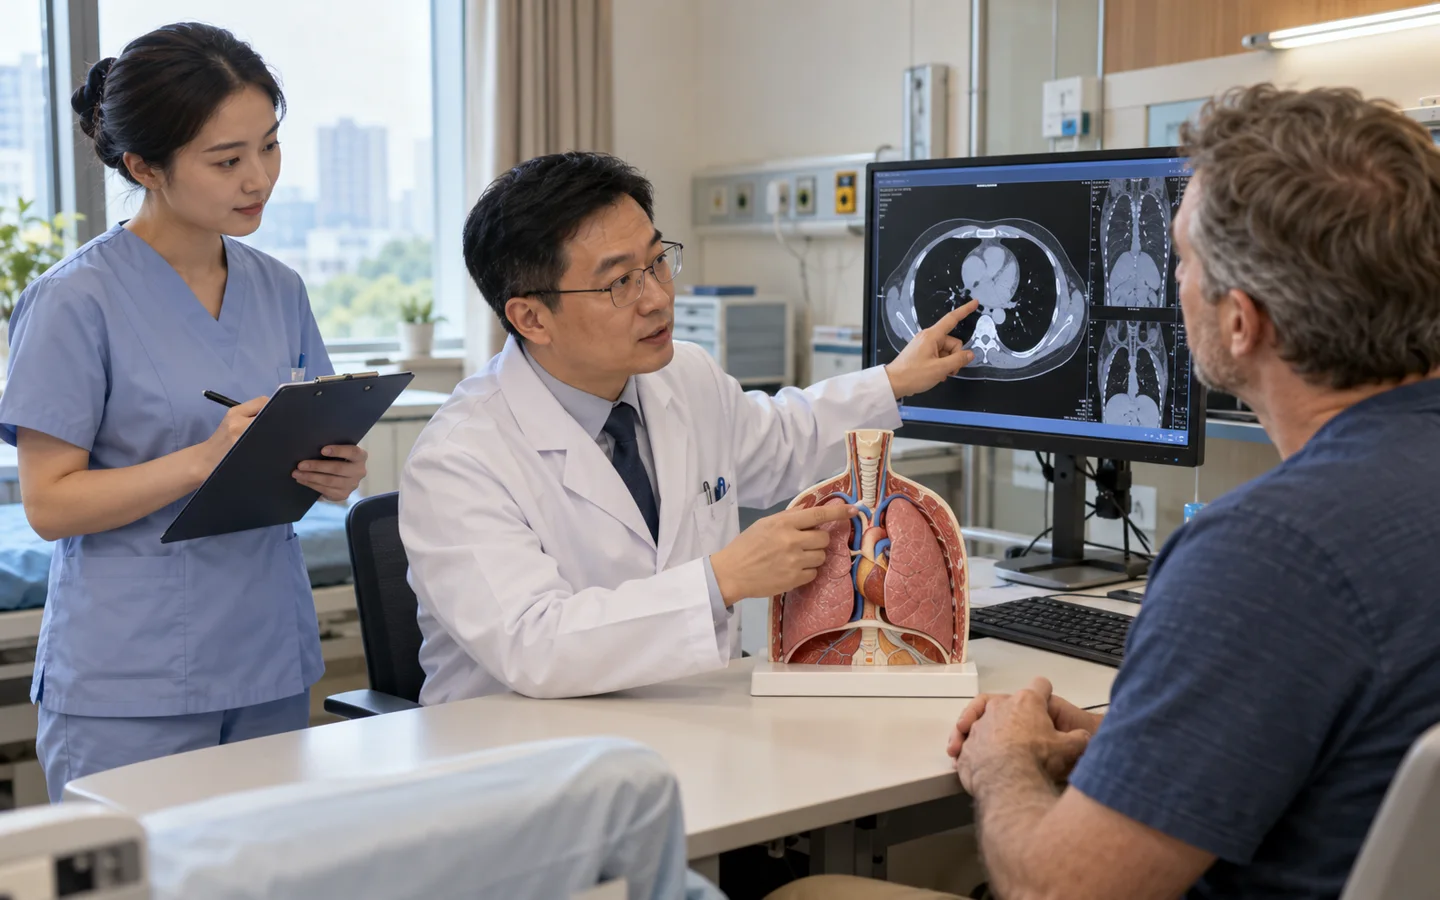
Chinese thoracic surgeon explaining the mediastinum and tumor location to an international patient

Medical cost reference

Indicative · not a quotation

Mediastinal Tumor Surgery costs in China

US$8,000–21,500

Original USD reference

Other currencies are approximate equivalents, not a quote or payment rate. Reference FX: ECB · 2 October 2026. Local snapshot, not live.

Mediastinal tumour resection; location, size and surgical approach affect the estimate.

This published reference range is a starting point for planning, not a fixed price or a China-wide average. Cities, public and private hospitals, procedure details and individual care needs affect costs. The hospital must confirm what is included and provide an estimate after reviewing your case.

  • Tumour location, size and extent
  • Surgical approach and additional procedures
  • Admission and subsequent treatment

Hospital medical fees, travel and our coordination services are separate. Any paid specialist review or coordination service is explained and agreed before you proceed.

Your next step

Start with your question

Tell us your diagnosis and what you need. Our free initial review checks the information and helps identify a suitable next step; it is not a specialist opinion or a hospital quotation.

Request a case-based estimate

Not ready to send records? Ask us first. Where hospital review is appropriate, we can help request an estimate. No travel commitment or mandatory proxy consultation.

Planning mediastinal tumor surgery in ChinaHospital review · individual costs · visit and follow-up

Plan the visit around tumour location, pathology and proposed surgical approach. Agree the assessment route before travel.

Records for the mediastinal tumor surgery review

Tell us what you already have: Contrast chest CT and MRI in DICOM; PET CT when performed; Pathology report slides and blocks. Start with a short summary; after first contact we explain which records the receiving team needs and how to share them.

Confirm the proposed scope and costs

Review the published reference below with the receiving team. Confirm the particular procedure, hospital and items included in your own estimate; the reference is not a confirmed quotation.

Visits and care after returning home

Ask which specialists need to review the imaging and how the proposed operation relates to any further treatment. Tell us if you need interpretation or English-language documents, and confirm the relevant arrangements with the receiving team.

Mediastinal surgery is defined by what surrounds the mass

The mediastinum contains the thymus, heart, great vessels, trachea, esophagus, nerves and lymphatic tissue. Masses in its anterior, middle and posterior compartments have different likely diagnoses.

Some tumors should be biopsied before treatment; others that appear clearly resectable may proceed directly to surgery. An unsafe biopsy path can cause bleeding or complicate definitive resection.

Do not treat every mediastinal mass the same way

Tumor type and compartment determine whether blood tests, PET, MRI, needle biopsy, surgical biopsy or direct resection is appropriate.

Who may be considered?

Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about mediastinal tumor surgery.

  • A resectable thymic epithelial or germ-cell tumor after appropriate work-up.
  • A symptomatic cyst or neurogenic tumor.
  • A mediastinal mass requiring surgical tissue diagnosis.
  • Residual localized disease considered for surgery within a multimodality plan.

What the specialist team must confirm

The team reviews contrast CT, MRI or PET, tumor markers, neurologic or myasthenic symptoms, tissue diagnosis when indicated and the mass relationship to vessels, pericardium, lung, airway, spine, esophagus and phrenic or recurrent-laryngeal nerves.

Key points for this treatment
Locationcentral chest mediastinum
Diagnosisimaging biomarkers and pathology
Riskmajor vessels airway and nerves
Accessthoracoscopy robotic sternotomy or open
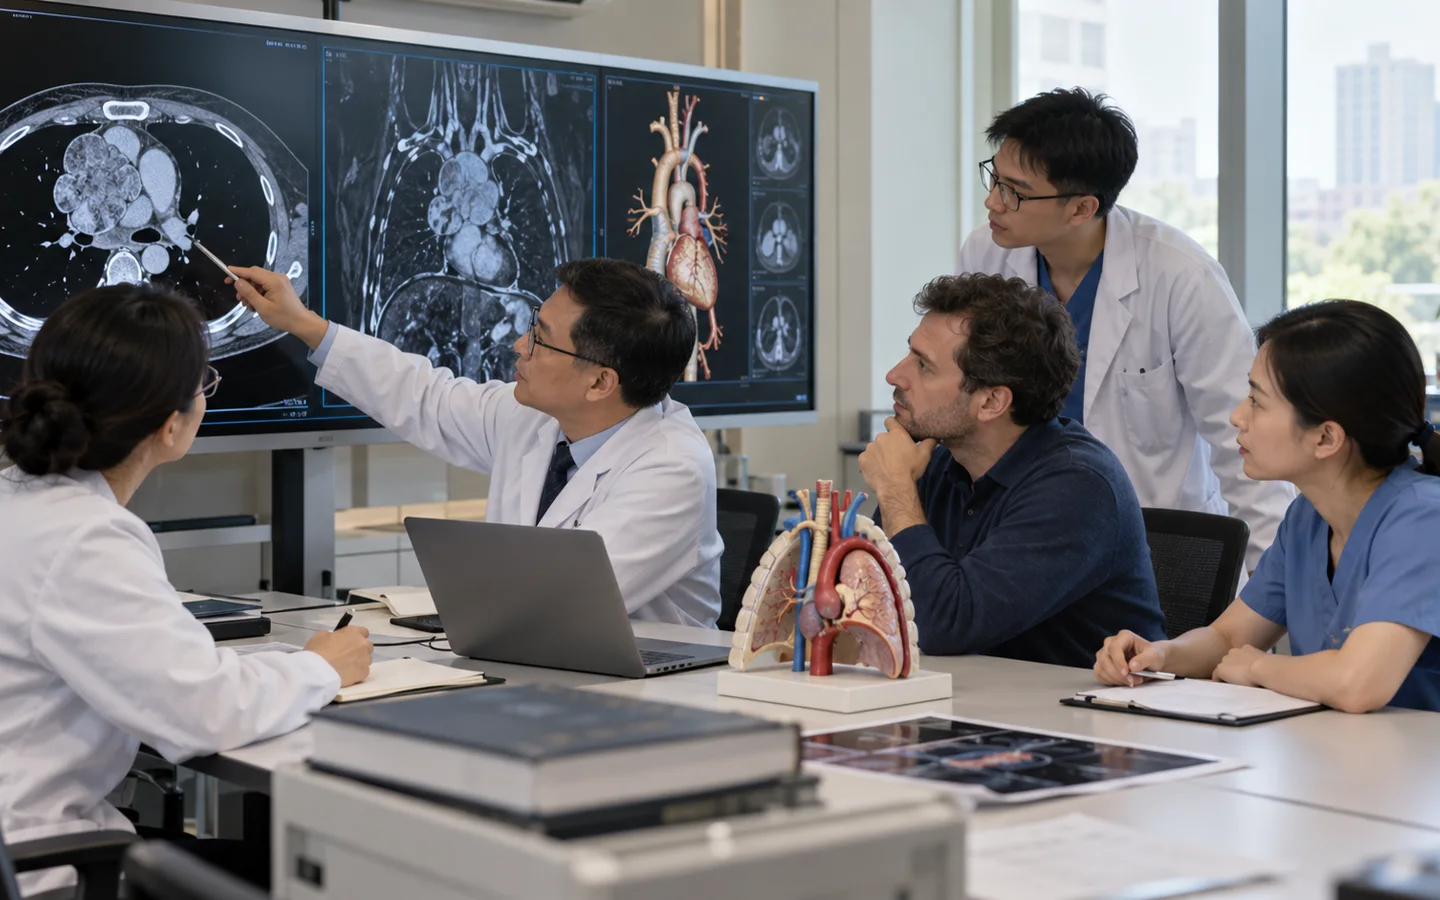
Chinese multidisciplinary team reviewing contrast CT MRI and major vessel relationships of a mediastinal mass
Compartment and invasion determine accessThe team plans vascular control, nerve preservation and whether cardiac, vascular, spine or reconstructive specialists are required.

From compartment diagnosis to safe resection

Surgery is planned only after the team understands whether complete removal is realistic and how pathology changes the wider treatment sequence.

ClassifyIdentify compartment and likely diagnosis
StageDefine invasion and systemic disease
PlanChoose biopsy or resection sequence
ProtectPrepare vessels airway and nerve strategy

Pathology directs the next phase

Early review focuses on breathing, bleeding, drains, voice, diaphragm movement and neurologic function. Recovery varies with incision and structures removed.

Final pathology, margins and stage determine whether surveillance, radiation, chemotherapy or another specialty review is needed.
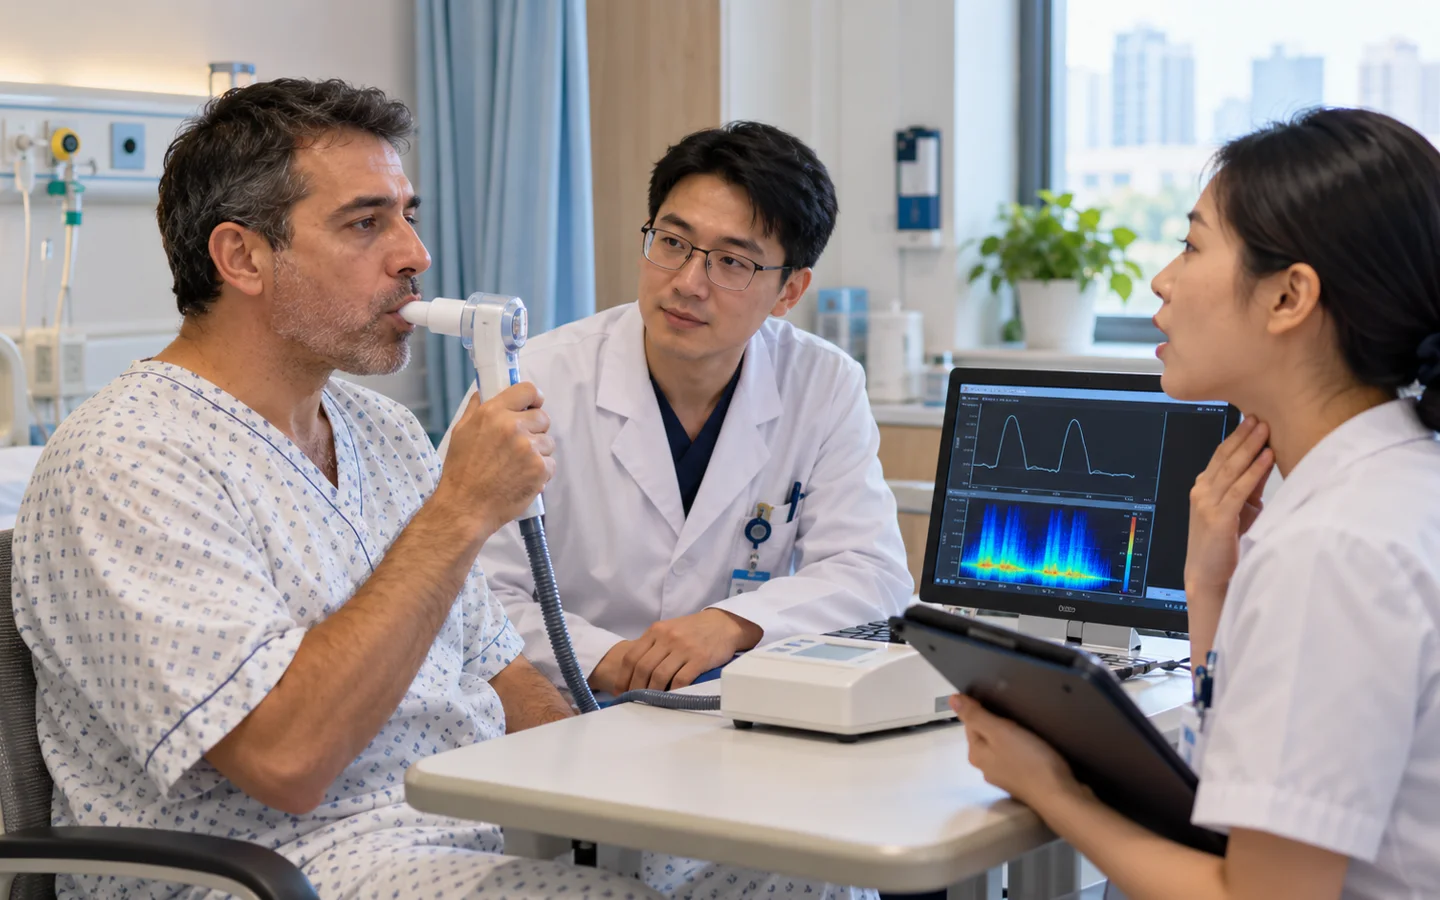
International patient completing breathing and voice assessment after mediastinal tumor surgery
Nerve and respiratory function need deliberate reviewVoice change, elevated diaphragm, arm symptoms or swallowing difficulty may indicate involvement of nearby structures.
Complete resectionPlan pathology-led surveillance
Unexpected invasionCoordinate additional treatment
Nerve effectAssess voice diaphragm or limb
Residual diseaseReturn to multidisciplinary review

Risks, limits and realistic expectations

Risks include bleeding from major vessels, lung or airway injury, nerve damage, diaphragm weakness, voice change, chyle leak, infection, incomplete resection, conversion to open surgery, recurrence and death.

Do not delay urgent local care

Rapid breathing difficulty, facial or neck swelling, fainting, new severe voice or swallowing change or neurologic weakness requires urgent local care.

Before hospital review

Records for mediastinal tumor surgery assessment

A safe international review depends on dated source reports, original imaging and a complete treatment timeline—not a diagnosis label alone.

Contrast chest CT and MRI in DICOM
PET CT when performed
Pathology report slides and blocks
Tumor-marker laboratory results
Neurologic and myasthenia assessments
Pulmonary and cardiac testing
Previous chemotherapy or radiotherapy details
Current symptoms medicines and functional status

Tell us what you need

Ask about your care,
your hospital and your budget.

You can ask about suitability, an expert opinion, an appointment or the likely medical cost. If you are unsure, choose “Not sure — please advise”.

This enquiry is aboutMediastinal Tumor SurgeryNot sure — please advise

How a personal estimate is prepared

  1. Tell us about your case.Describe your diagnosis, main question and preferred city, if any.
  2. Share the relevant records.We explain what is needed and how to send it by WhatsApp or email.
  3. Request a hospital estimate.Where appropriate, we help request hospital review and a cost estimate. Any paid review is agreed first.

This is an enquiry, not an order or payment. Proxy consultation is not mandatory. Any service scope is agreed separately before you proceed.

Ask about Mediastinal Tumor Surgery

A first enquiry is free. Email and permission to respond are required; the other details are optional. Any paid clinical review or coordination is discussed separately.

Included automatically so we know which procedure you are asking about.
A preference, not a confirmed appointment.
Please do not send passport numbers, card details or full medical files in this first enquiry. We will explain which records are needed next.

Send a short summary first. This is an enquiry, not an order, payment or confirmed appointment.

No booking or payment is made by sending this enquiry.
Editorial transparency

Medical sources

Patient information is based on established government and professional guidance. Content updated 5 October 2026. This is patient information, not an individual clinical assessment.