Home / Thoracic Surgery / Minimally Invasive Esophagectomy
Thoracic surgery patient guide · 微创食管切除术

Minimally Invasive Esophagectomy in China

Considering minimally invasive esophagectomy in China? Start with staging, approach selection and postoperative support. This guide helps you identify the relevant records, questions for the receiving team and the scope of an individual estimate before a visit is agreed.

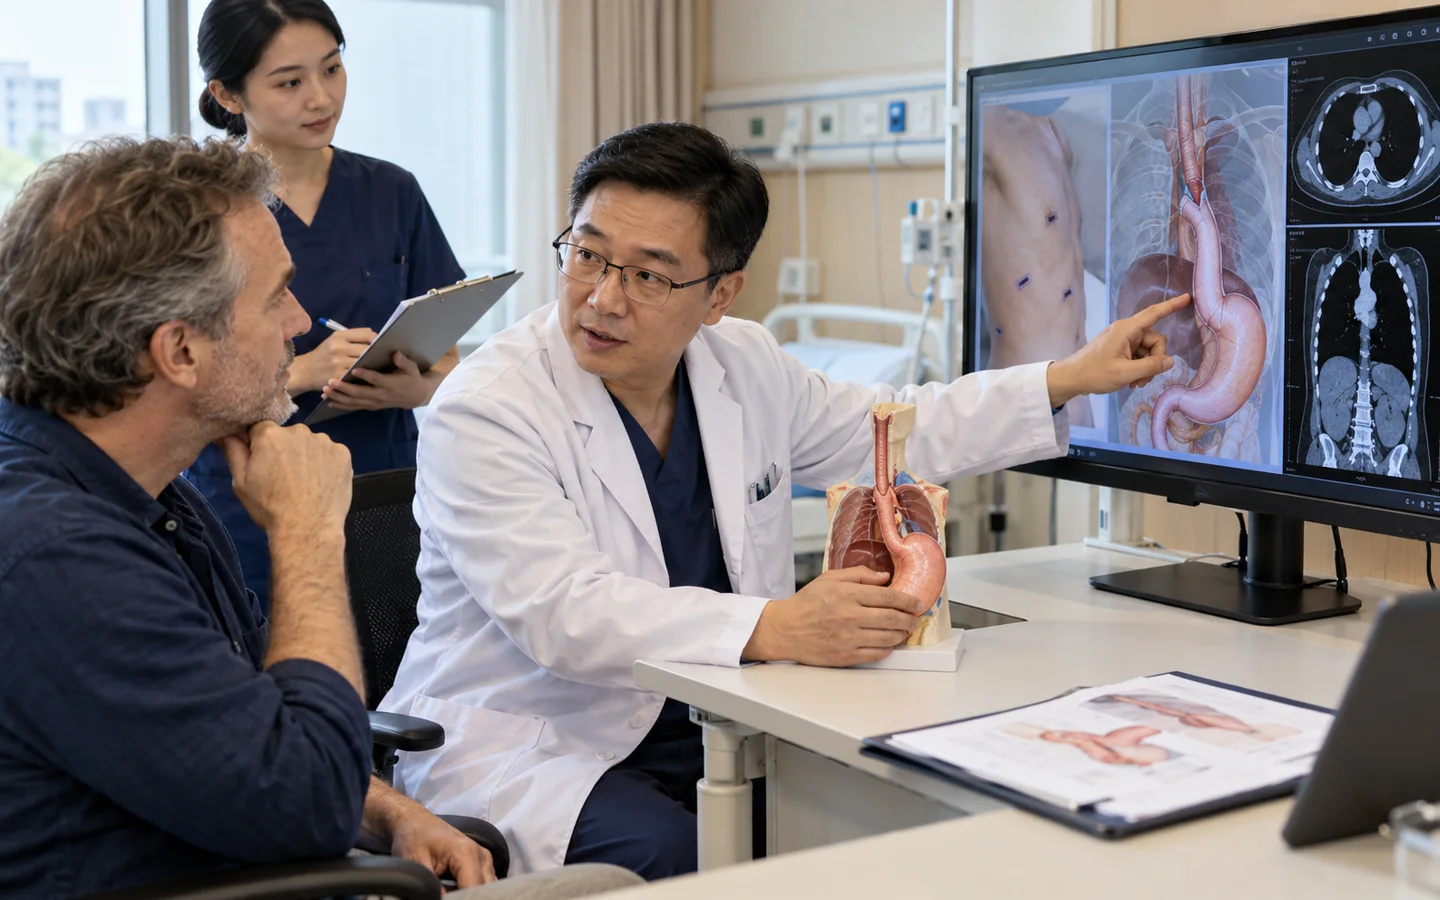
Chinese esophageal surgeon explaining minimally invasive esophagectomy ports and reconstruction to an international patient

Medical records & cost enquiry

Minimally Invasive Esophagectomy: assessment and cost questions

For Minimally Invasive Esophagectomy, the budget depends on the proposed care and the hospital. A useful estimate needs to distinguish:

  • Resection and reconstruction required
  • The proposed minimally invasive approach
  • Admission, nutrition and further treatment

Hospital medical fees, travel and our coordination services are separate. Any paid specialist review or coordination service is explained and agreed before you proceed.

Your next step

Start with your question

Tell us your diagnosis and what you need. Our free initial review checks the information and helps identify a suitable next step; it is not a specialist opinion or a hospital quotation.

Request a case-based estimate

Not ready to send records? Ask us first. Where hospital review is appropriate, we can help request an estimate. No travel commitment or mandatory proxy consultation.

Planning minimally invasive esophagectomy in ChinaHospital review · individual costs · visit and follow-up

Plan the visit around staging, approach selection and postoperative support. Agree the assessment route before travel.

Records for the minimally invasive esophagectomy review

Tell us what you already have: Endoscopy biopsy and pathology; CT PET and endoscopic ultrasound; Chemotherapy and radiotherapy summaries. Start with a short summary; after first contact we explain which records the receiving team needs and how to share them.

Confirm the proposed scope and costs

Before asking for a personal estimate, clarify: Resection and reconstruction required; The proposed minimally invasive approach; Admission, nutrition and further treatment. The receiving team confirms the proposed scope and hospital charges; coordination is agreed separately.

Visits and care after returning home

Ask whether this approach fits the proposed operation and how nutrition, review visits and any further therapy would be coordinated. Tell us if you need interpretation or English-language documents, and confirm the relevant arrangements with the receiving team.

Minimally invasive access changes the incisions, not the scale of treatment

The chest and abdominal phases are performed through small ports, sometimes with a limited neck or chest incision for the anastomosis and specimen.

The procedure remains a major operation. Tumor extent, prior radiation, adhesions, airway or vessel involvement and the team’s ability to perform a safe conduit and lymphadenectomy determine suitability.

Ask about the complete operation, not only the ports

Compare anastomosis location, lymph-node plan, conversion threshold, leak management and centre experience with the exact hybrid, thoracoscopic or robotic technique.

Who may be considered?

Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about minimally invasive esophagectomy.

  • Resectable esophageal or junctional cancer within a planned multimodality pathway.
  • A patient with anatomy and cardiopulmonary reserve suitable for minimally invasive access.
  • Selected early disease not appropriate for endoscopic treatment.
  • A case without invasion that requires an open en-bloc approach.

What the specialist team must confirm

Review includes the same oncologic staging as open esophagectomy plus prior abdominal surgery, adhesions, body habitus, conduit blood supply, airway access, port feasibility and the centre’s outcomes for leak, pneumonia and conversion.

Key points for this treatment
Accessthoracoscopy laparoscopy or robotic
Objectivesame oncologic resection
Reconstructionstomach conduit and anastomosis
Priorityleak lung and nutrition prevention
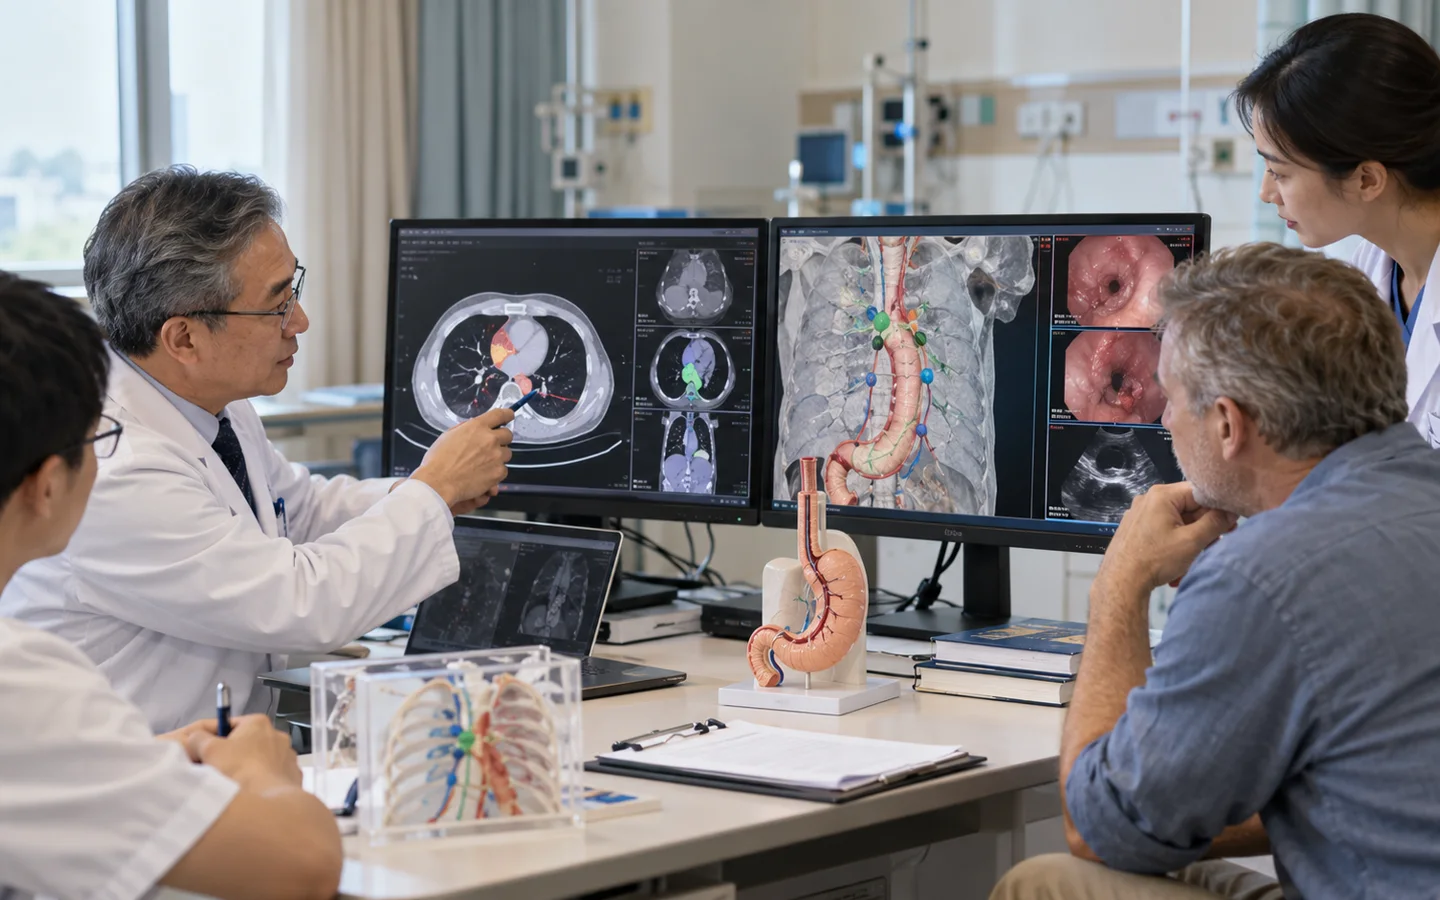
Chinese robotic and thoracoscopic team planning tumor stage lymph nodes and stomach conduit route
Minimal access still needs an open-surgery backupThe team preplans safe conversion, conduit perfusion assessment and treatment of an anastomotic or airway complication.

From minimally invasive access planning to full oncologic treatment

The approach is appropriate only when the expected resection and reconstruction are equivalent to the best open operation for that case.

StageConfirm tumor and treatment sequence
PrepareImprove nutrition lungs and fitness
ResectComplete chest and abdominal cancer phases
ReconnectConstruct conduit and verify perfusion

Enhanced recovery does not remove major-surgery risks

Early mobilization, lung physiotherapy and multimodal pain control may support recovery, while leak, pneumonia, rhythm and conduit perfusion are monitored closely.

Diet progresses in small steps. Long-term review covers swallowing, weight, reflux, dumping symptoms, final pathology and cancer surveillance.

International patient walking with respiratory physiotherapy and nutrition support after minimally invasive esophagectomy
Function and nutrition define recoveryShorter incisions may reduce access trauma, but the reconstructed digestive route still changes eating and weight.
Planned accessComplete resection through ports
ConversionOpen safely when exposure requires
Stable conduitAdvance nutrition by protocol
Final pathologyCoordinate additional treatment

Risks, limits and realistic expectations

Risks include anastomotic leak, conduit necrosis, pneumonia, bleeding, chyle leak, nerve injury, stricture, delayed emptying, conversion to open surgery, recurrence and death.

Do not delay urgent local care

Fever, new chest or abdominal pain, breathlessness, rapid heart rate, inability to swallow or persistent vomiting requires urgent local review.

Before hospital review

Records for minimally invasive esophagectomy assessment

A safe international review depends on dated source reports, original imaging and a complete treatment timeline—not a diagnosis label alone.

Endoscopy biopsy and pathology
CT PET and endoscopic ultrasound
Chemotherapy and radiotherapy summaries
Pulmonary and cardiac testing
Nutrition weight and swallowing records
Previous abdominal and chest operation notes
Current medicines allergies and frailty assessment
Proposed operative approach and backup plan

Tell us what you need

Ask about your care,
your hospital and your budget.

You can ask about suitability, an expert opinion, an appointment or the likely medical cost. If you are unsure, choose “Not sure — please advise”.

This enquiry is aboutMinimally Invasive EsophagectomyNot sure — please advise

How a personal estimate is prepared

  1. Tell us about your case.Describe your diagnosis, main question and preferred city, if any.
  2. Share the relevant records.We explain what is needed and how to send it by WhatsApp or email.
  3. Request a hospital estimate.Where appropriate, we help request hospital review and a cost estimate. Any paid review is agreed first.

This is an enquiry, not an order or payment. Proxy consultation is not mandatory. Any service scope is agreed separately before you proceed.

Ask about Minimally Invasive Esophagectomy

A first enquiry is free. Email and permission to respond are required; the other details are optional. Any paid clinical review or coordination is discussed separately.

Included automatically so we know which procedure you are asking about.
A preference, not a confirmed appointment.
Please do not send passport numbers, card details or full medical files in this first enquiry. We will explain which records are needed next.

Send a short summary first. This is an enquiry, not an order, payment or confirmed appointment.

No booking or payment is made by sending this enquiry.
Editorial transparency

Medical sources

Patient information is based on established government and professional guidance. Content updated 5 October 2026. This is patient information, not an individual clinical assessment.