Home / Gastroenterology / Peroral Endoscopic Myotomy (POEM)
Gastroenterology patient guide · 经口内镜下肌切开术

POEM for Achalasia in China

Considering POEM for achalasia in China? Start with swallowing investigations, prior treatment and procedure scope. This guide helps you identify the relevant records, questions for the receiving team and the scope of an individual estimate before a visit is agreed.

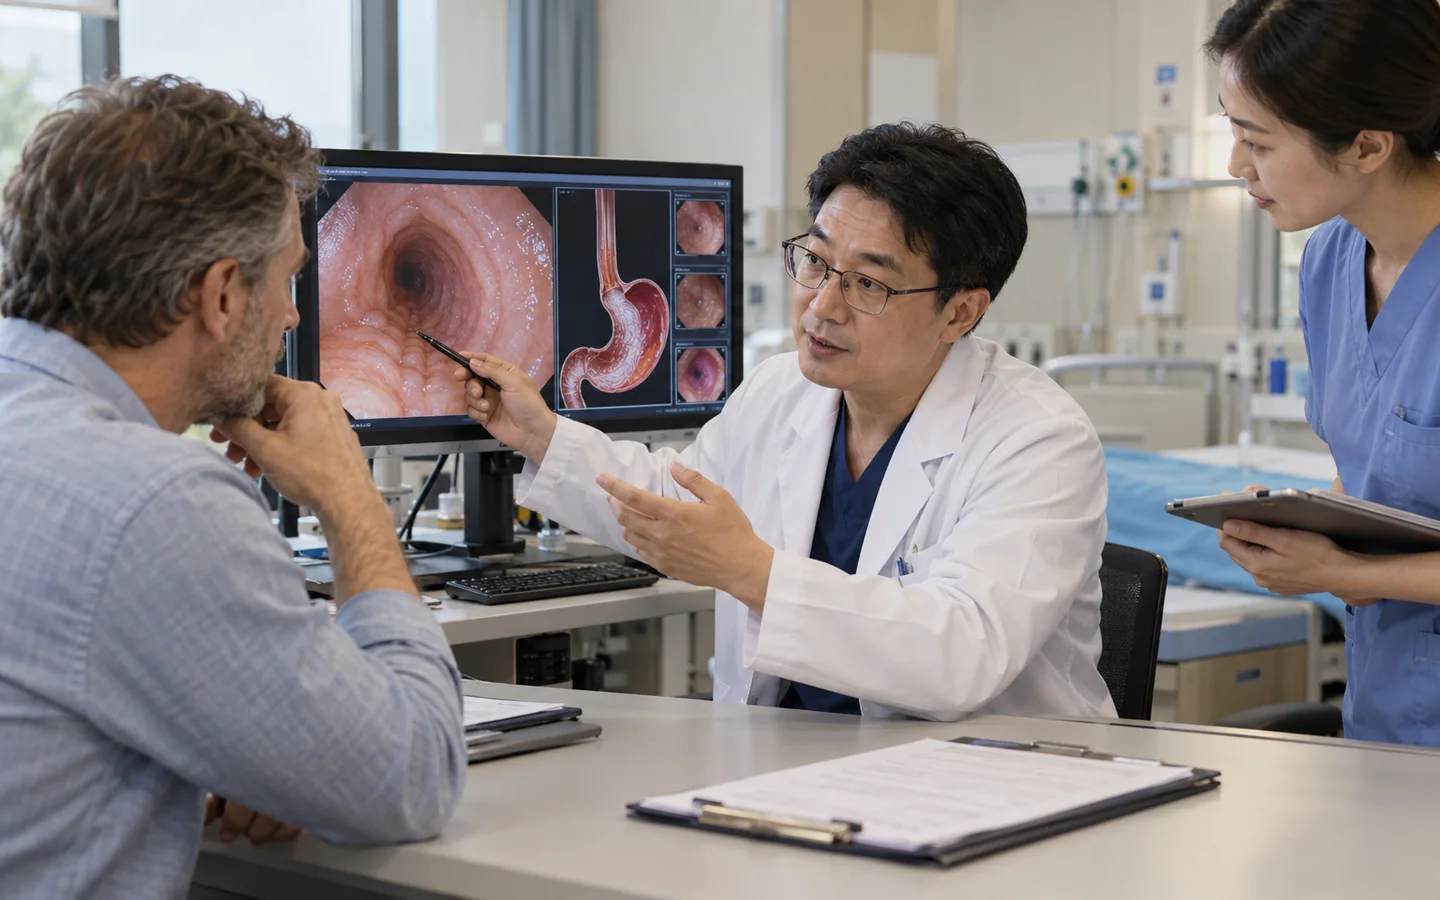
Chinese advanced endoscopist explaining POEM achalasia and reflux tradeoffs to an international patient

Medical records & cost enquiry

POEM for Achalasia: assessment and cost questions

For Peroral Endoscopic Myotomy (POEM), the budget depends on the proposed care and the hospital. A useful estimate needs to distinguish:

  • The motility disorder and proposed muscle division
  • Endoscopic assessment and admission scope
  • Reflux assessment and follow-up

Hospital medical fees, travel and our coordination services are separate. Any paid specialist review or coordination service is explained and agreed before you proceed.

Your next step

Start with your question

Tell us your diagnosis and what you need. Our free initial review checks the information and helps identify a suitable next step; it is not a specialist opinion or a hospital quotation.

Request a case-based estimate

Not ready to send records? Ask us first. Where hospital review is appropriate, we can help request an estimate. No travel commitment or mandatory proxy consultation.

Planning POEM for achalasia in ChinaHospital review · individual costs · visit and follow-up

Plan the visit around swallowing investigations, prior treatment and procedure scope. Agree the assessment route before travel.

Records for the POEM for achalasia review

Tell us what you already have: High-resolution manometry raw report; Timed barium swallow images and measurements; Upper endoscopy report and biopsies. Start with a short summary; after first contact we explain which records the receiving team needs and how to share them.

Confirm the proposed scope and costs

Before asking for a personal estimate, clarify: The motility disorder and proposed muscle division; Endoscopic assessment and admission scope; Reflux assessment and follow-up. The receiving team confirms the proposed scope and hospital charges; coordination is agreed separately.

Visits and care after returning home

Ask how the specialist reviews the swallowing diagnosis, what the proposed procedure includes and how symptoms and follow-up would be reviewed. Tell us if you need interpretation or English-language documents, and confirm the relevant arrangements with the receiving team.

POEM cuts selected esophageal muscle from inside the lumen

Under general anesthesia, the endoscopist enters the esophageal wall, creates a submucosal tunnel and cuts muscle across the lower sphincter, then closes the entry with clips.

Myotomy length can be tailored to achalasia subtype or spastic disease. POEM does not include an anti-reflux wrap, so reflux assessment and management are important.

Diagnosis must be complete before irreversible myotomy

High-resolution manometry, endoscopy and timed barium testing help distinguish achalasia from obstruction, pseudoachalasia or another motility disorder.

Who may be considered?

Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about POEM for achalasia.

  • Confirmed achalasia with significant swallowing symptoms.
  • Type III or spastic disease where a longer myotomy may help.
  • Persistent or recurrent symptoms after selected previous treatment.
  • A patient fit for general anesthesia and structured reflux follow-up.

What the specialist team must confirm

Review includes high-resolution manometry, timed barium swallow, endoscopy, weight and aspiration history, prior dilation Botox or surgery, reflux testing when relevant, CT or EUS if pseudoachalasia is a concern and anesthesia risk.

Key points for this treatment
Targetnonrelaxing lower esophageal sphincter
Methodsubmucosal tunnel and myotomy
Evidencemanometry endoscopy and timed barium
Long-term issuereflux monitoring
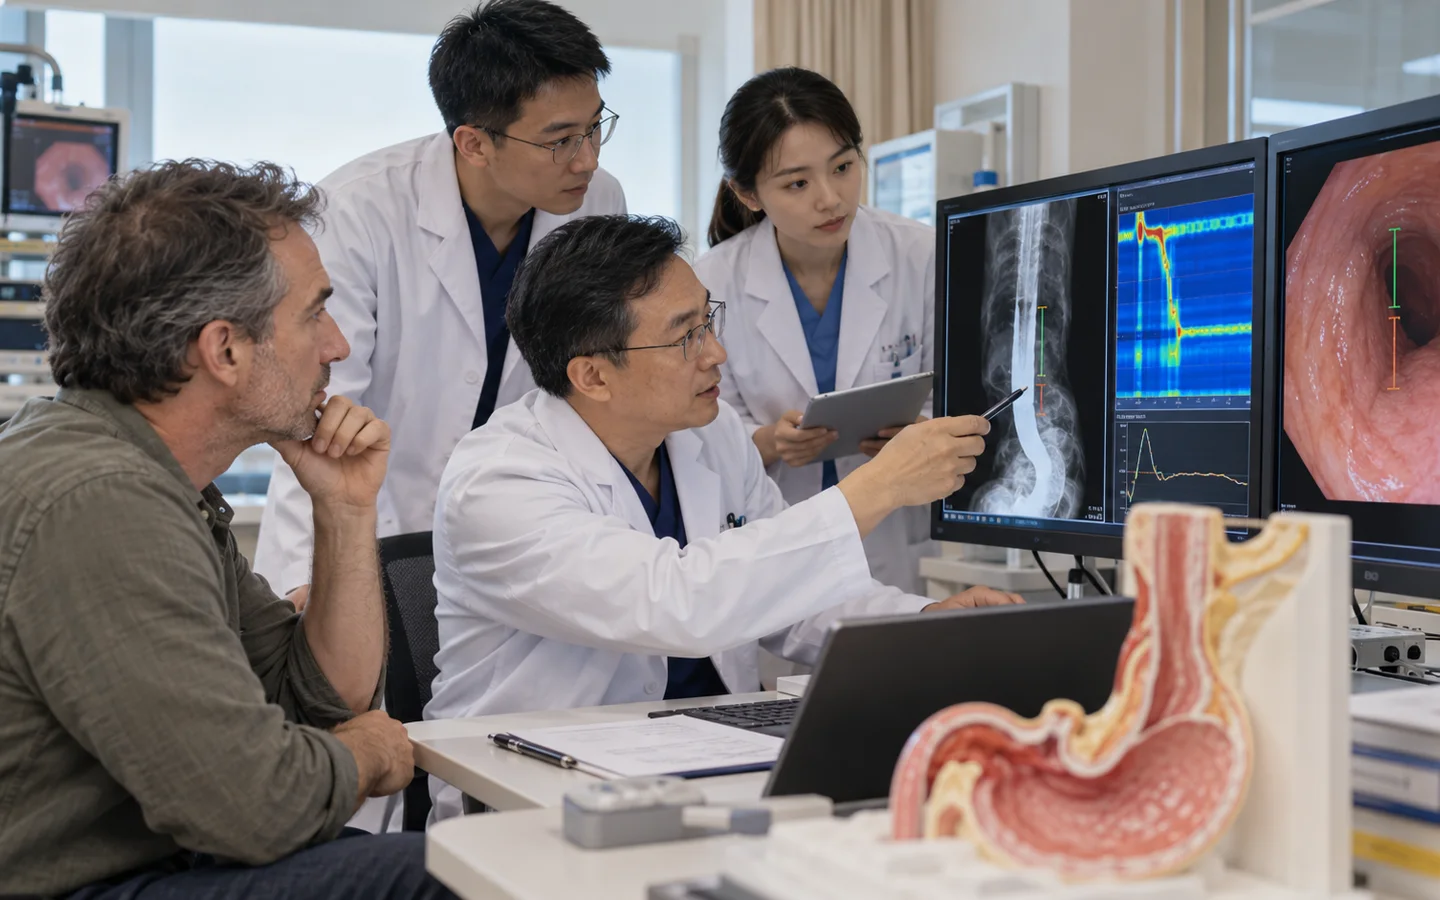
Chinese esophageal motility team reviewing manometry timed barium endoscopy and planned myotomy length
Achalasia subtype determines myotomy lengthPressure pattern, retained esophageal contents and previous scarring guide tunneling, muscle division and preparation.

From manometric diagnosis to tailored endoscopic myotomy

The team compares durable swallowing improvement, reflux risk, prior treatment and local expertise across POEM, dilation and surgery.

ConfirmClassify achalasia and exclude obstruction
PrepareClear esophagus and plan anesthesia
TunnelCreate submucosal route and myotomy
ProtectClose entry and monitor leak and reflux

Swallowing and reflux must both be measured

Diet advances from liquids according to protocol while pain, fever, leak and infection are monitored. Early imaging or endoscopy practices vary by centre.

Timed barium, symptom score, endoscopy or reflux testing may assess response. Good swallowing does not exclude silent acid exposure.
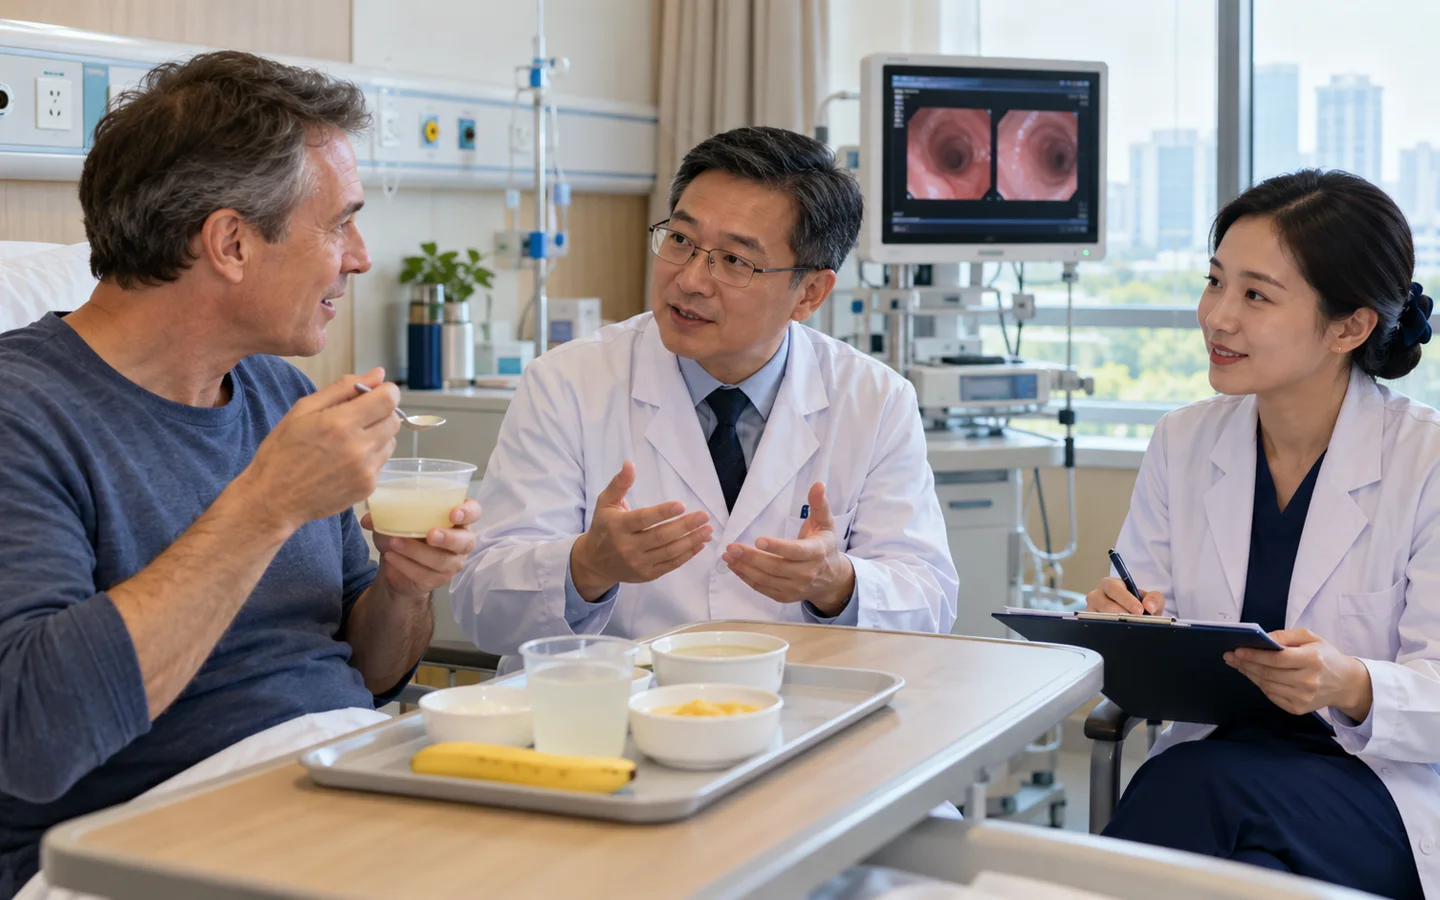
International patient reviewing liquid diet swallowing improvement and reflux medicine after POEM
Relief and reflux are separate outcomesA successful myotomy opens the sphincter; follow-up checks whether acid injury needs long-term treatment.
Swallowing improvesAdvance diet and monitor weight
Symptoms persistReassess emptying and myotomy
Reflux developsTreat and assess mucosal injury
Late recurrenceRepeat objective motility evaluation

Risks, limits and realistic expectations

Risks include bleeding, mucosal injury, perforation, leak, infection, pneumoperitoneum or mediastinal air, persistent dysphagia and gastroesophageal reflux. Additional treatment may be needed.

Do not delay urgent local care

Fever, severe chest or abdominal pain, breathlessness, vomiting blood, inability to swallow liquids or rapidly worsening neck swelling requires urgent local assessment.

Before hospital review

Records for POEM for achalasia assessment

A safe international review depends on dated source reports, original imaging and a complete treatment timeline—not a diagnosis label alone.

High-resolution manometry raw report
Timed barium swallow images and measurements
Upper endoscopy report and biopsies
CT EUS or other imaging when performed
Prior dilation Botox POEM or surgery records
Weight aspiration and symptom timeline
Reflux testing and acid-suppression history
Current medicines allergies and anesthesia assessment

Tell us what you need

Ask about your care,
your hospital and your budget.

You can ask about suitability, an expert opinion, an appointment or the likely medical cost. If you are unsure, choose “Not sure — please advise”.

This enquiry is aboutPeroral Endoscopic Myotomy (POEM)Not sure — please advise

How a personal estimate is prepared

  1. Tell us about your case.Describe your diagnosis, main question and preferred city, if any.
  2. Share the relevant records.We explain what is needed and how to send it by WhatsApp or email.
  3. Request a hospital estimate.Where appropriate, we help request hospital review and a cost estimate. Any paid review is agreed first.

This is an enquiry, not an order or payment. Proxy consultation is not mandatory. Any service scope is agreed separately before you proceed.

Ask about Peroral Endoscopic Myotomy (POEM)

A first enquiry is free. Email and permission to respond are required; the other details are optional. Any paid clinical review or coordination is discussed separately.

Included automatically so we know which procedure you are asking about.
A preference, not a confirmed appointment.
Please do not send passport numbers, card details or full medical files in this first enquiry. We will explain which records are needed next.

Send a short summary first. This is an enquiry, not an order, payment or confirmed appointment.

No booking or payment is made by sending this enquiry.
Editorial transparency

Medical sources

Patient information is based on established government and professional guidance. Content updated 5 October 2026. This is patient information, not an individual clinical assessment.