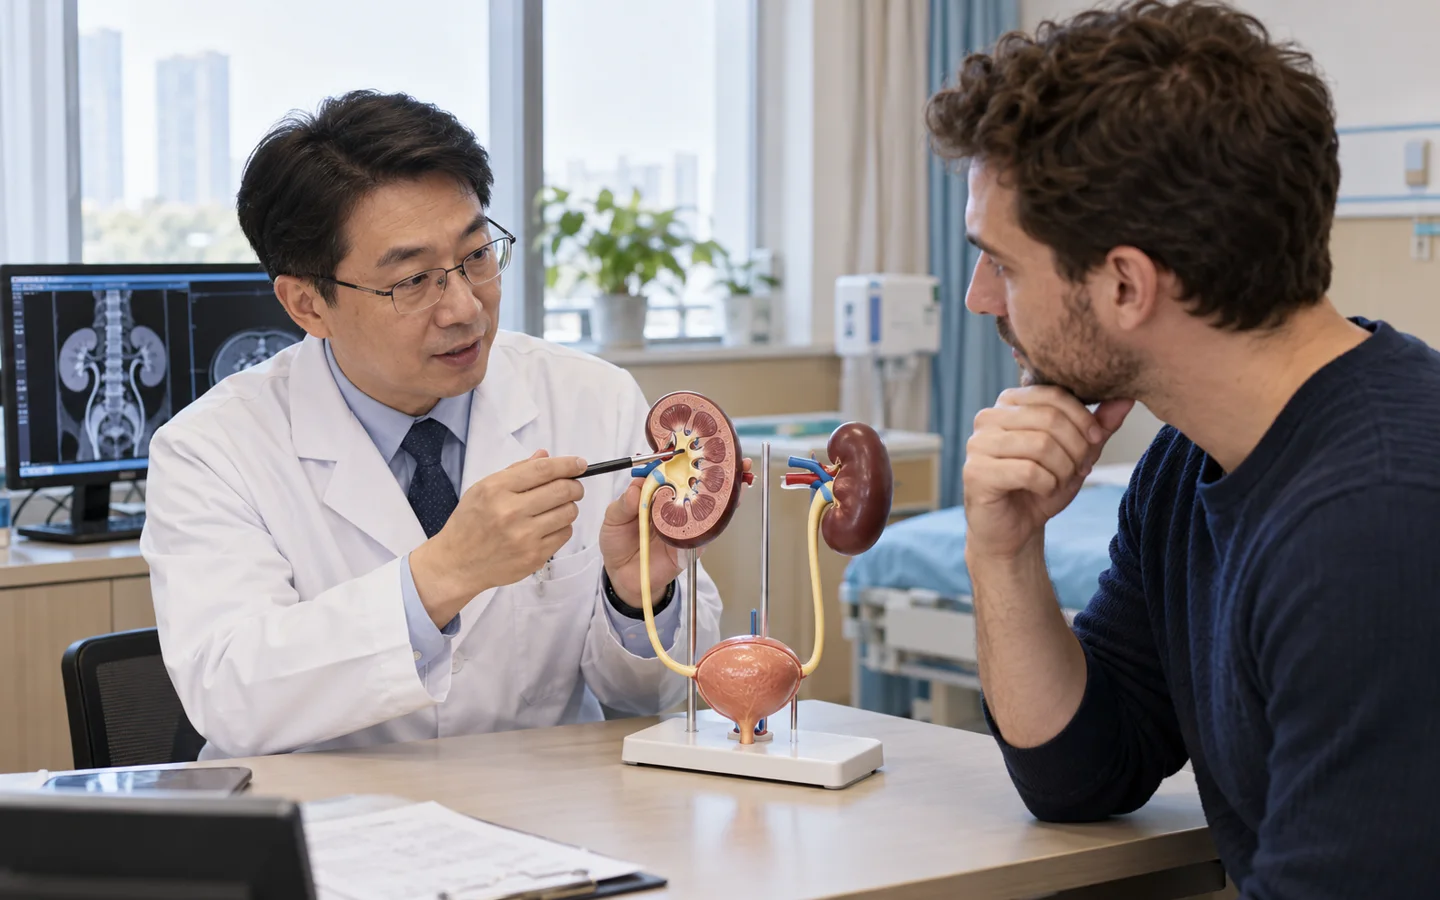
Pyeloplasty removes or bypasses a narrowed kidney drainage junction
The ureter is detached from the obstructed segment and reconnected to the renal pelvis in a wider, dependent position. A crossing vessel may influence reconstruction.
Dilation on imaging alone does not always prove harmful obstruction. Symptoms, infections, differential function and drainage curves help determine whether surgery is justified.
Ask what evidence shows obstruction, how much function the kidney contributes and what improvement is realistically expected.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about pyeloplasty.
- Symptomatic ureteropelvic-junction obstruction.
- Recurrent infection or stones linked to poor drainage.
- Progressive hydronephrosis or declining differential kidney function.
- A failed prior endoscopic or reconstructive treatment requiring revision.
What the specialist team must confirm
Review CT or MR urography, diuretic renogram curves and differential function, ultrasound trend, urine cultures, stones, crossing vessels and previous stents or operations.
Key points for this treatment
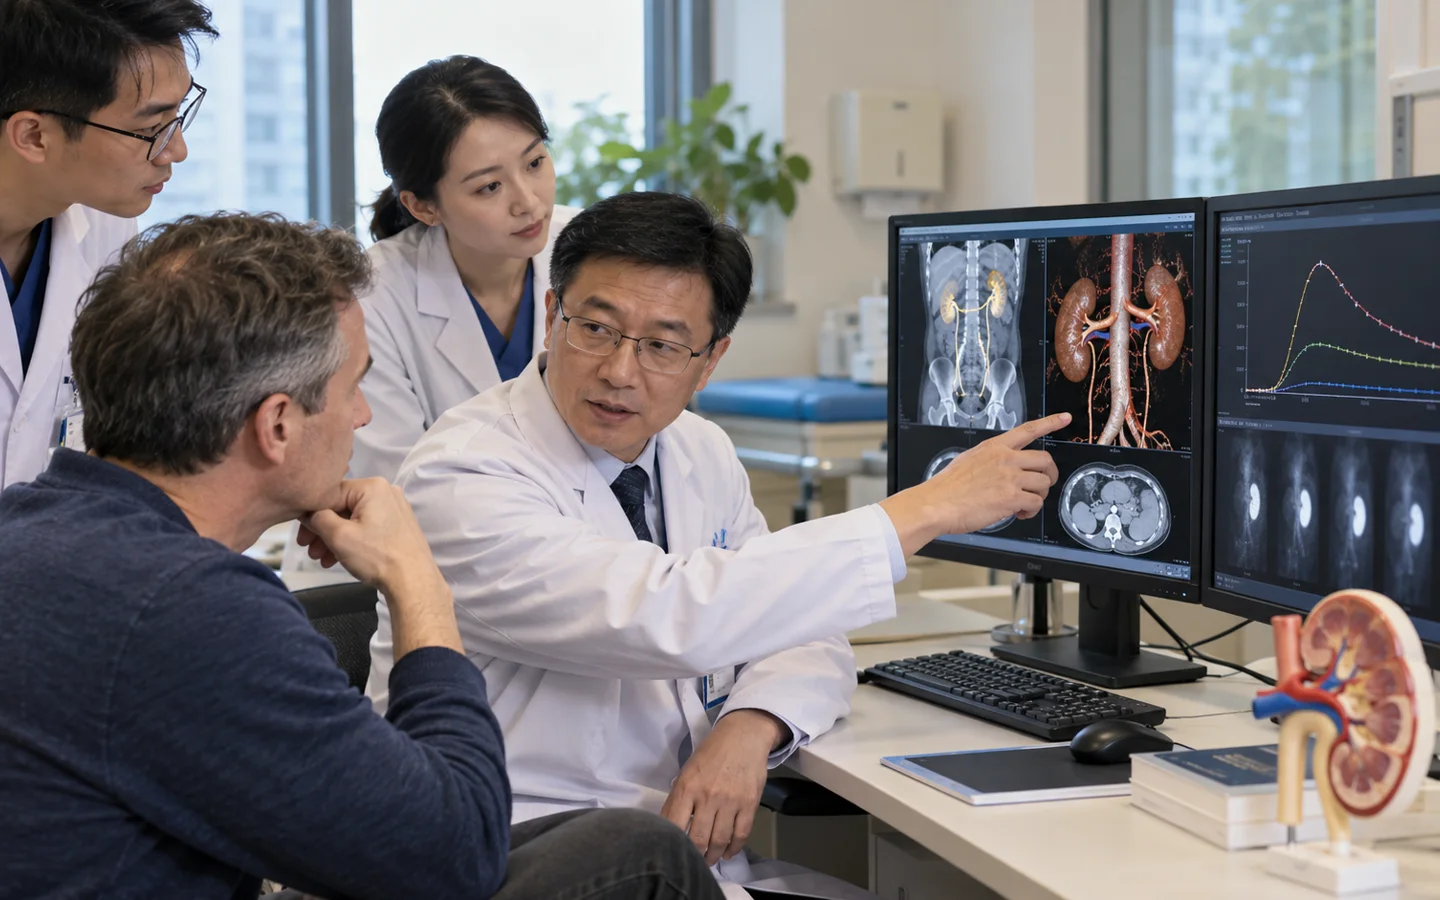
From functional confirmation to reconstructed drainage
A clear stent-removal and follow-up renogram plan prevents the operation from ending without objective outcome review.
Drainage improves before dilation always disappears
A ureteral stent commonly supports healing and can cause urinary frequency or flank discomfort until removal.
Ultrasound and sometimes repeat functional imaging assess drainage. The renal pelvis may remain enlarged even when obstruction has improved.
Risks, limits and realistic expectations
Risks include bleeding, infection, urine leak, stent symptoms, recurrent narrowing, persistent pain, injury to nearby structures and need for revision.
Fever, inability to urinate, severe flank pain, vomiting, catheter or stent concern or rapidly worsening swelling requires urgent local care.