
Diversion replaces or bypasses normal urinary storage and flow
Urine may drain continuously to a stoma bag, collect in a catheterizable internal pouch or pass through a reconstructed neobladder.
Each option has distinct continence, catheter, bowel, electrolyte and revision implications. Reliable kidney drainage takes priority over technical complexity.
Patients should see equipment, practice key tasks and understand nighttime management before committing to an option.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about urinary diversion and reconstruction.
- A patient undergoing bladder removal.
- A nonfunctional or severely damaged bladder.
- Complex obstruction or fistula requiring bypass.
- A patient able to maintain follow-up and diversion care.
What the specialist team must confirm
Review renal and ureter anatomy, bowel and radiation history, urethral suitability, kidney function, mobility, vision, hand function, cognition, support and infection risk.
Key points for this treatment
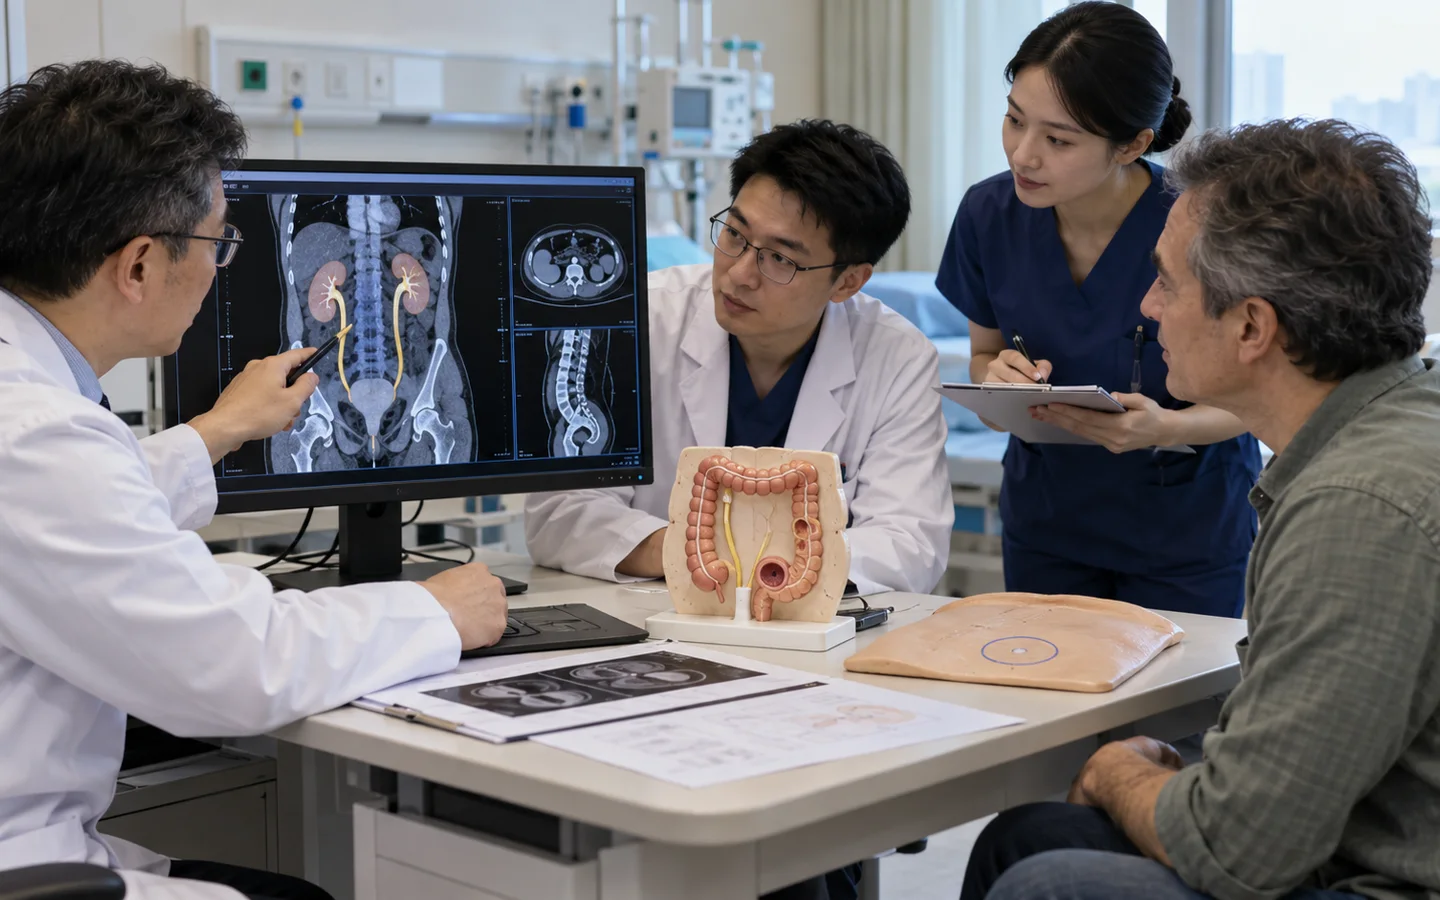
From shared selection to lifelong diversion maintenance
Preoperative education and realistic self-care planning reduce preventable problems after discharge.
Long-term monitoring protects the reconstruction
Early care addresses bowel recovery, urine leaks, catheter or stoma function, infection and skin.
Later follow-up checks kidney dilation, electrolytes, vitamin status, stones, infections, continence and any cancer surveillance needs.
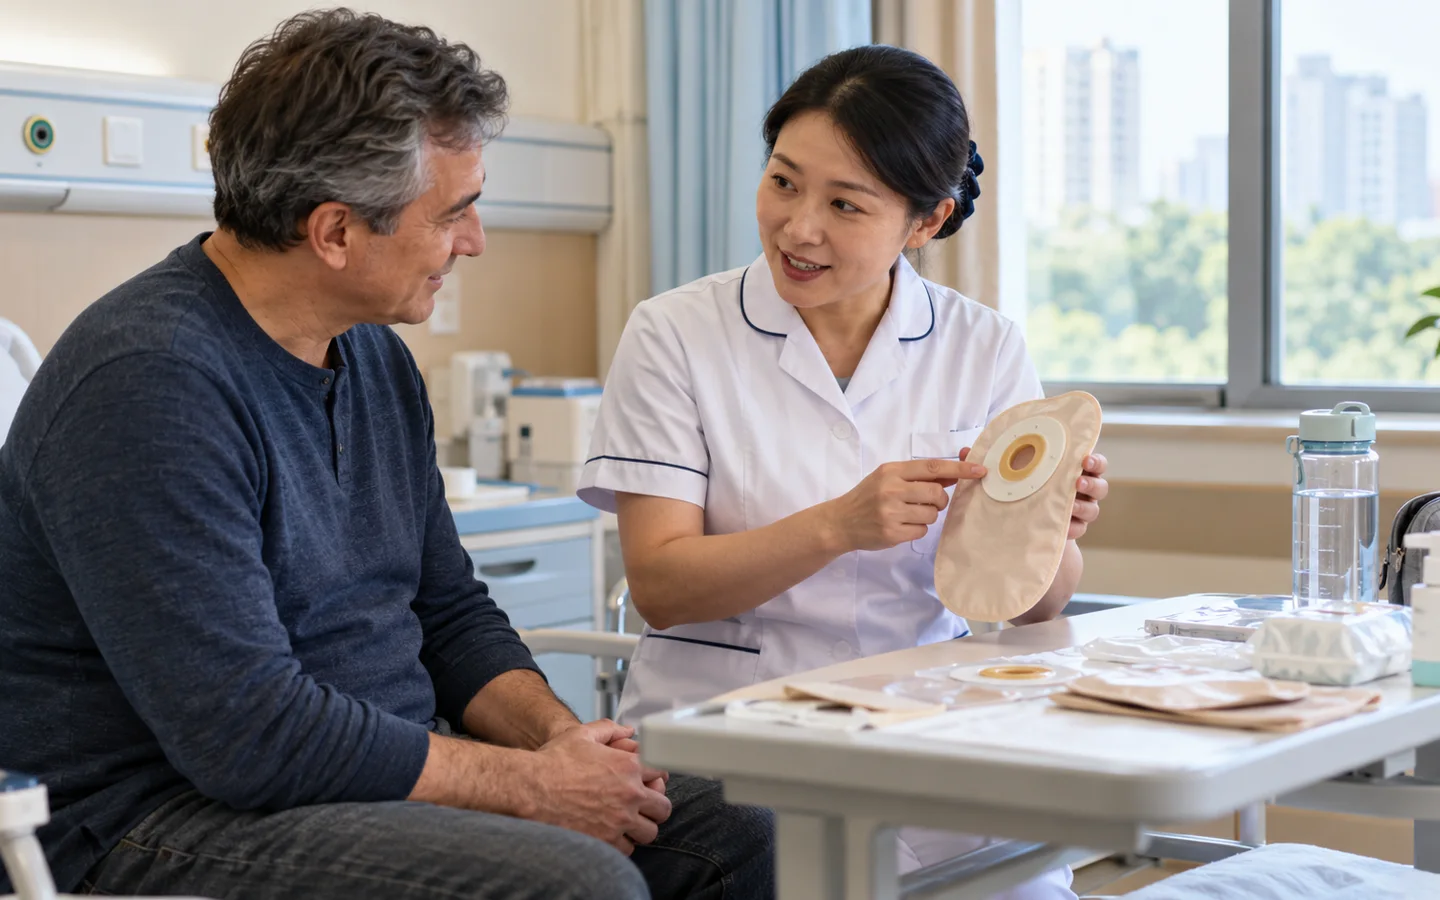
Risks, limits and realistic expectations
Risks include bowel obstruction or leak, urinary leak, infection, stones, electrolyte or vitamin problems, incontinence, stomal complications, catheter difficulty and kidney decline.
No urine output, fever, flank pain, persistent vomiting, a dark stoma or inability to catheterize requires urgent local help.