Radical nephrectomy is used when kidney preservation is not oncologically or technically appropriate
The operation removes the kidney and may include surrounding fat, adrenal gland or lymph nodes according to tumor position and stage.
Large tumors, central involvement or tumor thrombus may require complex vascular planning beyond a standard laparoscopic nephrectomy.
Baseline function, diabetes, blood pressure and contrast exposure influence both operative choice and long-term care.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about radical nephrectomy.
- A renal cancer not suitable for partial nephrectomy.
- A large central or locally advanced renal mass.
- A poorly functioning diseased kidney causing selected serious problems.
- A patient with adequate opposite-kidney reserve and acceptable operative risk.
What the specialist team must confirm
Review contrast CT or MRI of abdomen and chest, renal vein and vena cava, metastases, contralateral kidney, eGFR, anemia, performance status and whether systemic treatment or vascular expertise is needed.
Key points for this treatment
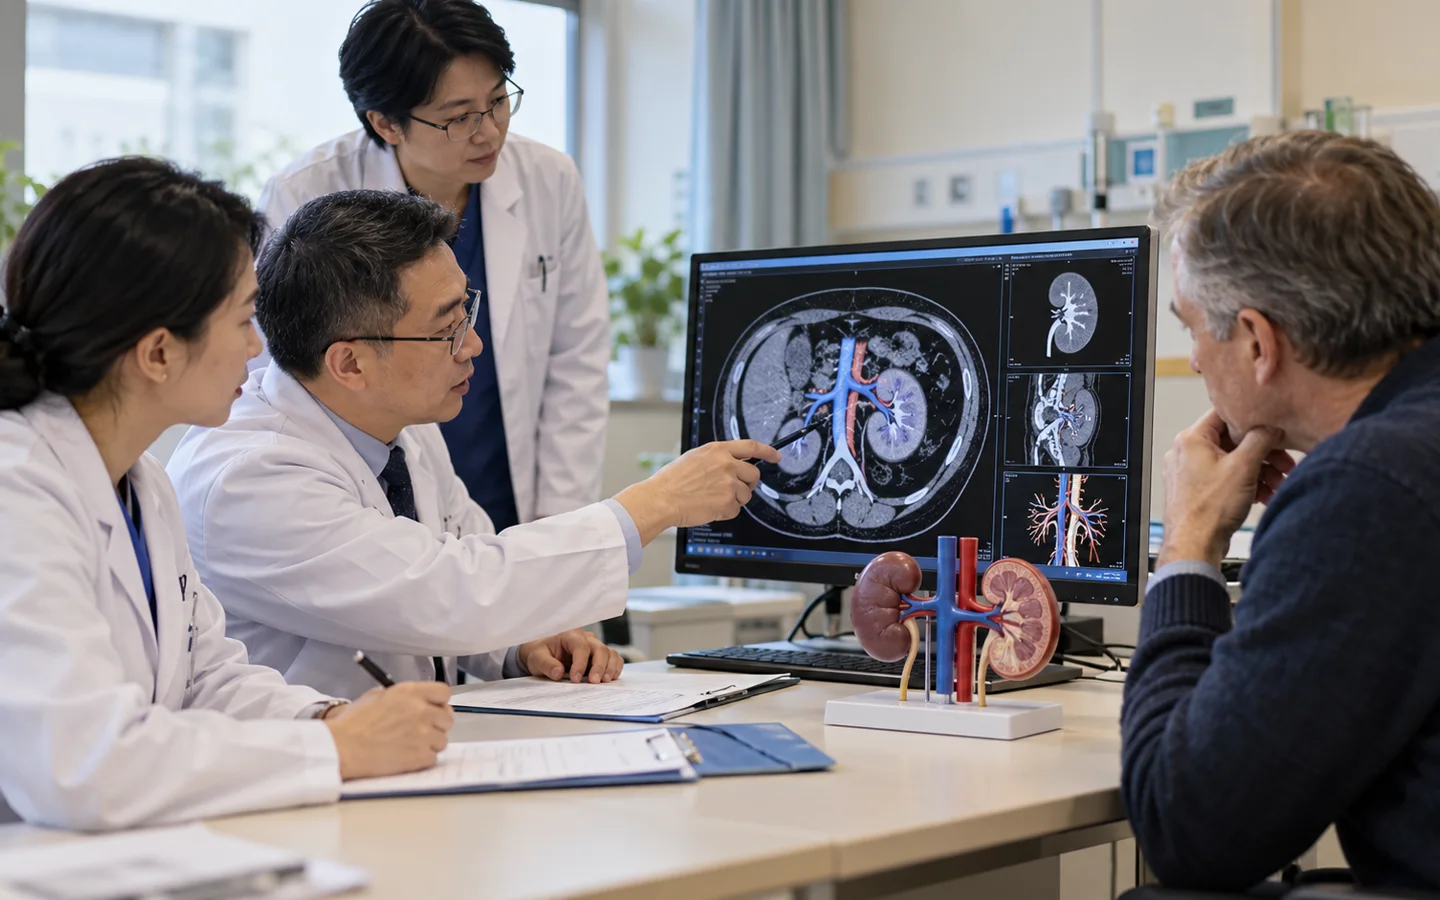
From whole-body staging to single-kidney follow-up
Surgery should sit within an oncology plan, especially when recurrence risk or metastatic disease may require systemic therapy.
Recovery includes cancer surveillance and kidney protection
Early care monitors bleeding, bowel recovery, clots, pain and kidney function. Final pathology refines stage and recurrence risk.
Long-term care includes renal function, blood pressure, cardiovascular risk, medication review and surveillance imaging.
Risks, limits and realistic expectations
Risks include bleeding, infection, organ or vascular injury, blood clots, hernia, chronic kidney disease, cardiovascular impact, recurrence and anesthesia complications.
Fever, faintness, new breathlessness, rapidly increasing abdominal pain or swelling, heavy hematuria or very low urine output needs urgent local care.