
Robotic prostatectomy removes the prostate and seminal vesicles through keyhole access
The bladder is reconnected to the urethra after the prostate is removed. Pelvic lymph nodes may be sampled according to cancer risk.
Robotic access does not determine cancer control by itself. Tumor location, margin strategy, nerve involvement and surgical experience matter more than the platform label.
Nerve sparing, bladder-neck preservation and lymph-node dissection are individualized and may conflict with cancer-control priorities.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about robotic radical prostatectomy.
- Localized or selected locally advanced prostate cancer where surgery is an appropriate option.
- A patient with life expectancy and health compatible with curative treatment.
- A patient who understands alternatives such as radiotherapy or active surveillance.
- A patient prepared for catheter care and functional rehabilitation.
What the specialist team must confirm
Review PSA history, biopsy grade and cores, prostate MRI, staging imaging when indicated, baseline urinary and erectile function, prostate size, prior TURP, abdominal surgery and cardiovascular risk.
Key points for this treatment
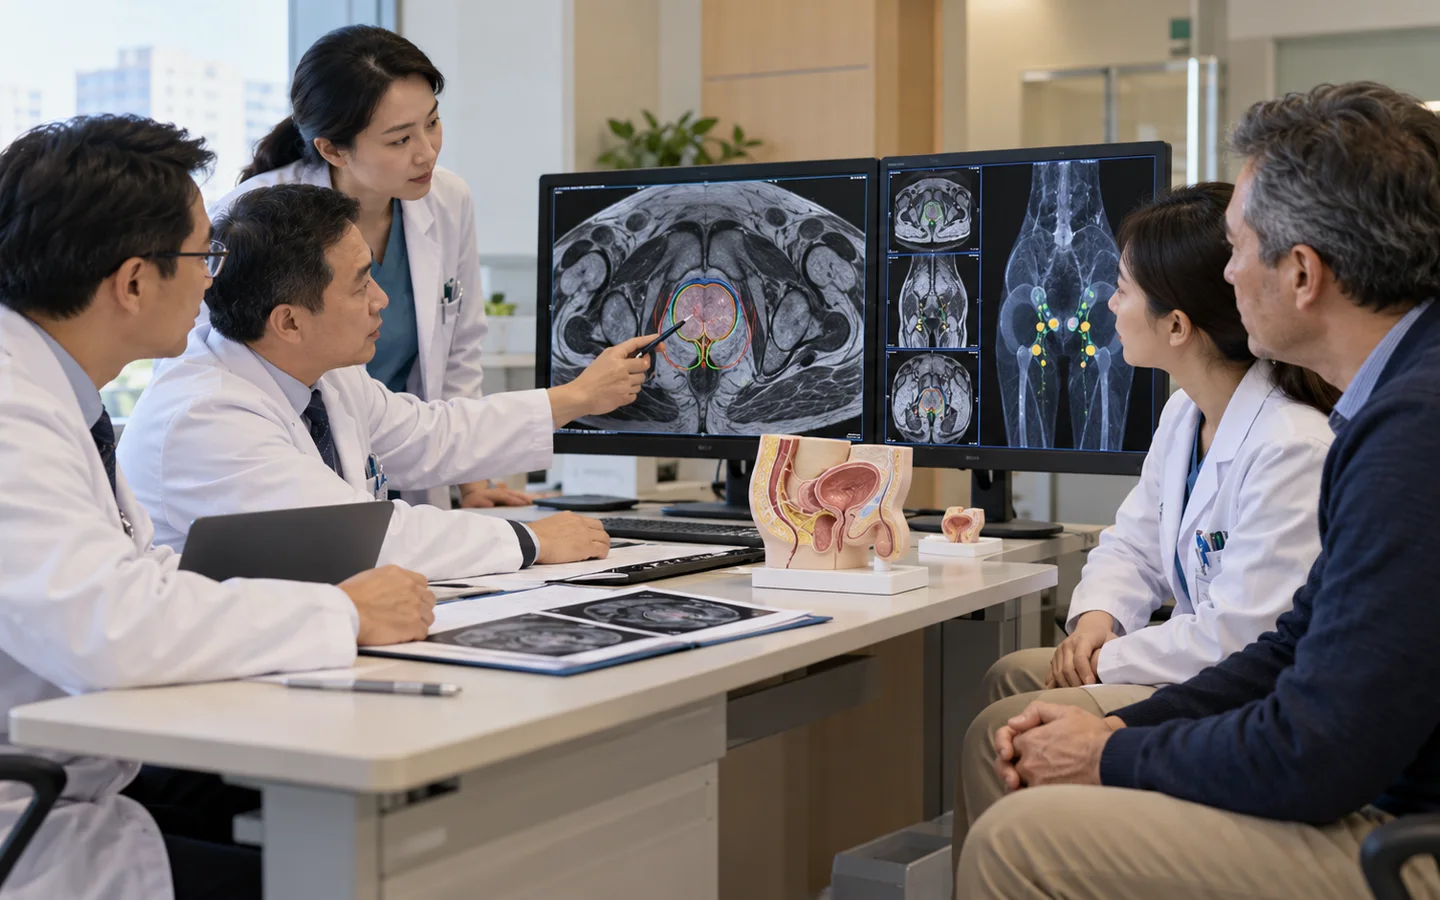
From cancer-risk discussion to functional rehabilitation
The treatment decision compares surgery with equally relevant alternatives, not simply robotic versus open access.
PSA and function are followed on different timelines
A catheter remains while the bladder-urethra connection heals. Continence often improves gradually with pelvic-floor rehabilitation.
PSA monitoring assesses cancer control. Erectile recovery depends on baseline function, nerve sparing, age and rehabilitation and may take much longer.

Risks, limits and realistic expectations
Risks include bleeding, infection, urine leak, bladder-neck narrowing, urinary incontinence, erectile dysfunction, lymphocele, blood clots, positive margins and need for additional cancer treatment.
Fever, catheter blockage, inability to drain urine, calf swelling, chest pain, severe pelvic pain or heavy bleeding requires urgent local care.