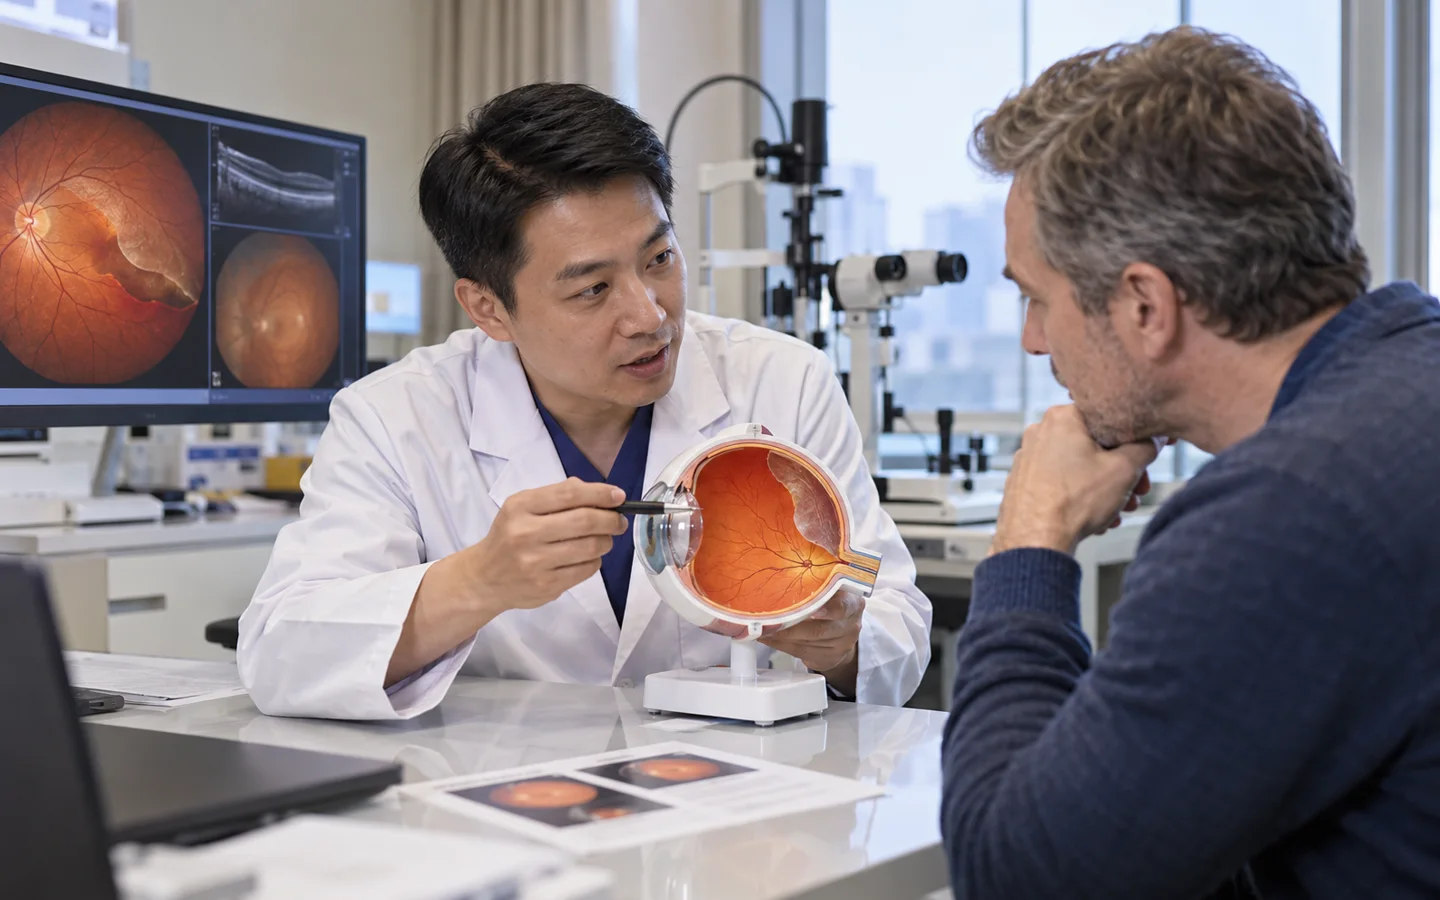
Retinal detachment repair seals retinal breaks and restores retinal contact
Pneumatic retinopexy, scleral buckle and vitrectomy use different ways to close tears and relieve vitreous traction.
The technique depends on tear number and location, detachment extent, macular involvement, lens status, scarring and whether postoperative positioning is feasible.
A new curtain shadow, flashes or rapid field loss requires immediate retinal assessment near the patient.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about retinal detachment repair.
- A rhegmatogenous retinal detachment requiring repair.
- Selected retinal tears with localized detachment suitable for office gas treatment.
- Complex detachment with vitreous hemorrhage or proliferative vitreoretinopathy.
- A recurrent detachment requiring revision.
What the specialist team must confirm
Document onset, visual field, macular status, retinal breaks, detachment extent, proliferative scarring, lens and prior cataract or retinal surgery, fellow eye and travel constraints.
Key points for this treatment
From emergency retinal mapping to reattachment surveillance
The plan includes travel restrictions, positioning support and what to do if the visual field worsens again.
Anatomical repair does not guarantee full visual recovery
Drops, positioning and activity restrictions vary. Gas bubbles prohibit flying and nitrous oxide anesthesia until fully absorbed.
The team monitors pressure, cataract, recurrent detachment and scarring. Visual recovery is often slower and less complete when the macula was detached.

Risks, limits and realistic expectations
Risks include recurrent detachment, cataract, infection, bleeding, high or low pressure, double vision, membrane scarring, need for silicone-oil removal and permanent vision loss.
Any new curtain shadow, expanding field defect, sudden floaters, severe pain, nausea or abrupt visual decline after repair requires emergency retinal care.