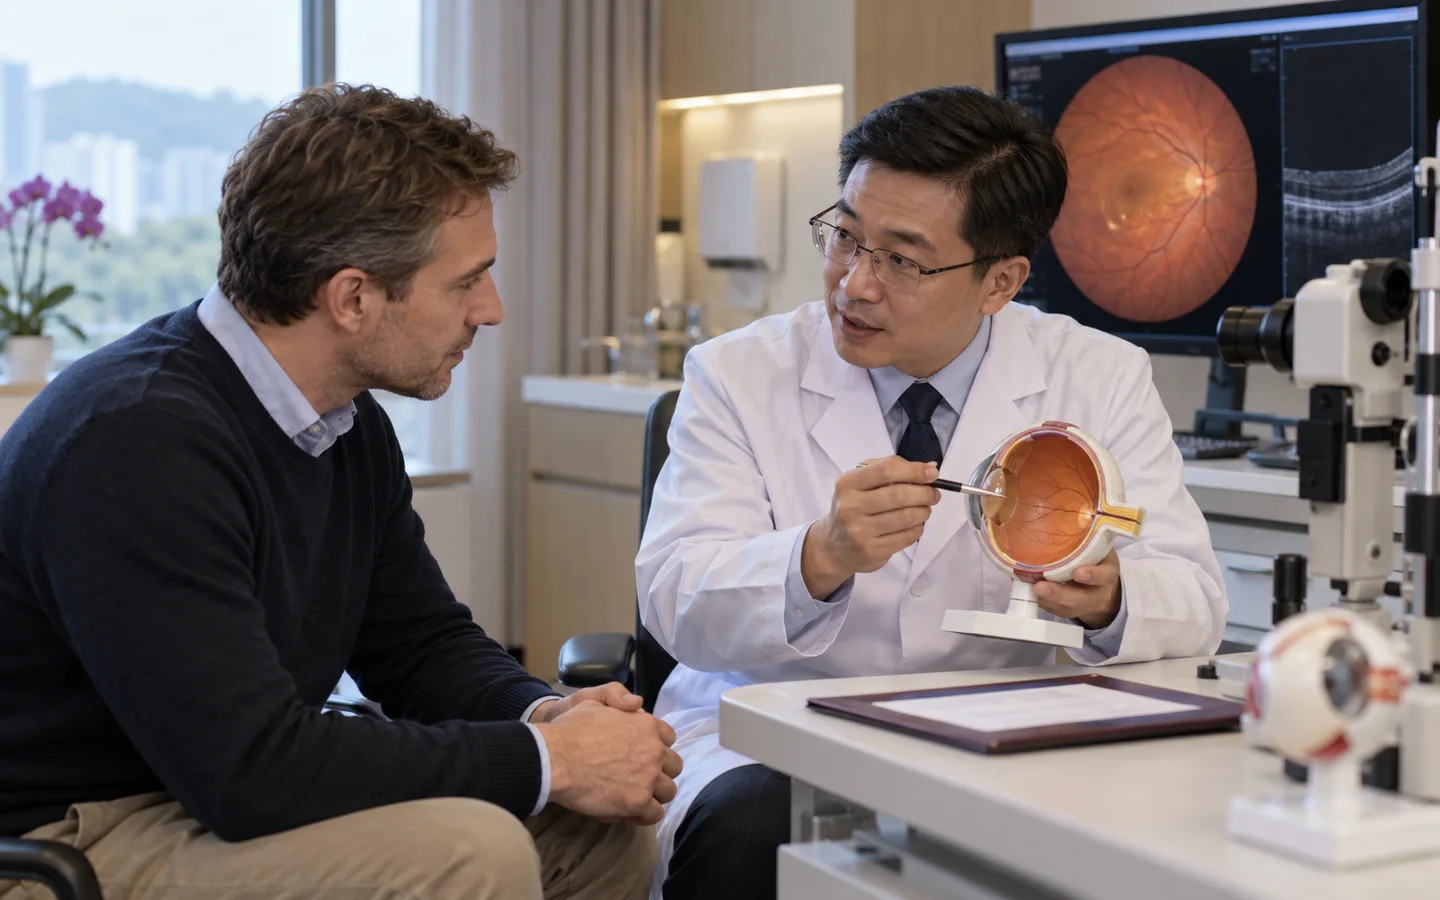
Vitrectomy creates access to treat disease at the back of the eye
Small instruments remove vitreous and may clear blood, release traction, peel membranes, drain fluid, apply laser or insert gas or silicone oil.
The operation name alone does not describe the case. Prognosis depends on the retina and optic nerve, why surgery is needed and whether the macula has sustained damage.
Membrane peeling, retinal laser, detachment repair and tamponade determine recovery and restrictions.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about vitrectomy.
- Non-clearing vitreous hemorrhage.
- Macular hole, epiretinal membrane or traction.
- Retinal detachment requiring internal repair.
- Infection, retained lens material or other selected posterior-segment problem.
What the specialist team must confirm
Review dilated retinal examination, OCT, ultrasound when the view is blocked, angiography where relevant, lens status, pressure, cause and duration, previous injections and surgery and fellow-eye function.
Key points for this treatment
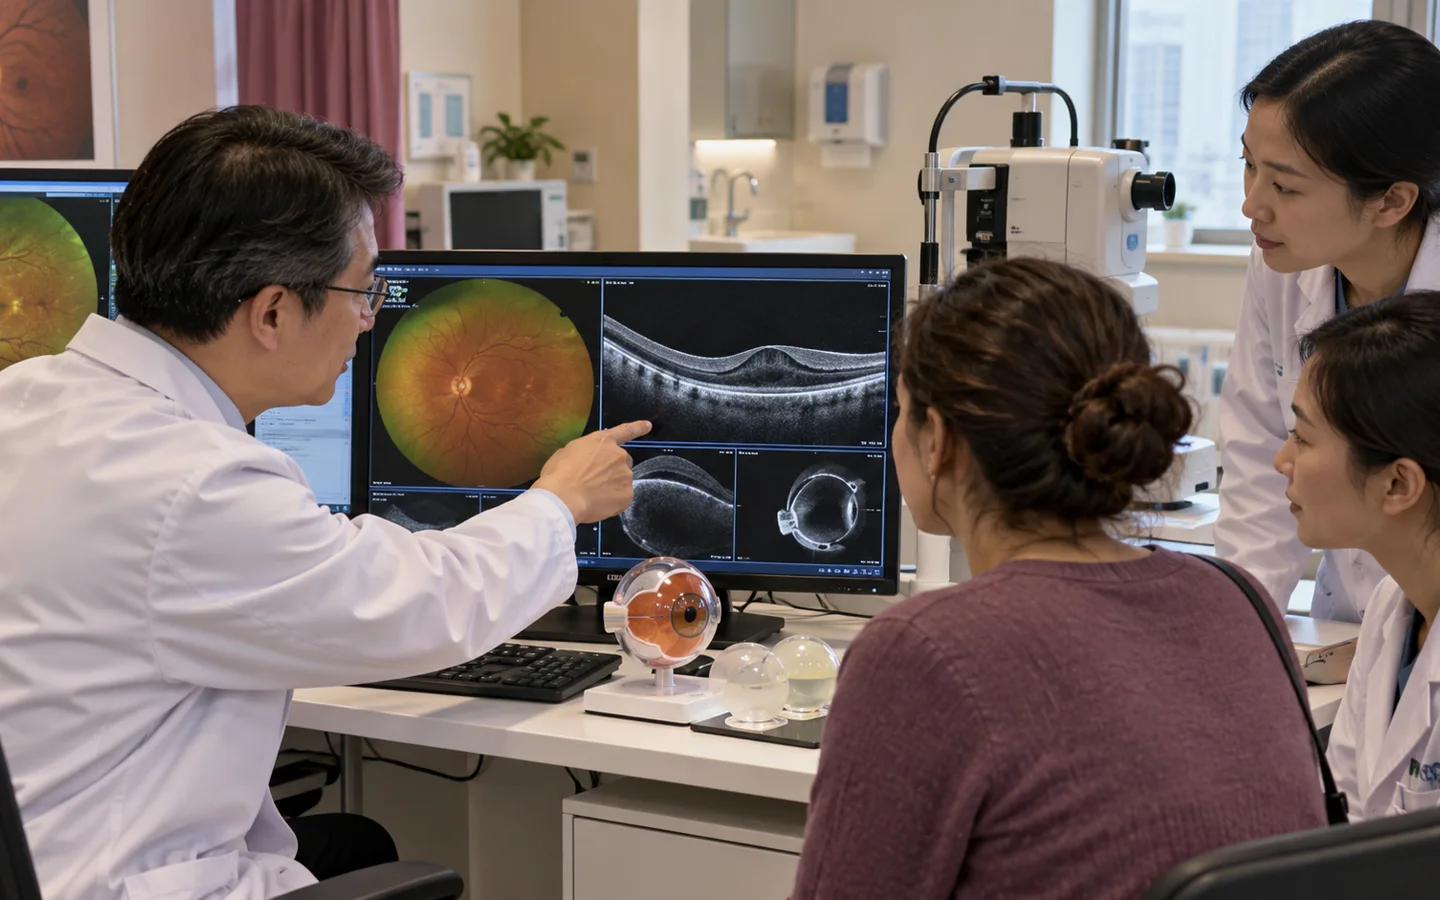
From obscured or tractional retina to structured recovery
Patients receive procedure-specific guidance for positioning, drops, travel and whether silicone oil may need later removal.
Recovery follows the retina, tamponade and lens
Vision may initially be very blurred with gas, oil, inflammation or the original retinal disease. Pressure and wounds are checked early.
Later OCT and retinal examination assess anatomy. Cataract commonly progresses in natural-lens eyes, and silicone oil may require another operation.
Risks, limits and realistic expectations
Risks include retinal tear or detachment, infection, bleeding, pressure change, cataract, corneal damage, need for repeat surgery and incomplete or worsened vision.
New field loss, sudden floaters, severe pain, nausea, increasing redness or rapid vision decline after vitrectomy requires urgent retinal assessment.