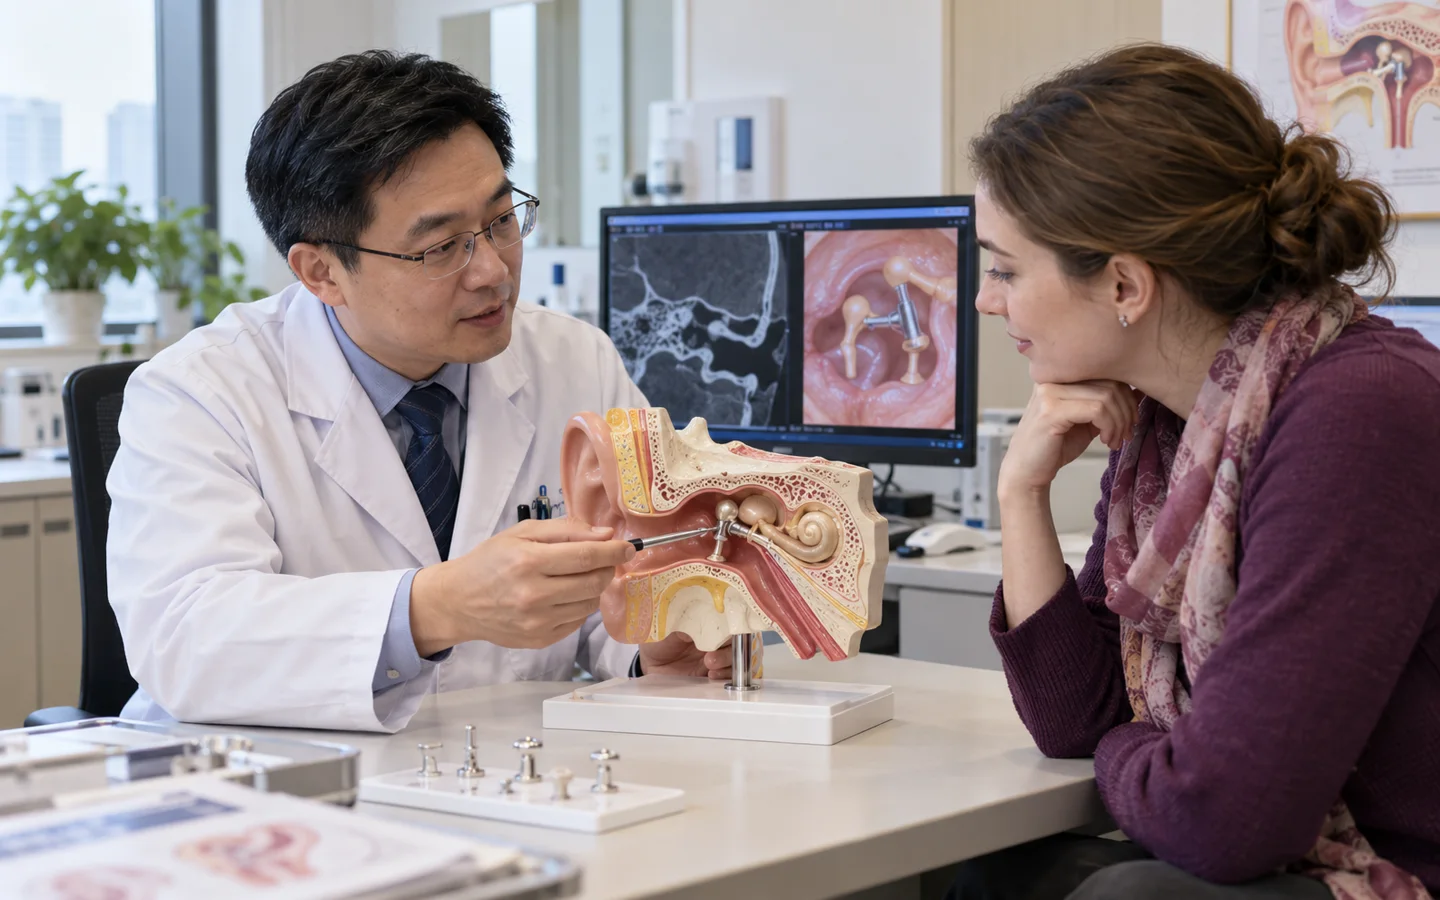
Stapes Surgery: diagnosis, function and long-term planning
Stapes Surgery is considered when otosclerosis fixes the stapes and creates a clinically meaningful conductive or mixed hearing loss.
The choice between observation, hearing aids and stapes surgery depends on audiometric pattern, speech understanding, inner-ear reserve, anatomy, occupation and acceptance of rare severe hearing loss.
Who may be considered?
Specialist review may help when conductive loss is progressive and the patient wants to compare surgical hearing improvement with amplification.
- Confirmed stapes fixation with a suitable air-bone gap.
- Good enough cochlear reserve for useful postoperative hearing.
- A patient who understands hearing-aid alternatives.
- A patient able to follow pressure and activity precautions.
What the specialist team must confirm
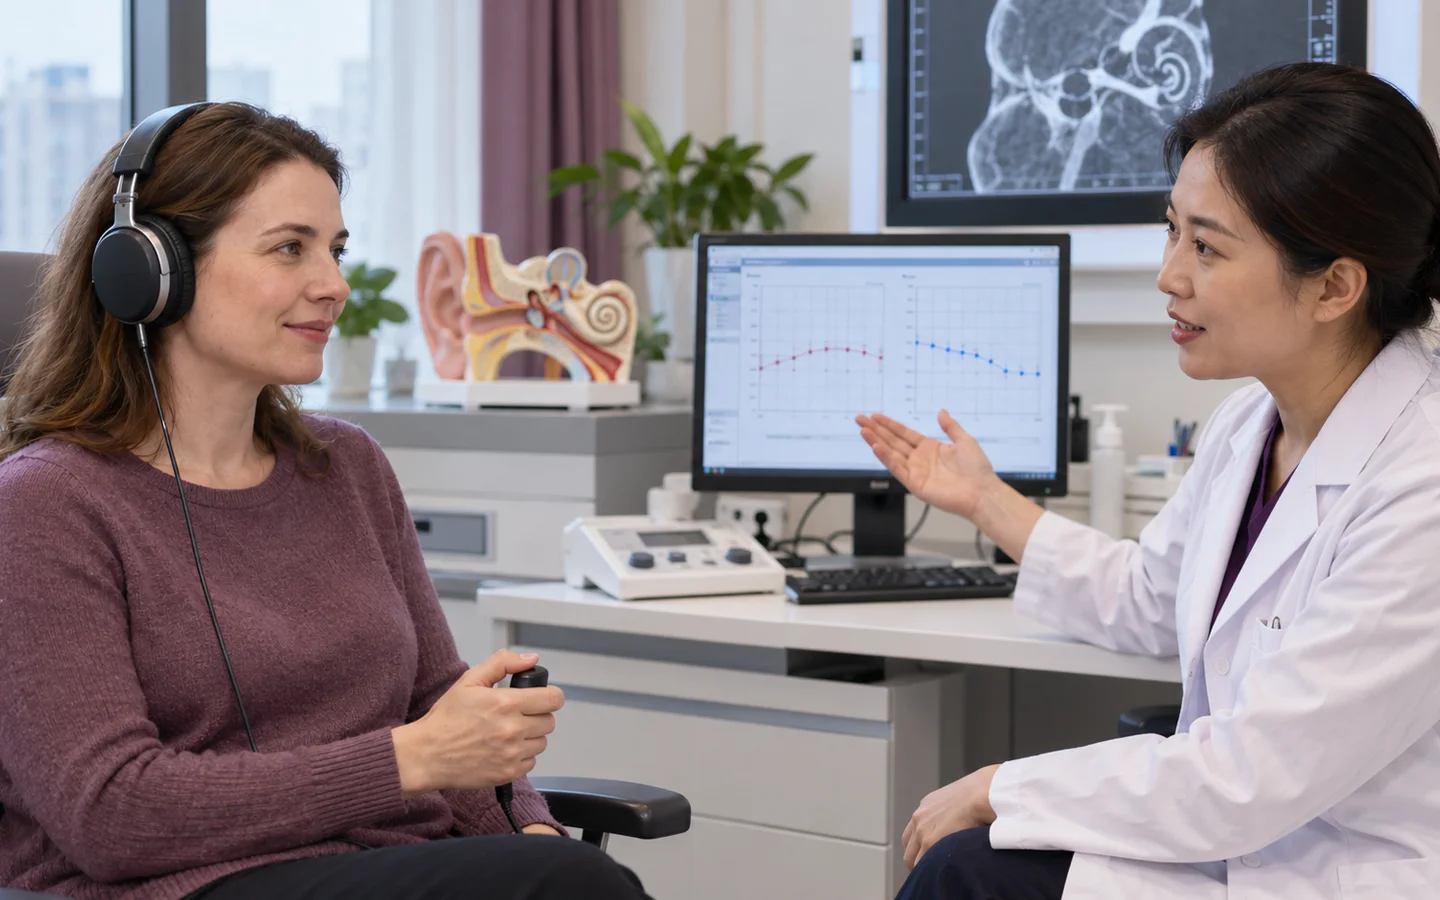
Review serial audiograms, speech discrimination, tympanometry and acoustic reflexes, otoscopy, vestibular symptoms, family history and CT only when diagnosis or anatomy is atypical.
Key points for this treatment

From conductive hearing analysis to stable sound transmission
The operated ear, anesthesia plan and prosthesis strategy should be documented together with contingency plans for unexpected anatomy.
Balance settles before the final hearing result
Temporary dizziness, taste change and blocked hearing can occur while packing and middle-ear fluid resolve.
Audiograms confirm closure of the air-bone gap and monitor recurrent loss, prosthesis problems or inner-ear decline.
Risks, limits and realistic expectations
Risks include temporary or persistent vertigo, taste disturbance, tinnitus, eardrum injury, prosthesis displacement, facial weakness and partial or profound sensorineural hearing loss.
Sudden marked hearing decline, severe spinning vertigo, facial weakness, fever or fluid leakage after surgery needs urgent local ENT care.