
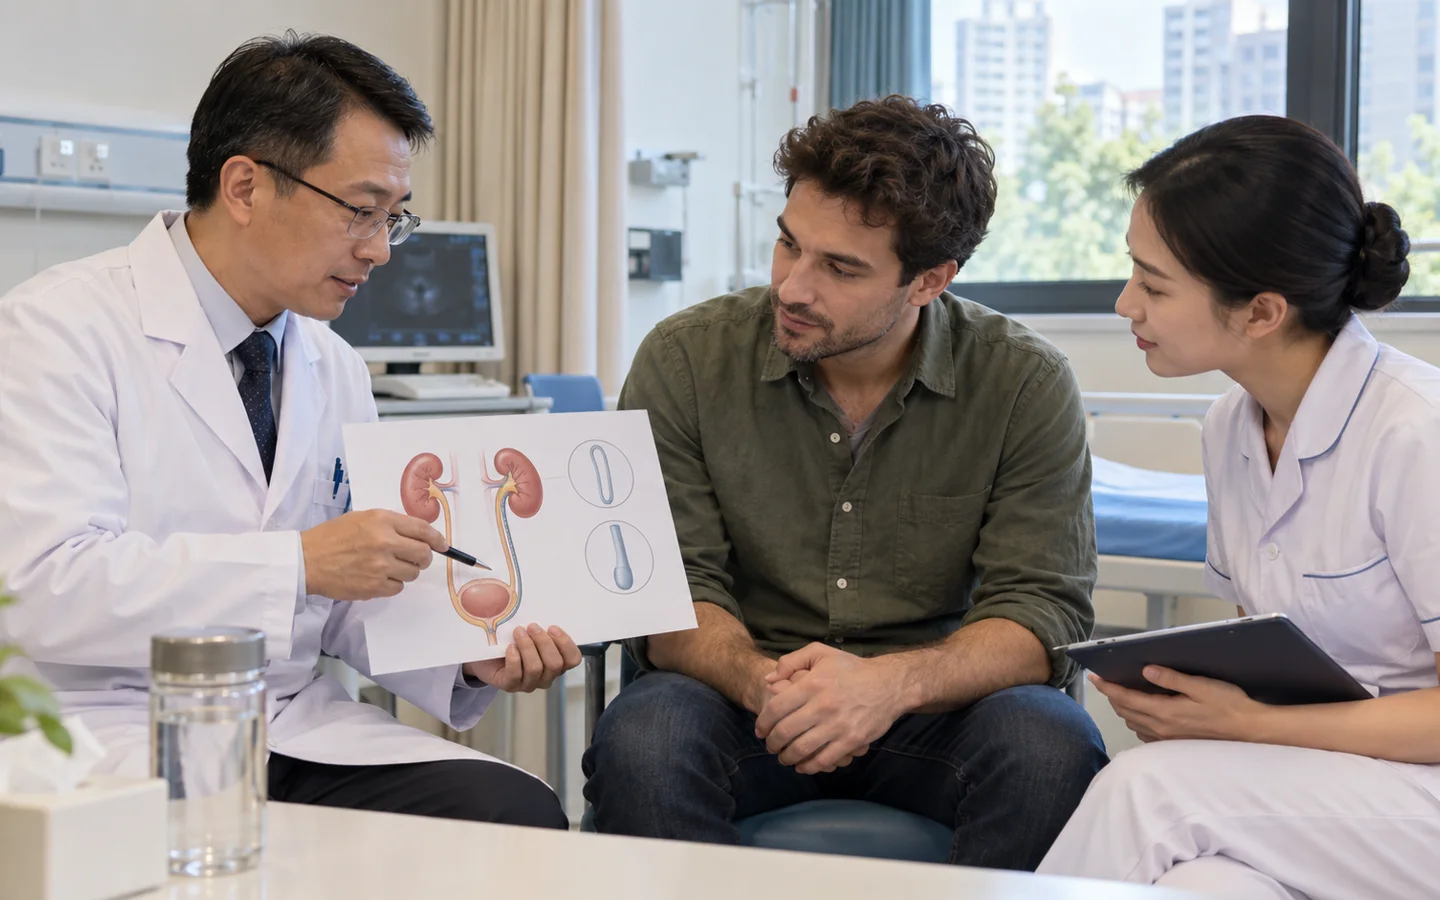
Ureteroscopy reaches the stone through the natural urinary passage
A thin scope passes through the bladder into the ureter and sometimes the kidney. Laser energy fragments the stone and baskets may remove pieces.
Access can be limited by a narrow ureter, swelling, previous reconstruction or infection. Staged treatment with an initial stent is sometimes safer than forcing access.
Before treatment, clarify why a stent may be placed, how long it should remain and exactly where removal will occur.
Who may be considered?
Specialist review may help when the diagnosis, symptoms and previous treatment create a focused question about ureteroscopy and laser lithotripsy.
- A ureter stone unlikely to pass or causing persistent symptoms.
- A kidney stone suitable for flexible ureteroscopic access.
- A residual stone after another treatment.
- A patient needing active stone removal after infection is controlled.
What the specialist team must confirm
The team reviews CT anatomy, total stone burden, obstruction, urine culture, renal function, ureteral narrowing, prior stents, anticoagulation and anesthesia risk.
Key points for this treatment

From sterile access to planned stent removal
The procedure is complete only when the residual-stone and stent follow-up plans are documented.
Stent symptoms and residual fragments need a timetable
Frequency, urgency, flank discomfort and blood in urine can occur with a ureteral stent. Medicines and activity advice may reduce symptoms.
Imaging and stone analysis guide clearance and recurrence prevention. Forgotten stents can encrust and cause serious problems.
Risks, limits and realistic expectations
Risks include infection, bleeding, ureter perforation or later stricture, incomplete clearance, stent discomfort, repeat treatment and anesthesia complications.
Fever, chills, inability to urinate, escalating flank pain, vomiting or heavy bleeding after ureteroscopy requires urgent local care.